Despite advances in systemic therapy, metastatic pancreatic cancer (mPC) remains one of the most lethal malignancies. Current frontline regimens, including FOLFIRINOX and gemcitabine plus nab-paclitaxel, provide limited long-term benefit, and there is no established standard of care for patients whose disease progresses after multiple lines of chemotherapy. To address this unmet need, we conducted a prospective phase II study to assess the therapeutic potential of combining TAS-102 (trifluridine/tipiracil) with the multi-target tyrosine kinase inhibitor surufatinib in patients with heavily pretreated mPC. Patients with mPC who had experienced disease progression following at least two prior systemic treatment regimens were enrolled. Participants received oral TAS-102 at 35 mg/m² twice daily on days 1–5 and 8–12, along with continuous daily surufatinib at 250 mg, in repeating 28-day cycles. Radiographic evaluations were performed at 8-week intervals. Treatment was maintained until objective disease progression, unacceptable adverse effects, clinical decision to discontinue, or patient withdrawal. Clinical outcomes included progression-free survival (PFS), overall survival (OS), objective response rate (ORR), disease control rate (DCR), and treatment-related toxicity. Between January 2023 and June 2024, 22 patients were enrolled, of whom 20 were evaluable for efficacy. The median PFS achieved with the combination therapy was 2.35 months (95% CI, 1.91–3.94), while the median OS was 6.34 months (95% CI, 3.81–10.09). Tumor shrinkage meeting criteria for partial response was observed in four patients, yielding an ORR of 20%, and disease stabilization or response was achieved in 30% of patients overall. All participants experienced at least one treatment-emergent adverse event, with hematologic toxicities predominating. The most frequently reported events included anemia, neutropenia, leukocytopenia, and lymphocytopenia. Severe (grade ≥3) adverse events occurred in half of the cohort, most commonly neutropenia. Exploratory subgroup analyses indicated reduced clinical benefit in patients with liver metastases or dissemination to more than two organ sites. Proteomic profiling identified elevated expression of OCIAD2 as a marker of poor clinical outcome, a result that was independently corroborated using data from the CPTAC and RuiJin cohorts. In this prospective study, the combination of TAS-102 and surufatinib exhibited measurable antitumor activity and an acceptable safety profile in patients with metastatic pancreatic cancer who had exhausted standard treatment options. The identification of clinical and proteomic correlates of outcome suggests potential avenues for patient selection and personalized therapy, which warrant confirmation in larger studies. This trial was registered at ClinicalTrials.gov (NCT05481463).
Introduction
Pancreatic cancer remains one of the most lethal malignancies worldwide and continues to pose a substantial public health challenge. It currently ranks as the seventh leading cause of cancer-related mortality globally [1]. In China, the burden of this disease is particularly pronounced, with approximately 118,700 new diagnoses and 106,300 deaths reported in 2022 [2]. Survival outcomes have shown little improvement over recent decades, with long-term survival remaining rare and 5-year survival rates consistently below 10%. These sobering statistics emphasize the urgent necessity for more effective treatment strategies.
Curative treatment is possible only through surgical resection; however, the majority of patients are not candidates for surgery at diagnosis. Fewer than one-fifth of patients present with resectable disease, and among those who undergo curative-intent surgery followed by adjuvant chemotherapy, disease recurrence occurs in nearly 60% within three years [3]. For patients with locally advanced or metastatic pancreatic cancer, systemic therapy is the principal treatment approach, yet outcomes remain dismal, with overall survival rates among the poorest reported for solid tumors [4].
For advanced or metastatic pancreatic cancer (mPC), current treatment recommendations from the National Comprehensive Cancer Network (NCCN) prioritize combination chemotherapy regimens, including FOLFIRINOX and gemcitabine plus nab-paclitaxel (AG) [5]. These regimens demonstrated improved survival compared with gemcitabine monotherapy in the landmark PRODIGE-4 [6] and MPACT [7] trials, respectively. Despite these advances, treatment responses are limited, with objective response rates of approximately 20% and median overall survival rarely extending beyond one year [6, 7]. Nanoliposomal irinotecan (nal-IRI) has expanded therapeutic options in both first- and second-line settings following positive outcomes in the NAPOLI-3 [8] and NAPOLI-1 [9] trials. In clinical practice, second-line management often involves transitioning between first-line regimens to mitigate cumulative toxicity, a strategy primarily supported by retrospective analyses [10].
Targeted therapeutic approaches for chemotherapy-resistant mPC remain applicable to only a small fraction of patients. Potentially actionable molecular alterations include KRAS mutations, HER2 amplification, NTRK gene fusions, and mismatch repair deficiency [4]. PARP inhibitors have demonstrated benefit in patients with BRCA-mutated mPC who previously achieved disease control with platinum-based chemotherapy [11]. However, such genomic vulnerabilities are identified in fewer than 5% of cases, leaving the vast majority of patients without effective targeted treatment options after standard chemotherapy failure.
TAS-102 is an orally administered cytotoxic agent composed of trifluridine, a thymidine analog that incorporates into DNA, and tipiracil, which inhibits trifluridine degradation. This agent has shown clinical benefit in patients with refractory metastatic colorectal cancer (mCRC) [12] and has demonstrated activity in tumors resistant to fluorouracil-based therapy [13, 14]. Preclinical investigations further revealed that TAS-102 induces DNA damage and suppresses proliferation in fluorouracil-resistant pancreatic cancer models [15]. Its clinical potential in pancreatic cancer was explored in a phase II trial (NCT02921737), which, despite early termination due to limited accrual, reported encouraging efficacy and acceptable tolerability in patients who progressed after first-line therapy, with median progression-free and overall survival of 13.64 and 23.45 weeks, respectively.
The integration of anti-angiogenic therapy into cancer treatment has yielded substantial benefits across multiple tumor types, particularly metastatic colorectal cancer. In this setting, the addition of bevacizumab to TAS-102 significantly improved survival compared with TAS-102 alone, as demonstrated in the SUNLIGHT trial [14]. This success has prompted exploration of oral tyrosine kinase inhibitors (TKIs) that inhibit angiogenic signaling pathways. Regorafenib, when combined with TAS-102, achieved clinically meaningful progression-free survival in a prospective phase II study involving patients with refractory mCRC [16]. These findings support the feasibility of combining angiogenesis inhibitors with TAS-102 and provide a rationale for investigating similar combinations in pancreatic cancer.
Surufatinib is a multi-target TKI that inhibits VEGF-mediated angiogenesis and additionally blocks CSF-1R and FGFR1 signaling. Through these mechanisms, surufatinib not only suppresses tumor vascularization but also alters the tumor immune microenvironment by reducing the accumulation and immunosuppressive activity of tumor-associated macrophages [17]. This effect is particularly relevant in pancreatic cancer, which is characterized by a dense stromal environment enriched with macrophages that facilitate immune escape and therapeutic resistance [18]. Several ongoing clinical trials are evaluating surufatinib in pancreatic cancer, either in combination with gemcitabine-based chemotherapy (CTR20240939, NCT05218889, NCT06051851) or immune checkpoint blockade [19]. Given the complementary mechanisms of surufatinib and TAS-102—encompassing angiogenesis inhibition, immune modulation, and direct cytotoxicity—their combination represents a biologically plausible strategy for patients with refractory disease.
Proteomic technologies have recently enabled more comprehensive interrogation of pancreatic cancer biology [20–22]. The Clinical Proteomic Tumor Analysis Consortium (CPTAC) performed large-scale proteogenomic profiling of pancreatic cancer specimens and identified several tumor-derived glycoproteins with potential diagnostic relevance [20]. Independent proteomic analysis of the RuiJin cohort further identified NDUFB8 and CEMIP2 as candidate biomarkers associated with response to adjuvant chemotherapy [21]. Additionally, integrative proteomic approaches have uncovered critical signaling interactions between tumor and stromal compartments, including the PDGFR–PTPN11–FOS axis, which appears to play a central role in tumor–stroma communication [22]. Collectively, these studies illustrate the value of proteomic profiling in identifying clinically relevant biomarkers and elucidating mechanisms of disease progression.
Against this background, we conducted a prospective, single-arm phase II trial to evaluate the clinical activity and safety of TAS-102 combined with surufatinib in patients with metastatic pancreatic cancer who had progressed after at least two prior lines of systemic therapy. This study also incorporated targeted genomic sequencing and proteomic analyses to explore biomarkers associated with treatment outcomes.
Materials and Methods
Study design and patient eligibility
This investigator-initiated, single-center, single-arm phase II study was conducted at Sun Yat-sen University Cancer Center between January 2023 and June 2024 (Figure 1a). Patients aged 18–75 years with histologically confirmed, unresectable metastatic pancreatic cancer were eligible if they had experienced disease progression on, or intolerance to, a minimum of two prior systemic treatment regimens. Additional eligibility requirements included an ECOG performance status of 0–1, at least one measurable lesion according to RECIST version 1.1, and adequate bone marrow, hepatic, renal, and coagulation function as determined by standard laboratory criteria, including blood counts, liver enzymes, creatinine, bilirubin, prothrombin time, and international normalized ratio. Patients were excluded if they had a history of another malignancy, active or uncontrolled infection, clinically significant bleeding events within three months prior to enrollment, or severe uncontrolled comorbid conditions such as heart failure or poorly controlled diabetes mellitus.
|
|
|
a) |
|
|
|
b) |
|
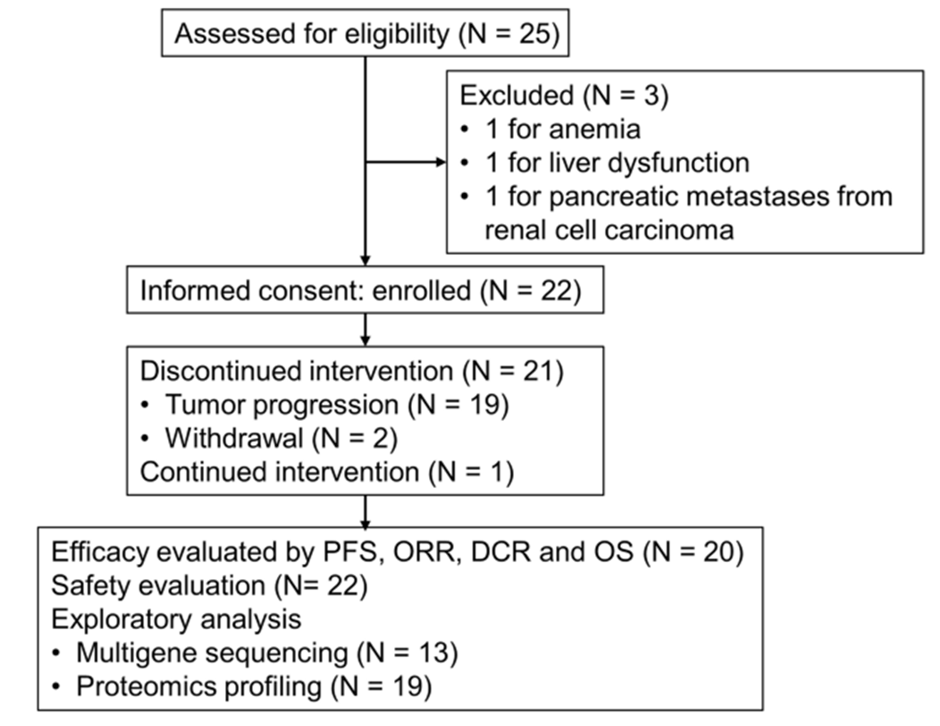
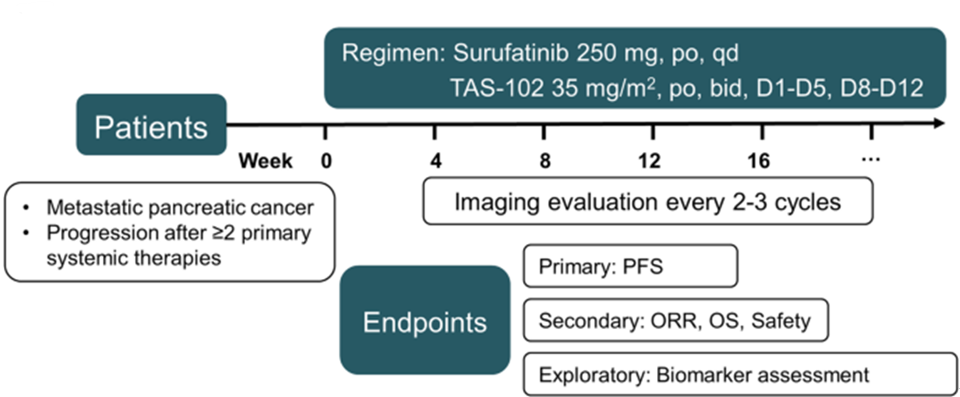
Figure 1. Schematic overview of the investigation. a) Participant flow. Out of 25 individuals assessed for suitability, 22 satisfied the entry requirements and joined the trial. Assessments of therapeutic effectiveness relied on objective response rate (ORR), disease control rate (DCR), median progression-free survival (mPFS), and median overall survival (mOS) (set suitable for efficacy analysis, N = 20). The complete group underwent safety review (N = 22). Additional investigations included next-generation sequencing of multiple genes (N = 13) and combined proteomic evaluation (N = 19). b) The illustration outlines the dosing schedule, maintained until evidence of progression or severe adverse effects. |
The trial design, incorporating updates, gained approval from the Institutional Review Board at Sun Yat-sen University Cancer Center. It adhered to the Declaration of Helsinki and Good Clinical Practice standards. Every participant gave signed consent prior to participation, and the trial received prior registration on ClinicalTrials.gov (NCT05481463). The entire author group accessed the raw data, examined it, and endorsed the submitted version.
Study procedures
Participants received TAS-102 at 35 mg/m² orally twice daily on days 1–5 and 8–12, alongside surufatinib at 250 mg orally once daily, within 28-day cycles (Figure 1b). Selection of these doses drew from earlier studies (e.g., NCT02921737, NCT05832892, NCT06361888) and insights gained from a related investigator-sponsored study directed by the current group (NCT05481476). Investigators evaluated tumor changes every eight weeks via contrast-enhanced CT or MRI scans, applying RECIST 1.1 guidelines. Therapy persisted until confirmed progression, severe side effects, clinical judgment by the investigator, or consent revocation by the patient. Before starting each new cycle, adverse events underwent evaluation and classification using physical exams and lab results, based on CTCAE version 5.0. Management of emerging side effects allowed for two tiers of dosage reductions in either agent.
Endpoints
Earlier investigational and registry-based research has repeatedly indicated very low objective response rates in individuals with metastatic pancreatic cancer who no longer respond to at least two prior systemic treatments [23, 24]. Such patterns emphasize how hard it is to detect genuine tumor reduction in these cases, given the challenge of separating actual drug effects from normal fluctuations in disease behavior. Therefore, the main outcome measure chosen was progression-free survival (PFS), calculated from the start of treatment until RECIST 1.1-confirmed progression or death from any reason (whichever came first). This endpoint better reflects ongoing disease stabilization and patient benefit across a broader timeframe than the brief activity signal provided by ORR. A key additional outcome was overall survival (OS), measured from initial dosing to death regardless of cause. Further additional measures encompassed ORR (fraction of cases with complete or partial remission) and DCR (fraction achieving complete remission, partial remission, or disease stability), all per RECIST 1.1. Evaluation also covered safety profile and patient tolerance. Additional investigations explored links between treatment results (including ORR, OS, and PFS) and genetic alterations or protein expression patterns.
Isolation of DNA and targeted sequencing
From FFPE tumor sections, DNA was obtained using the QIAamp DNA FFPE Tissue Kit (Qiagen) as directed by the supplier. Quantification occurred via Qubit 2.0 fluorometer (Thermo Fisher Scientific, USA) per protocol. As a reference, germline DNA came from peripheral blood leukocytes. Blood specimens were processed by centrifugation shortly after draw (within 2 hours) to isolate leukocyte fractions and plasma for storage. Leukocyte-derived genomic DNA was purified with the RelaxGene Blood DNA System (TianGen Biotech Co., Ltd., China) according to guidelines, followed by Qubit 2.0 quantification (Thermo Fisher Scientific, USA).
All downstream processes—such as preparing libraries, capturing targets, sequencing, handling raw data, and mapping reads—for both tumor and control samples followed identical steps.
Protein expression profiling and staining techniques
Archived pre-therapy tumor blocks in FFPE format were sent for comprehensive protein analysis to PTM BIO (Hangzhou, China). On additional FFPE material, immunohistochemistry for OCIAD2 (Ovarian Carcinoma Immunoreactive Antigen Domain-Containing Protein 2) and KRT19 employed methods from an earlier work by the team [25]. Staining results were scored via the H-score approach, combining strength of signal with percentage of positive cells. The antibodies applied were anti-OCIAD2 (dilution 1:150, ProteinTech, Cat No. 13437-1-AP) and anti-KRT19 (dilution 1:500, Servicebio, Cat No. GB11197).
Stemness assessment
The stemness signature was established using Stem.Sig, an innovative stemness marker created and confirmed by Zhang et al. through comprehensive analysis across multiple cancer types [26]. Single-sample gene set enrichment analysis (ssGSEA) was carried out with the “GSVA” R package to determine stemness scores for each individual patient. The mRNA-based stemness index for tumor samples was derived using the one-class logistic regression (OCLR) machine learning approach. In particular, a prediction model was built from pluripotent stem cell data in the Progenitor Cell Biology Consortium (PCBC) database. The resulting model coefficients were then utilized to generate stemness indices for pancreatic ductal adenocarcinoma transcriptome profiles obtained from The Cancer Genome Atlas (TCGA).
Statistical methods
This trial was a non-randomized, single-arm, exploratory study intended to assess the initial effectiveness of combining TAS-102 with surufatinib in metastatic pancreatic cancer (mPC) patients refractory to chemotherapy. The main focus was on progression-free survival (PFS) to generate preliminary evidence on efficacy and safety, which could guide the planning of future larger studies in a population without established treatment options. Due to the lack of reliable historical control data from standard therapies in this setting and the exploratory purpose of this early-phase trial, enrollment targeted 20 evaluable patients without a formal phase I component or powered sample size estimation. Allowing for a projected 10% dropout rate, the target recruitment was set at 22 patients.
Safety analyses included all patients who received at least one dose of study treatment, whereas efficacy analyses comprised those with at least one on-treatment imaging evaluation. All statistical computations and visualizations were conducted using R software (version 4.2.1) and GraphPad Prism (version 8.0; Boston, Massachusetts, USA). Comparisons of overall survival (OS) and PFS were performed with log-rank tests. Hazard ratios (HRs) along with 95% confidence intervals (CIs) for progression or death were obtained from stratified Cox proportional hazards models. Objective response rate (ORR) and disease control rate (DCR) were presented as point estimates accompanied by exact Clopper-Pearson CIs. Continuous data were reported as means (with standard deviations) or medians (with ranges), while categorical data were expressed as counts and proportions. Group differences in clinical features, mutation rates, and protein expression were evaluated using two-sided chi-square tests, Fisher’s exact tests, or Wilcoxon rank-sum tests, depending on the data type. Statistical significance was defined as a P-value below 0.05 for all tests.
Results and Discussion
Results patient population
From January 2023 to June 2024, 22 individuals with metastatic pancreatic cancer who had progressed after at least two prior lines of therapy were recruited at Sun Yat-sen University Cancer Center. All 22 were assessed for safety, and 20 who underwent at least one post-baseline imaging scan formed the efficacy population (Figure 1a). The cohort had a median age of 59.0 years, was mostly male (63.6%, 14/22), and half presented with liver metastases (11/22). The majority (63.6%, 14/22) had received exactly two prior treatment lines. Every participant had confirmed pancreatic carcinoma; 16 (72.7%) underwent resection of the primary tumor, and 4 (18.2%) harbored wild-type KRAS/NRAS (Table 1). As of the data cutoff on March 1, 2025, the median follow-up duration was 14.16 months (95% CI, 13.31–not reached), with one patient (4.5%) remaining on active treatment. Treatment discontinuation occurred primarily due to disease progression (N = 19, 86.4%) or patient decision (N = 2, 9.1%), and none stopped because of treatment-emergent adverse events (Figure 1a). In terms of previous therapies, 14 patients had been exposed to either FOLFIRINOX or AG-based regimens, one received SOXIRI, 19 had gemcitabine-containing treatments, 4 participated in early-phase trials of experimental targeted therapies, and 6 received immunotherapy combined with conventional chemotherapy.
Table 1 Clinical characteristics and baseline demographics
|
Characteristic |
(N = 22) |
|
Median age, years (range) |
59 (41–72) |
|
ECOG performance status, n (%) |
|
|
0 |
0 (0) |
|
1 |
22 (100) |
|
Sex, n (%) |
|
|
Male |
14 (63.6) |
|
Female |
8 (36.4) |
|
Number of prior treatment lines, n (%) |
|
|
2 |
14 (63.6) |
|
3 |
8 (36.4) |
|
TNM stage, n (%) |
|
|
III |
0 (0) |
|
IV |
22 (100) |
|
Location of primary tumor, n (%) |
|
|
Body/tail of pancreas |
16 (72.7) |
|
Head/neck of pancreas |
6 (27.3) |
|
Tumor histology, n (%) |
|
|
Adenocarcinoma |
22 (100) |
|
Other |
0 (0) |
|
Sites of distant metastasis, n (%) |
|
|
Liver (intrahepatic) and/or extrahepatic sites |
20 (90.9) |
|
Liver only |
2 (9.1) |
|
Surgical resection of primary tumor, n (%) |
|
|
No |
6 (27.3) |
|
Yes |
16 (72.7) |
|
MSI status, n (%) |
|
|
MSI-high |
1 (4.5) |
|
MSS (microsatellite stable) |
15 (68.2) |
|
Unknown |
6 (27.3) |
|
Gene mutations, n (%) |
|
|
RAS wild-type |
4 (18.2) |
|
KRAS/NRAS mutated |
17 (77.3) |
|
Unknown |
1 (4.5) |
|
Baseline CA19-9 level, U/ml, n (%) |
|
|
≤35 |
4 (18.2) |
|
>35 |
18 (81.8) |
Efficacy
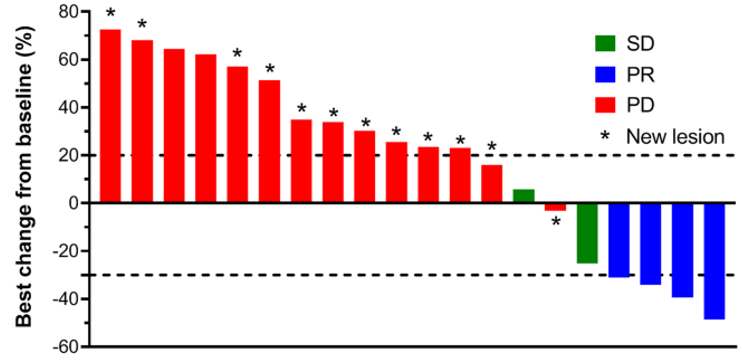
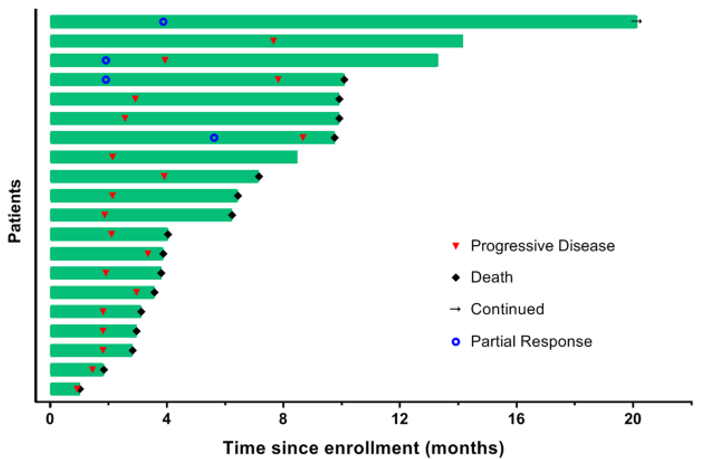
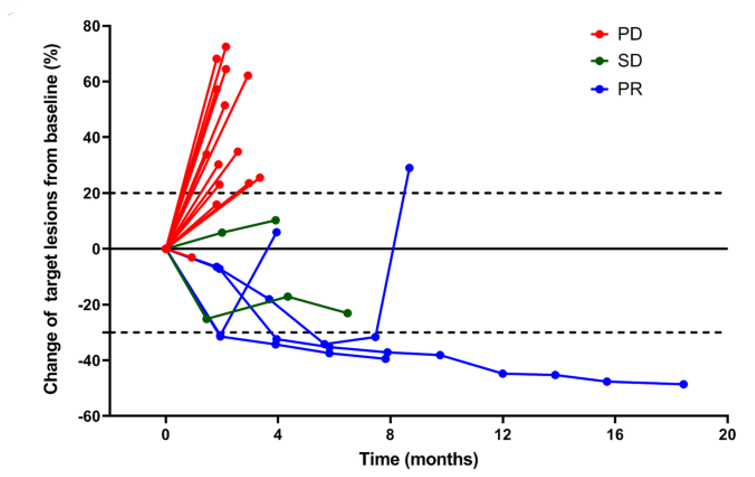
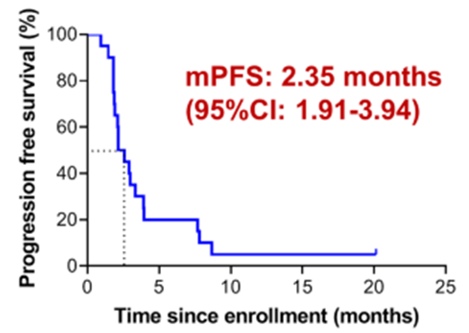
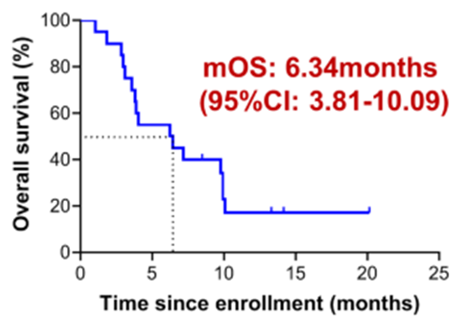
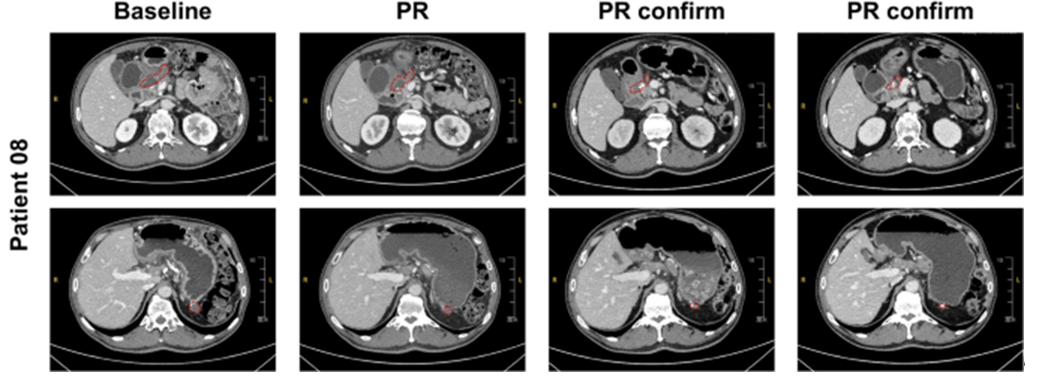
Tumor shrinkage meeting criteria for partial response was observed in four of the 20 patients assessable for efficacy, corresponding to a response rate of 20% (95% CI, 8.1%–41.6%). Individual patterns of response and treatment exposure are summarized in Figure 2, which reveals substantial heterogeneity in clinical benefit. One patient achieved sustained disease control and continued treatment for more than 20 months. When longitudinal tumor measurements were analyzed across the cohort, disease stabilization or response was achieved in six patients, resulting in a disease control rate of 30% (95% CI, 14.6%–51.9%). Survival outcomes remained limited in this heavily pretreated population. Median progression-free survival was 2.35 months (95% CI, 1.91–3.94), with only 35.0% of patients remaining progression-free at 3 months and 20.0% at 6 months. At the time of data cutoff, clinical outcomes were known for nearly all participants, as 90% had died or were no longer under follow-up. Median overall survival reached 6.34 months (95% CI, 3.81–10.09). Corresponding overall survival rates were 80.0% at 3 months and 55.0% at 6 months. Subsequent anticancer treatment was administered to fewer than half of the patients after study drug discontinuation. Eight individuals (40%) received additional systemic therapy, most frequently nanoliposomal irinotecan, which accounted for half of post-study regimens. Inclusion of all enrolled patients in the full analysis population (N = 22) yielded median progression-free and overall survival durations of 2.74 months and 5.14 months, respectively. Clinical benefit was particularly notable in several individual cases. One patient (No. 08), who experienced early relapse with local recurrence and peritoneal spread during adjuvant FOLFIRINOX following curative-intent surgery, showed continued disease progression after AG combined with targeted therapy. In contrast, initiation of TAS-102 plus surufatinib led to rapid tumor regression after two cycles, with ongoing radiographic control at last assessment. The remaining partial responses were documented in one patient with peritoneal metastases and two patients with lung-only metastatic disease.
|
|
|
a) |
|
|
|
b) |
|
|
|
c) |
|
Figure 2. Antitumor activity. a) The waterfall diagram displays the greatest proportional variation in summed target lesion measurements relative to baseline among evaluable participants (N = 20). Columns are annotated by the best overall response category. Appearance of new tumor sites, denoted by a star symbol, was classified as disease progression. Imaging-based response assessments for three patients were derived from scans performed at their respective local centers. Patients with stable disease, partial response, or progressive disease are indicated in green, blue, and red, respectively. b) Time-to-event outcomes for progression-free survival in the full cohort (N = 20) are summarized in the swimmer plot. Treatment responses are marked with blue dots for partial response and red downward-pointing triangles for progression. Bar length corresponds to the interval from trial enrollment to progression or death, with fatal events identified by black diamond symbols. c) The spider plot illustrates patient-level trajectories of target lesion size over time, expressed as percentage change from baseline (N = 20). Response categories—stable disease, partial response, and progressive disease—are again distinguished by green, blue, and red coloring. |
|
|
|
|
|
a) |
b) |
|
|
|
||
|
c) |
||
|
Figure 3. Overall survival and progression-free. a) Progression-free survival for all enrolled patients (N = 20) was analyzed using the Kaplan–Meier method. b) Overall survival for the same cohort (N = 20) was likewise estimated by Kaplan–Meier analysis. c)Serial computed tomography images from Patient No. 08, who continued to receive study treatment, are shown at baseline and at three subsequent follow-up time points. Areas outlined by irregular polygons correspond to recurrent disease at the surgical bed and metastatic involvement of the peritoneum. |
||
Safety
Treatment-emergent adverse events occurred in every patient enrolled in the study. The most frequently reported adverse events of any severity (incidence ≥10%) were hematologic in nature, including anemia (59.1%), neutropenia (54.6%), leukopenia (50.0%), and lymphopenia (45.5%) (Table 2). Severe toxicities (grade 3–4) were predominantly bone marrow–related and consisted mainly of neutropenia (31.8%), lymphopenia (13.6%), and anemia (9.1%) (Table 2). Elevated blood pressure was documented in two patients, including one case each of grade 2 and grade 3 hypertension. No treatment-related deaths or grade 5 adverse events were recorded.
Most adverse events were attributed to TAS-102 exposure. Serious adverse events were uncommon, occurring in two patients (9.1%), with a total of three reported events: sinus bradycardia, intra-abdominal infection, and gastrointestinal bleeding (Table 2).
Table 2. Summary of treatment-related adverse events and serious adverse events.
|
Adverse Event |
Grade 3–4, N (%) |
Any Grade, N (%) |
|
Total |
11 (50.0) |
22 (100.0) |
|
Leukocytopenia |
1 (4.55) |
11 (50.00) |
|
Lymphocytopenia |
3 (13.64) |
10 (45.45) |
|
Anemia |
2 (9.09) |
13 (59.09) |
|
Neutropenia |
7 (31.82) |
12 (54.55) |
|
Proteinuria |
0 |
8 (36.36) |
|
Hyponatremia |
0 |
8 (36.36) |
|
Abnormality in ECG |
0 |
9 (40.91) |
|
Occult blood |
0 |
8 (36.36) |
|
Hypochloremia |
0 |
4 (18.18) |
|
Fatigue |
0 |
5 (22.73) |
|
Increased AST level |
0 |
4 (18.18) |
|
Nausea |
0 |
4 (18.18) |
|
Diarrhea |
1 (4.55) |
4 (18.18) |
|
Increased TSH level |
0 |
3 (13.64) |
|
Abdominal pain |
0 |
3 (13.64) |
|
Hyperuricemia |
0 |
4 (18.18) |
|
Vomiting |
0 |
4 (18.18) |
|
Hyperbilirubinemia |
0 |
3 (13.64) |
|
Sinus bradycardia |
0 |
1 (4.55) |
|
Abdominal infection |
1 (4.55) |
1 (4.55) |
|
Gastrointestinal bleeding |
1 (4.55) |
1 (4.55) |
|
Abdominal discomfort |
0 |
3 (13.64) |
|
Increased LDH level |
0 |
3 (13.64) |
Exploratory evaluation of clinical correlates
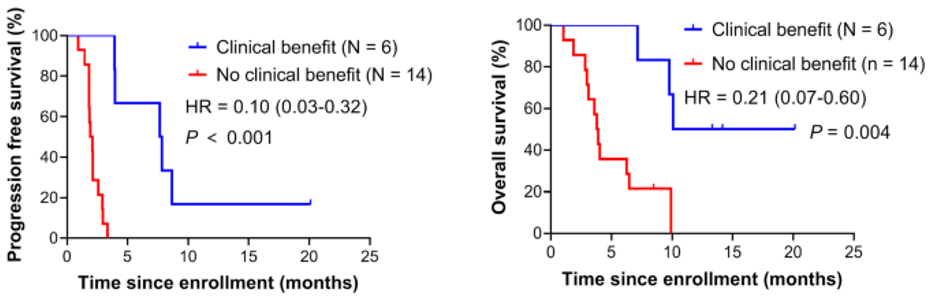
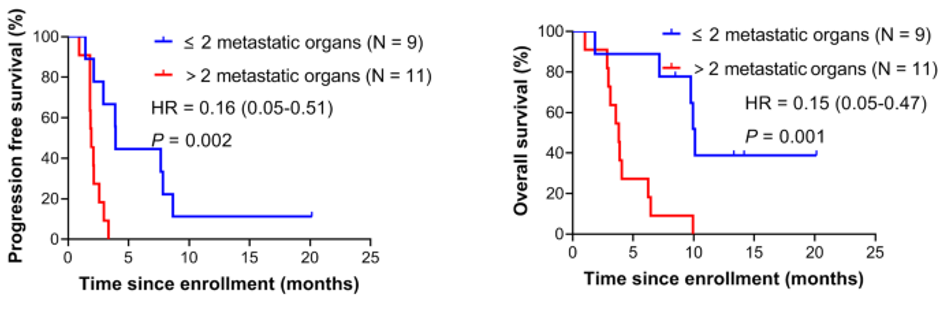
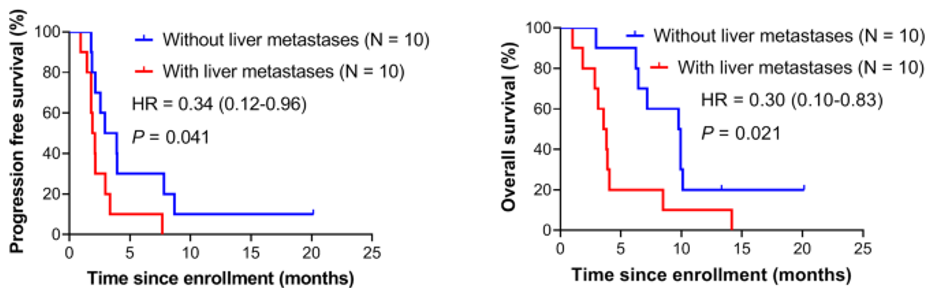
We explored whether selected baseline clinical features were associated with treatment outcomes. Patients who achieved tumor control, defined as stable disease or partial response (n = 6), were classified as having derived clinical benefit. This subset experienced substantially prolonged survival compared with those without benefit. Median progression-free survival extended to 7.74 months versus 2.00 months, corresponding to a hazard ratio of 0.10 (95% CI, 0.03–0.32; P < 0.001). Median overall survival was likewise markedly improved, reaching 15.12 months compared with 3.84 months (HR = 0.21, 95% CI, 0.07–0.60; P = 0.004) (Figure 4a). Extent of metastatic spread emerged as another relevant factor. Patients with metastatic disease confined to no more than two organs demonstrated superior outcomes relative to those with involvement of more than two organs. In this group, median progression-free survival was 3.94 months compared with 1.91 months (HR = 0.16, 95% CI, 0.05–0.51; P = 0.002), while median overall survival was 10.09 months versus 3.81 months (HR = 0.15, 95% CI, 0.05–0.47; P = 0.001) (Figure 4b). Patterns of metastatic sites also influenced prognosis. Absence of liver metastases was associated with longer progression-free survival (3.42 vs. 2.01 months; HR = 0.34, 95% CI, 0.12–0.96; P = 0.041) and extended overall survival (9.84 vs. 3.70 months; HR = 0.30, 95% CI, 0.10–0.83; P = 0.021) compared with patients who had hepatic involvement (Figure 4c). Baseline tumor marker levels were additionally examined. Patients with pretreatment CA19-9 values below the cohort median exhibited a statistically significant advantage in overall survival, although no corresponding difference was detected for progression-free survival. Other evaluated baseline characteristics—including prior lines of therapy, presence of peritoneal metastases, and surgical resection of the primary tumor—showed no meaningful association with either progression-free or overall survival.
|
|
|
a) |
|
|
|
b) |
|
|
|
c) |
|
Figure 4. Subgroup survival analyses. a) Kaplan–Meier curves comparing progression-free survival (PFS) and overall survival (OS) between patients who achieved clinical benefit (N = 6) and those who did not (N = 14). b) Kaplan–Meier estimates of PFS and OS stratified by metastatic burden, contrasting patients with involvement of more than two organs (N = 11) versus two or fewer organs (N = 9). c) Kaplan–Meier survival analyses according to hepatic involvement, comparing patients with liver metastases (N = 10) to those without liver metastases (N = 10). Statistical comparisons across all subgroups were conducted using the log-rank test. |
Genomic alterations and potential predictive markers
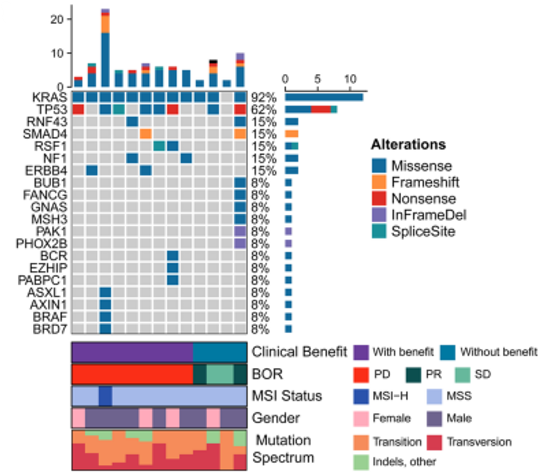
Comprehensive genomic profiling was available for 13 patients, in whom sequencing of 1,021 cancer-associated genes was performed at our institution. The distribution of somatic alterations across these patients is summarized in Figure 5a. KRAS mutations were nearly ubiquitous, occurring in 12 of 13 cases (92%), while TP53 alterations were detected in 8 patients (62%). Additional recurrently altered genes among the top 20 included RNF43, SMAD4, RSF1, NF1, and ERBB4.
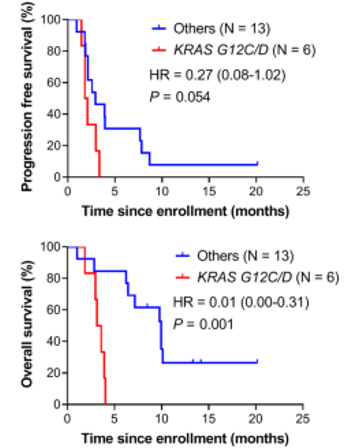
Given the limited sample size, no statistically meaningful differences in mutation frequencies were observed between patients who experienced clinical benefit and those who did not (Figure 5a). Nevertheless, survival analyses suggested that tumors harboring KRASG12C or KRASG12D variants were associated with less favorable outcomes, as reflected by shorter progression-free and overall survival compared with other molecular subgroups (Figure 5b). When stratified by overall RAS mutation status, progression-free survival did not differ significantly between wild-type and mutated tumors; however, overall survival was significantly prolonged in patients with RAS wild-type disease relative to those with RAS alterations.
|
|
|
||
|
a) |
b) |
||
|
|
|
|
|
|
c) |
d) |
e) |
|
|
|
|
||
|
f) |
g) |
||
|
|
|
||
|
h) |
i) |
||
|
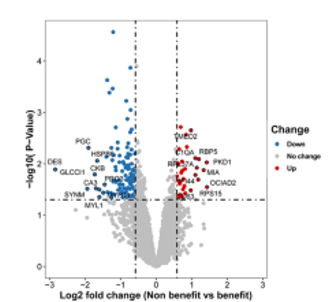
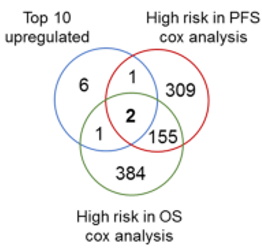
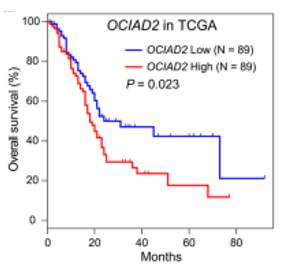
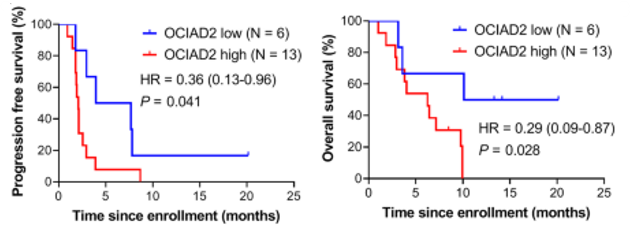
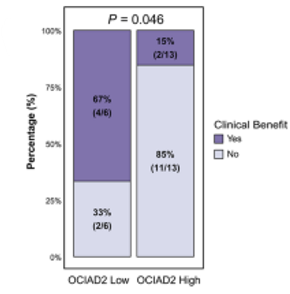
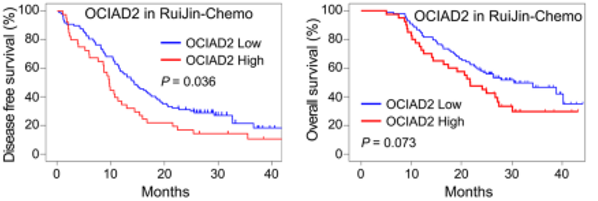
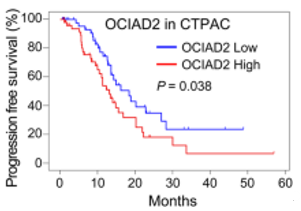
Figure 5. Multi-omics characterization and outcome associations. a) Overview of recurrent somatic alterations, displaying the 20 most commonly mutated genes identified in the study cohort. b) Survival comparison using Kaplan–Meier curves for progression-free and overall survival between patients carrying KRASG12C or KRASG12D substitutions (N = 6) and those without these variants (N = 13). c) Volcano plot summarizing protein abundance differences between patients with and without clinical benefit; log₂ fold change represents mean relative protein expression. d) Intersection of proteins showing the highest overexpression with those significantly linked to both progression-free and overall survival. e) Relationship between OCIAD2 expression and overall survival in pancreatic cancer cases derived from the TCGA dataset. f) Kaplan–Meier analysis of PFS and OS stratified by elevated (N = 13) versus reduced (N = 6) OCIAD2 protein expression. g) Distribution of clinical benefit across low and high OCIAD2 expression groups. h) Disease-free survival and overall survival among chemotherapy-treated pancreatic cancer patients from the RuiJin cohort, grouped by OCIAD2 expression levels. i) Progression-free survival analysis based on OCIAD2 expression in pancreatic cancer patients from the CPTAC (Clinical Proteomic Tumor Analysis Consortium) database. Statistical significance in panel g) was assessed using Fisher’s exact test, whereas survival comparisons in panels b, e, f, h, and i were performed with the log-rank test. |
|||
Proteomic profiling in metastatic pancreatic cancer
Tumor proteomic data were available for 19 patients and were analyzed according to treatment outcome, separating patients into benefit (n = 6) and non-benefit (n = 13) categories. Across all samples, 8,298 distinct proteins were quantified. Comparative analysis demonstrated pronounced proteomic differences between outcome groups, with 35 proteins exhibiting increased abundance and 123 showing reduced abundance in tumors from non-benefiting patients relative to those with clinical benefit (Figure 5c). Subsequent survival-based screening identified 852 proteins whose expression levels were significantly associated with progression-free or overall survival (Figure 5d). Among the ten proteins most strongly enriched in the non-benefit group, OCIAD2 and TMED2 emerged as consistently associated with adverse PFS and OS (Figures 5c and 5d). External validation using TCGA data revealed that elevated OCIAD2 expression correlated with shortened overall survival (Figure 5e), whereas TMED2 expression showed no statistically meaningful survival association. Given prior evidence implicating OCIAD2 in pancreatic tumor progression through activation of the Akt signaling pathway [27], subsequent analyses focused on this protein. Patients with higher OCIAD2 expression experienced significantly worse progression-free and overall survival compared with those exhibiting lower expression (Figure 5f). Consistent with these findings, disease control was achieved in 67% of patients with low OCIAD2 levels, compared with only 15% in the high-expression group (Figure 5g). To further substantiate these observations, OCIAD2 expression was evaluated in independent datasets, including the RuiJin proteomic cohort [21] and the CPTAC database. In the RuiJin cohort, reduced OCIAD2 expression was significantly associated with prolonged disease-free survival among patients receiving chemotherapy, and overall survival showed a favorable trend in the low-expression group (Figure 5h). Analyses of CPTAC samples demonstrated a concordant pattern, with OCIAD2 expression consistently associated with both progression-free and overall survival (Figure 5i). Collectively, these data indicate that elevated OCIAD2 expression is linked to unfavorable prognosis and may contribute to resistance to anticancer therapy in pancreatic cancer.
Elevated OCIAD2 expression in patients without clinical benefit
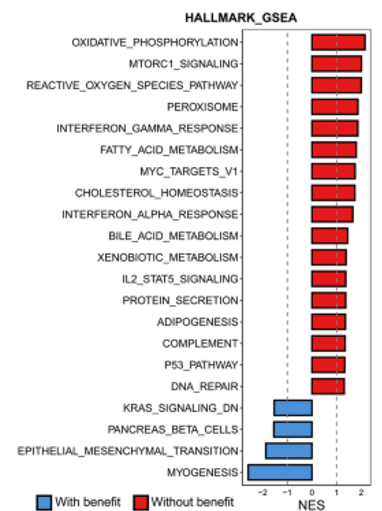
To gain insight into the biological processes associated with OCIAD2-linked treatment resistance, gene set enrichment analysis was performed comparing tumors from benefit and non-benefit groups. Tumors from non-responding patients demonstrated significant enrichment of metabolic pathways, including oxidative phosphorylation, reactive oxygen species (ROS) signaling, and fatty acid catabolism (Figure 6a). Additional pathway analyses revealed upregulation of ROS detoxification mechanisms and metabolic programs such as mitochondrial respiratory electron transport in the non-benefit group. Consistently, Reactome-based enrichment analyses identified ROS-related pathways and biological oxidation processes as dominant features in tumors from non-responders.
|
|
|
||
|
b) |
|||
|
|
|||
|
a) |
c) |
||
|
|
|||
|
d) |
|||
|
|
|
||
|
e) |
f) |
||
|
|
|
||
|
g) |
h) |
||
|
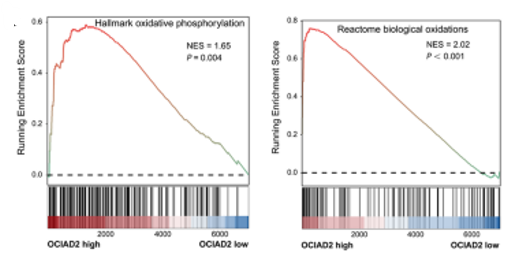
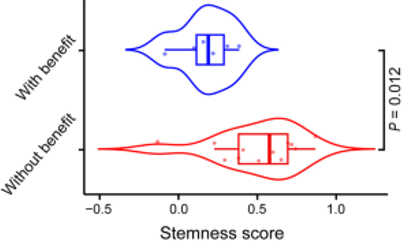
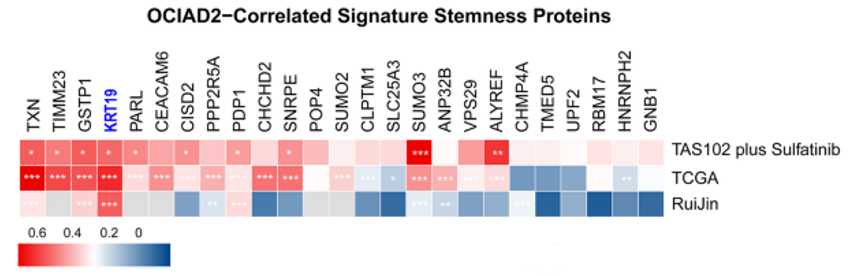
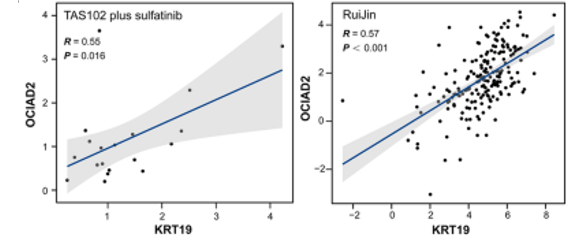
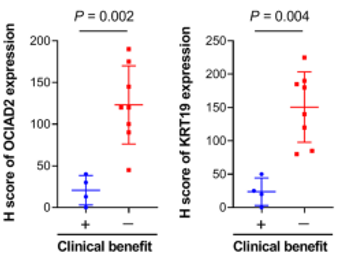
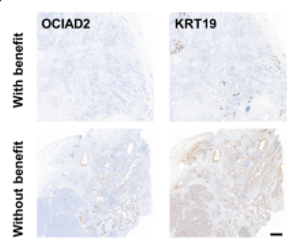
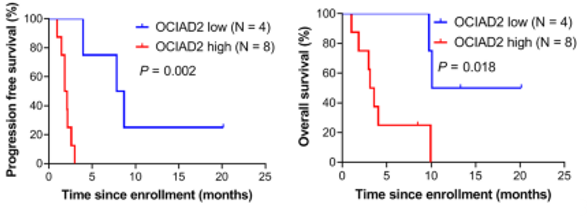
Figure 6. Functional relevance of OCIAD2 in pancreatic cancer. a) Comparative analysis of cancer hallmark–related pathways enriched in tumors from patients with and without clinical benefit. b) Gene set enrichment analysis illustrating differential activation of oxidative phosphorylation and Reactome biological oxidation pathways between tumors with low versus high OCIAD2 expression. c) Comparison of stemness scores between patients who derived clinical benefit and those who did not. d) Correlation matrix depicting associations between OCIAD2 expression and genes included in the stemness signature across the RuiJin cohort, TCGA dataset, and the present study cohort; correlation strength is indicated by color intensity, and statistical significance is denoted by pentagram symbols. e) Correlation analyses between OCIAD2 and KRT19 expression in the study cohort and the RuiJin cohort. f) Quantitative H-score assessment of OCIAD2 and KRT19 protein expression in tumor specimens from 12 patients with available samples following proteomic profiling, stratified by clinical benefit status. g) Representative immunohistochemical staining images demonstrating OCIAD2 and KRT19 expression in tumors from responders and non-responders. Scale bars represent 1000 μm. h) Kaplan–Meier survival curves showing progression-free survival (PFS) and overall survival (OS) according to low versus high OCIAD2 H-score levels. Statistical comparisons in panels c and f were performed using the Wilcoxon rank-sum test. Pearson correlation analysis was applied for panels d and e, while survival differences in panel h were evaluated using the log-rank test. Significance thresholds are indicated as *P < 0.05, **P < 0.01, and ***P < 0.001. |
|||
When patients were stratified based on OCIAD2 protein abundance, tumors with elevated OCIAD2 expression demonstrated marked enrichment of oxidative phosphorylation–related processes, biological oxidation pathways, and reactive oxygen species (ROS) signaling (Figure 6b). These findings suggest a potential involvement of OCIAD2 in regulating redox homeostasis in pancreatic cancer. Consistently, KEGG pathway analyses of pancreatic cancer samples from the CPTAC database revealed increased activity of oxidative phosphorylation and ROS-associated pathways in cases with high OCIAD2 expression.
Given prior evidence linking ROS signaling to maintenance of tumor stemness and resistance to chemotherapy in multiple solid malignancies, we next examined whether OCIAD2 expression was associated with these phenotypes. The stemness score previously established by our group [26] was significantly elevated in patients who failed to achieve clinical benefit compared with those who responded to treatment (Figure 6c). Independent validation using the RuiJin cohort and TCGA dataset further confirmed that higher OCIAD2 expression was significantly associated with increased stemness scores. To identify specific stemness-related genes associated with OCIAD2, we integrated expression data from the study cohort, RuiJin cohort, and TCGA database (Figure 6d). Among the evaluated markers, KRT19 consistently showed a strong positive correlation with OCIAD2 expression across all datasets, including both the study and RuiJin cohorts (Figures 6d and 6e) as well as the TCGA dataset.
Finally, protein expression of OCIAD2 and KRT19 was examined by immunohistochemistry in tumor samples from 12 patients with available material following proteomic analysis. Both OCIAD2 and KRT19 were expressed at significantly higher levels in tumors from patients who did not respond to TAS-102 combined with surufatinib compared with responders (Figures 6f and 6g). A positive correlation between OCIAD2 and KRT19 protein expression was observed within this subset of patients (Figure 6g). Importantly, elevated OCIAD2 expression was associated with significantly shorter progression-free and overall survival in these 12 patients (Figure 6h). Taken together, these findings indicate that OCIAD2, in concert with KRT19, may contribute to chemotherapy resistance in pancreatic cancer treated with TAS-102 plus surufatinib, underscoring the need for further mechanistic and translational investigations.
As advances in first- and second-line systemic therapies have extended disease control, a growing proportion of patients with metastatic pancreatic cancer (mPC) maintain adequate performance status even after progression on standard regimens. This evolving clinical landscape underscores an urgent unmet need for effective therapies beyond second line [28]. In this context, we conducted the first prospective evaluation of TAS-102 combined with surufatinib in patients receiving third-line or later treatment. This regimen achieved a median progression-free survival (mPFS) of 2.35 months (95% CI: 1.91–3.94) and a median overall survival (mOS) of 6.34 months (95% CI: 3.81–10.09). Encouragingly, objective responses and disease stabilization were observed despite extensive prior therapy, with an objective response rate of 20% and a disease control rate of 30%. Notably, patients with limited metastatic burden (fewer than two involved organs) derived greater benefit, with mPFS and mOS reaching 3.94 and 10.09 months, respectively. In addition, OCIAD2 emerged as a candidate biomarker with potential utility for identifying patients more likely to benefit from this therapeutic approach.
In the absence of established standards for later-line mPC treatment, retrospective analyses indicate that therapeutic decisions typically rely on conventional cytotoxic agents such as fluoropyrimidines or gemcitabine [28, 29], while molecularly targeted therapies, including erlotinib, are infrequently used (<10%) [28]. Other reported strategies include combining chemotherapy with targeted agents or immunotherapy [29], use of nanoliposomal irinotecan (nal-IRI) [30, 31], administration of genotype-matched inhibitors in selected patients [32], or enrollment in early-phase clinical trials [33]. Outcomes from these approaches remain suboptimal. For example, a retrospective cohort of 251 patients receiving third-line therapy reported mPFS and mOS of only 2.03 and 5.5 months, respectively [28]. Even intensified multimodal approaches, such as dual immune checkpoint blockade combined with stereotactic body radiotherapy, achieved mPFS and mOS of merely 1.6 and 3.8 months [33]. These findings reflect the formidable biological resistance of pancreatic cancer, a challenge widely acknowledged in the literature [34].
Against this backdrop, the survival outcomes observed with TAS-102 plus surufatinib in our prospective study compare favorably with prior reports. Previous chemotherapy-based regimens in later-line settings have yielded mPFS values ranging from 2.03 to 4.4 months [28–32], while a prospective trial evaluating CBP501 in combination with nivolumab and cisplatin reported an mPFS of 2.4 months in chemotherapy-refractory mPC [35]. Importantly, our cohort represented a heavily pretreated population: 20% had participated in early-phase trials of novel targeted agents and 30% had received immunotherapy combined with standard chemotherapy prior to enrollment. These patterns highlight both the refractory disease biology and the scarcity of effective treatment options. All prior therapies were completed at least four weeks before study initiation, reducing the likelihood that earlier treatments substantially influenced the observed outcomes. Although 40% of patients received additional therapies after discontinuing the study regimen, potentially contributing to overall survival, progression-free survival—unaffected by subsequent treatment—remained clinically meaningful.
For patients previously treated with gemcitabine-based regimens, landmark trials such as CONKO-003 [36] and NAPOLI-1 [9] demonstrated that FOLFOX-6 or nal-IRI significantly improved survival compared with fluoropyrimidine monotherapy, achieving mOS of approximately 6 months and mPFS near 3 months. Importantly, our study population had progressed after both fluoropyrimidine- and gemcitabine-based treatments, placing them at an even more advanced disease stage. Despite this, survival outcomes with TAS-102 plus surufatinib were comparable to those reported in CONKO-003 and NAPOLI-1, supporting the potential role of this oral combination as a practical later-line option for patients with preserved functional status.
While some retrospective studies have reported mOS exceeding 9 months [30, 31], their interpretability is limited by small sample sizes and inherent selection bias. Overall, the efficacy observed in our trial aligns with outcomes reported in both retrospective [28, 29] and prospective [32, 33, 35] studies, although direct comparisons are constrained by differences in patient populations and study designs. A notable advantage of the present regimen is its oral administration, which may be particularly appealing for patients who have already undergone prolonged courses of intravenous therapy and often experience declining tolerance with disease progression. Consistent with expectations, treatment-related toxicities were manageable, with hematologic adverse events primarily attributable to TAS-102–related myelosuppression.
Our findings further reinforce the prognostic relevance of metastatic pattern in mPC. Patients with liver metastases experienced inferior survival, consistent with prior observations, and those with more extensive metastatic involvement also fared worse. In contrast, factors such as performance status, primary tumor location, and peritoneal dissemination did not show significant associations with outcome. These observations emphasize the importance of careful patient selection when considering this regimen.
From a mechanistic perspective, mPC is characterized by a dense desmoplastic stroma and an immunosuppressive microenvironment enriched with tumor-associated macrophages (TAMs), both of which contribute to therapeutic resistance and metastatic dissemination [37, 38]. Surufatinib, through inhibition of CSF-1R, may alter TAM distribution while simultaneously normalizing tumor vasculature, thereby enhancing intratumoral delivery of cytotoxic agents such as TAS-102. This dual mechanism provides a strong biological rationale for combining surufatinib with chemotherapy in pancreatic cancer. Moreover, surufatinib’s immunomodulatory properties have demonstrated clinical activity in combination with immune checkpoint inhibitors in gastrointestinal malignancies [19], raising the possibility that similar strategies could be extended to mPC.
Beyond clinical efficacy, our multi-omics analyses provide novel insights into resistance mechanisms. OCIAD2 dysregulation has been reported across multiple malignancies, including ovarian mucinous tumors [39], lung adenocarcinoma [40], and hepatocellular carcinoma [41]. In pancreatic cancer, OCIAD2 overexpression has been shown to drive tumor progression via Akt signaling activation [27], indicating context-specific oncogenic functions. More recently, OCIAD2 has been identified as a mitochondrial complex III assembly factor essential for maintaining electron transport chain integrity [42]. In line with these findings, our analyses revealed altered mitochondrial metabolism in non-responders, including dysregulated oxidative phosphorylation (OXPHOS) and reactive oxygen species (ROS) pathways.
Elevated OXPHOS activity and ROS signaling are increasingly recognized as hallmarks of chemoresistant cancer cells [43]. Moderate ROS levels are critical for sustaining cancer stem cell (CSC) populations and their resistance to therapy [44]. In pancreatic cancer, CSCs rely heavily on OXPHOS to maintain their functional properties [45, 46]. Experimental work by Valle et al. demonstrated that forcing pancreatic cancer cells to depend on OXPHOS enhances stemness-associated traits, tumorigenicity, immune evasion, and drug resistance [46]. Consistent with this paradigm, we observed significantly higher stemness scores in non-responders, along with a strong association between OCIAD2 expression and KRT19, a marker previously linked to pancreatic cancer stemness [47]. These data suggest that OCIAD2 overexpression may promote mitochondrial metabolic reprogramming, reinforcing stem-like properties and contributing to resistance to TAS-102 plus surufatinib.
Several limitations of this study should be acknowledged. As a single-arm, hypothesis-generating phase II trial with a small sample size (N = 22), the findings require validation in larger, randomized studies. Formal sample size calculations were not performed due to the lack of established benchmarks in this clinical setting. Additionally, tumor responses were investigator-assessed rather than centrally reviewed, which may have introduced bias. Finally, biomarker analyses were exploratory and based primarily on computational approaches, without functional validation in experimental models. These results should therefore be interpreted cautiously.
Conclusion
In conclusion, this study provides the first prospective evidence supporting the clinical activity of an all-oral regimen combining TAS-102 and surufatinib in heavily pretreated mPC. Through integrated genomic and proteomic analyses, we identified potential biological determinants of treatment resistance, particularly implicating OCIAD2-driven metabolic and stemness pathways. Together, these findings highlight both the therapeutic promise of this combination and the importance of continued translational research to improve outcomes in this highly lethal disease.
Acknowledgments: None
Conflict of Interest: None
Financial Support: None
Ethics Statement: None