Human papillomavirus (HPV)–based testing has become the preferred strategy for population-level cervical cancer (CC) screening. Compared with HPV DNA assays, detection of HPV E6/E7 mRNA using the Aptima HPV (AHPV) test offers improved specificity, making it a promising option for primary screening. However, evidence regarding its performance across different age groups and in combination with various triage strategies remains limited. This study assessed the age-dependent effectiveness of AHPV testing and compared multiple triage approaches with cytology to identify optimal screening strategies for Chinese women. Women participating in community-based cervical cancer screening programs were enrolled from 34 sites in Liaoning Province and Qingdao City, China, between April 2018 and December 2021. All participants underwent both liquid-based cytology (LBC) and AHPV testing as initial screening tests. Those with abnormal findings on either test were referred for colposcopic evaluation. HPV genotyping (AHPV-GT) was performed for all HPV-positive samples. Outcomes of interest included age-stratified HSIL+ detection rates, colposcopy referral proportions, and diagnostic accuracy metrics (sensitivity and specificity). Comparative analyses of AHPV-based screening and different triage strategies were conducted across predefined age categories. Among 9,911 women included in the final analysis, abnormal cytology was observed in 6.1%–8.0% of participants, with the highest frequency in the 45–54-year age group. HPV prevalence increased with age and peaked among women aged 55–64 years, exceeding that observed in women aged 35–44 and 45–54 years (14.1% vs. 12.2% and 11.6%, respectively; P = 0.048 and P = 0.002). In women aged 35–44 years, AHPV testing demonstrated markedly superior sensitivity for HSIL+ detection compared with LBC (96.6% [95% CI: 89.7–100.0] vs. 65.5% [95% CI: 48.3–82.8], P < 0.001). Implementation of AHPV genotyping with reflex LBC triage resulted in a higher HSIL+ detection rate than cytology alone (9.6‰ vs. 7.3‰) while simultaneously lowering colposcopy referrals (5.1% vs. 6.1%). In contrast, among women aged 45–54 years, HSIL+ detection using this triage strategy was marginally lower than that achieved by LBC alone (6.2‰ vs. 6.6‰). For women aged 55–64 years, AHPV testing again showed significantly greater sensitivity than cytology (97.2% [95% CI: 91.7–100.0] vs. 66.7% [95% CI: 50.0–80.6], P = 0.003). No statistically significant difference was observed between AHPV-GT with reflex LBC triage and LBC alone in terms of overall discriminatory ability, as reflected by comparable AUC values. The diagnostic performance of AHPV-based primary screening and subsequent triage approaches varied substantially by age. AHPV testing appears to be a reliable primary screening method for women aged 35–44 years and 55–64 years, whereas the addition of HPV genotyping followed by reflex cytology may provide particular benefit for women in the 35–44-year age group.
Introduction
Cervical malignancy continues to represent a substantial public health challenge for women worldwide, ranking among the leading causes of both cancer incidence and mortality [1]. Extensive evidence has established long-term infection with oncogenic human papillomavirus (HPV) genotypes as the indispensable initiating event in the development of cervical cancer [2]. This etiological understanding has driven a paradigm shift in population-based screening, with HPV-centered strategies increasingly replacing cytology-only approaches for the early identification of cervical neoplasia [3-5]. At present, regulatory approval by the U.S. Food and Drug Administration encompasses four HPV assays, consisting of one messenger RNA–based platform and three DNA-based tests [6].
Among available technologies, detection of HPV E6/E7 mRNA using the Aptima HPV (AHPV) assay has emerged as a clinically attractive alternative to DNA-based testing. Prior studies have shown that AHPV offers comparable sensitivity for identifying clinically significant cervical lesions, including CIN2+ and CIN3+, while providing improved specificity, thereby reducing false-positive results [7, 8]. Moreover, longitudinal evidence supports the feasibility of using AHPV as a primary screening tool at extended screening intervals of approximately five years when clinician-collected cervical samples are used [9].
Despite these advantages, HPV-based screening presents inherent challenges due to the transient nature of many HPV infections. A substantial proportion of HPV infections resolve without intervention and never progress to precancerous or malignant disease, particularly among younger women [10]. Consequently, international guidelines recommend restricting primary HPV screening to women aged 30 years or older to minimize overdiagnosis and unnecessary follow-up [11]. Supporting this recommendation, pooled analyses have demonstrated more favorable screening performance in women aged 30–35 years and above, a population characterized by lower HPV prevalence than younger cohorts [12]. However, epidemiological patterns in China diverge from those observed in many Western countries. National data indicate a bimodal age distribution of HPV infection, with a second prevalence peak occurring in women aged 55–64 [13, 14]. In parallel, rapid population aging has led to increased emphasis on cervical cancer screening among older women in China [15]. The resurgence of HPV detection later in life is frequently associated with transient or reactivated infections, complicating clinical decision-making and triage strategy selection in this age group. Importantly, robust, large-scale prospective data examining the age-specific diagnostic performance of AHPV testing are limited.
In response to these unresolved issues, the present study was designed to compare age-stratified outcomes of primary AHPV screening with those of cytology alone and to evaluate the effectiveness of multiple age-adapted triage strategies in order to inform optimal cervical cancer screening approaches for Chinese women.
Materials and Methods
Study population
This community-based investigation was conducted between April 2018 and December 2021 across several screening regions in northeastern and eastern China. Participants were recruited from urban areas in Shenyang City and Benxi County, the Sujiatun District of Liaoning Province, and Qingdao City. Women were eligible for inclusion if they had resided in the screening area for more than three years, were between 35 and 64 years of age, had no history of severe systemic illness or psychiatric disease, and had not previously undergone hysterectomy, pelvic radiotherapy, or treatment for cervical cancer. Additional inclusion criteria required voluntary participation and the ability to complete standardized questionnaires. Women who were pregnant, breastfeeding, or whose cervical samples were inadequate for cytological or HPV testing were excluded from the analysis.
Participants were stratified into three age categories reflecting reproductive status: 35–44 years (reproductive age), 45–54 years (perimenopausal), and 55–64 years (postmenopausal). Ethical approval for the study was granted by the institutional ethics committee (approval number: 20180106), and written informed consent was obtained from all participants prior to enrollment.
Cytological examination
Cervical specimens were collected using a cytobrush and immediately placed into PreservCyt transport medium (Hologic Inc., Marlborough, MA, USA). The same samples were utilized for both liquid-based cytology (LBC) and HPV testing. Cytological processing and interpretation were performed using the ThinPrep® system (Hologic Inc.), and diagnostic categories were assigned in accordance with the 2014 Bethesda System guidelines [16].
HPV mRNA testing and genotype analysis
Following cytological preparation, residual cervical cell material was analyzed in a blinded manner using the Aptima® HPV assay. This FDA-approved test detects E6/E7 mRNA transcripts from 14 oncogenic HPV types, including HPV16, 18, 31, 33, 35, 39, 45, 51, 52, 56, 58, 59, 66, and 68. All samples testing positive for high-risk HPV were subsequently subjected to genotyping with the Aptima® HPV 16/18/45 genotype assay (AHPV-GT; Gen-Probe, Hologic, San Diego, CA, USA), which specifically identifies HPV16 and a subset of HPV18 and HPV45 infections [17]. All laboratory analyses were conducted strictly in accordance with the manufacturer’s instructions.
Colposcopy and biopsy procedures
All colposcopic examinations were conducted by experienced and well-trained specialists. The criteria for referring patients to colposcopy included: (1) a cytological finding of atypical squamous cells of undetermined significance (ASC-US) or any more severe abnormality; (2) a positive HPV test result; (3) immediate colposcopy if any visible lesions were detected, irrespective of screening test results. Biopsies directed by colposcopy were performed whenever abnormal epithelial areas were identified. Histological findings from biopsies were classified into three groups: normal (including no pathological changes or cervicitis), low-grade squamous intraepithelial lesions (LSIL), and high-grade squamous intraepithelial lesions or more severe (HSIL+). Confirmation of HSIL involved immunohistochemistry for p16 and Ki-67. In cases where cytology showed ASC-H, HSIL, or atypical glandular cells (AGC) but colposcopy revealed no visible lesions, random biopsies were taken at the 3, 6, 9, and 12 o'clock positions on the cervix, along with endocervical curettage. Patients with cytology indicating ASC-US or LSIL, no HPV 16/18 infection, and a fully normal colposcopic appearance did not receive a biopsy and were classified as having "no HSIL" histologically. Similarly, those with negative results in co-testing were assigned a "no HSIL" status.
Outcome measures
The primary clinical endpoint was histologically confirmed HSIL+. Positivity in liquid-based cytology (LBC) at initial screening was defined as ASC-US or higher. Positivity in the Aptima HPV (AHPV) test at primary screening indicated any high-risk HPV (hr-HPV) infection. Two triage approaches were evaluated for women testing HPV-positive: (1) AHPV followed by LBC triage, where AHPV-positive women were referred to colposcopy if LBC showed ASC-US or worse; (2) AHPV with genotyping (AHPV-GT) and reflex LBC triage, where AHPV-positive women received further HPV genotyping and were referred to colposcopy if positive for HPV16/18/45, or if positive for other hr-HPV types combined with LBC showing ASC-US or worse.
Data analyses
Age-specific rates of positive screening, colposcopy referrals, and HSIL+ detection were computed, along with their 95% confidence intervals (CI). Absolute values and 95% CI were also determined for age-specific sensitivity, specificity, positive predictive value (PPV), and negative predictive value (NPV). Differences in sensitivity and specificity were assessed using McNemar tests. Receiver operating characteristic curve areas (AUC) were calculated per standard methods and compared via DeLong tests. PPVs and NPVs were compared with Pearson's chi-squared tests. Group differences in categorical variables were evaluated using chi-squared tests. Analyses were performed with SPSS version 22.0 and R software version 3.5.4 (R Foundation for Statistical Computing, Vienna, Austria), with statistical significance set at P < 0.05.
Results and Discussion
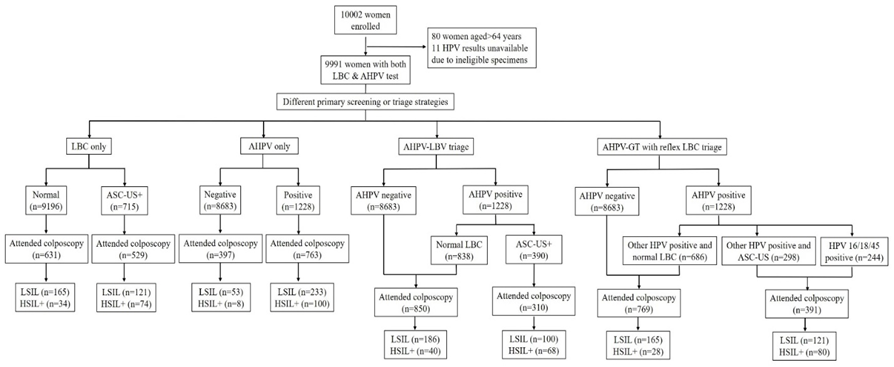
A total of 10,002 women were initially enrolled, but exclusions were made for those lacking HPV results (due to inadequate samples) and those younger than 35 or 65 years or older. This left 9911 women for analysis (Figure 1). Among them, 7891 (79.6%) resided in Liaoning province and 2020 (20.4%) in Qingdao City; 5915 (59.7%) were urban residents and 3996 (40.3%) rural. The median age was 49 years (interquartile range: 44–55). Demographic analysis showed that 5404 (54.5%) women were perimenopausal and 4507 (45.5%) postmenopausal. Furthermore, 9304 (93.9%) had never smoked, 527 (5.3%) were current smokers, and 80 (0.8%) were former smokers. Additionally, 5539 (55.9%) had experienced two or more pregnancies, and 1021 (10.3%) had two or more births. None of the participants had received HPV vaccination. Overall, 7708 (77.8%) had no prior cervical cancer screening history. Across all age groups and various screening approaches, the proportion of screening-positive results requiring colposcopy referral ranged from 390 (3.9%) to 1228 (12.4%). Colposcopy was carried out in 62.1%–79.5% of screening-positive women depending on the method used, and 96.8%–97.4% had satisfactory negative colposcopy results or adequate biopsy samples.
|
|
|
Figure 1. Presents a flow diagram illustrating the study population and screening outcomes. |
Among the 9911 participants, 715 (7.2%) showed abnormal cytology results (ASC-US or higher), and 1228 (12.4%) tested positive for HPV (Figure 1). Overall, 108 women (1.1%) were diagnosed with histologically confirmed HSIL+, including 5 (0.05%) who had verified cervical cancer. Table 1 displays the age-specific distribution of clinical characteristics among the screened women.
Age-specific rates of abnormal cytology ranged from 6.1% to 8.0%, peaking in the 45–54-year age group and reaching the lowest level in the 35–44-year group (P = 0.002). Low-grade cytological abnormalities were also significantly more frequent in women aged 45–54 years (P < 0.05). HPV prevalence showed considerable variation by age group: the rate was highest in 55–64-year-olds (14.1%), exceeding that in 35–44-year-olds (12.2%, P = 0.048) and 45–54-year-olds (11.6%, P = 0.002). Detection rates for histological HSIL+ did not vary significantly across age groups. However, LSIL detection was significantly higher in the 55–64-year age group compared to the 35–44-year group (3.5% vs. 2.5%, P = 0.028).
Table 1. Age-Specific Distribution of Clinical Characteristics of Screened Women.
|
Outcome |
55–64 years (N = 2602) n (%) |
45–54 years (N = 4706) n (%) |
35–44 years (N = 2603) n (%) |
Total (N = 9911) n (%) |
χ² |
p-value |
|
Low-grade cytology |
152 (5.8) |
332 (7.1) |
128 (4.9) |
612 (6.2) |
12.983 |
<0.001* |
|
|
|
3.988 |
0.046*** |
|||
|
|
|
2.184 |
0.139** |
|||
|
LBC abnormal |
179 (6.9) |
378 (8.0) |
158 (6.1) |
715 (7.2) |
9.497 |
0.002* |
|
|
|
3.164 |
0.075*** |
|||
|
|
|
1.408 |
0.235** |
|||
|
High-risk HPV positive |
366 (14.1) |
544 (11.6) |
318 (12.2) |
1228 (12.4) |
0.695 |
0.404* |
|
|
|
9.655 |
0.002*** |
|||
|
|
|
3.899 |
0.048** |
|||
|
High-grade cytology |
27 (1.0) |
46 (1.0) |
30 (1.2) |
103 (1.0) |
0.499 |
0.480* |
|
|
|
0.061 |
0.804*** |
|||
|
|
|
0.158 |
0.691** |
|||
|
HSIL+ |
36 (1.4) |
43 (0.9) |
29 (1.1) |
108 (1.1) |
0.690 |
0.406* |
|
|
|
3.459 |
0.063*** |
|||
|
|
|
0.766 |
0.381** |
|||
|
Histological diagnosis |
|
|
||||
|
LSIL |
92 (3.5) |
129 (2.7) |
65 (2.5) |
286 (2.9) |
0.386 |
0.534* |
|
|
|
3.607 |
0.058*** |
|||
|
|
|
4.798 |
0.028** |
LSIL: low-grade squamous intraepithelial lesion; HSIL: high-grade squamous intraepithelial lesion; LBC: liquid-based cytology; AHPV: Aptima human papillomavirus assay.
*Comparison between the 35–44-year and 45–54-year age groups. **Comparison between the 35–44-year and 55–64-year age groups. ***Comparison between the 45–54-year and 55–64-year age groups.
Age-related differences in the diagnostic accuracy of primary screening and triage approaches for HSIL+
The ability of primary cervical cancer screening assays to identify HSIL+ lesions showed clear variation across age categories. For women aged 55–64 years, AHPV testing achieved very high sensitivity (97.2%; 95% CI: 91.7–100), exceeding the sensitivity observed among those aged 45–54 years (86.0%; 95% CI: 74.4–95.3). Conversely, AHPV yielded a higher positive predictive value in younger women aged 35–44 years (17.7%; 95% CI: 12.3–24.8) compared with women aged 45–54 years (10.2%; 95% CI: 7.3–13.9).
Detailed analysis in the 35–44-year age group (Table 2) revealed marked differences between screening methods. AHPV testing detected nearly all HSIL+ cases, with a sensitivity of 96.6% (95% CI: 89.7–100), whereas LBC identified substantially fewer cases, achieving a sensitivity of 65.5% (95% CI: 48.3–82.8). This difference was statistically significant (P < 0.001). Despite this disparity in sensitivity, the predictive accuracy of positive results did not differ between the two methods, as PPVs were comparable for AHPV and LBC (17.7% vs. 18.3%, respectively; P = 0.910). Evaluation of overall diagnostic performance using ROC curve analysis further highlighted the superiority of AHPV. The AUC for AHPV was 0.956 (95% CI: 0.921–0.990), which was significantly greater than the AUC for LBC (0.810; 95% CI: 0.722–0.898; P < 0.001). When genotyping-based AHPV screening followed by reflex LBC triage was applied in women aged 35–44 years, screening efficiency improved further. This strategy increased the HSIL+ detection rate by 31.5% relative to LBC alone (9.6‰ vs. 7.3‰) while simultaneously lowering the proportion of women referred for colposcopy by 16.4% (5.1% vs. 6.1%). Consistent with these findings, the combined approach demonstrated a significantly higher AUC (0.918; 95% CI: 0.855–0.982) than LBC alone (P = 0.0046). Taken together, these findings indicate that, in women aged 35–44 years, both standalone AHPV testing and AHPV genotyping with reflex cytology provide superior diagnostic performance for HSIL+ detection compared with cytology-based screening.
Table 2. Comparative accuracy of triage strategies AND primary screening tests in identifying HSIL+ lesions.
|
Age group |
Screening strategy |
HSIL+ cases detected (n) |
HSIL+ detection rate (‰) |
Colposcopy referral rate (%) |
Sensitivity % (95% CI) |
Specificity % (95% CI) |
PPV % (95% CI) |
NPV % (95% CI) |
AUC (95% CI) |
P value |
|
35–44 yrs |
LBC |
19 |
7.3 |
6.1 |
65.5 (48.3–82.8) |
96.4 (95.7–97.2) |
18.3 (11.6–27.3) |
99.6 (99.2–99.8) |
0.810 (0.722–0.898) |
— |
|
AHPV |
28 |
10.8 |
12.2 |
96.6 (89.7–100.0) |
94.6 (93.7–95.4) |
17.7 (12.3–24.8) |
100.0 (99.7–100.0) |
0.956 (0.921–0.990) |
<0.001* |
|
|
AHPV with LBC triage |
19 |
7.3 |
3.6 |
65.5 (48.3–82.8) |
98.1 (97.5–98.6) |
29.2 (18.9–42.0) |
99.6 (99.2–99.8) |
0.818 (0.730–0.906) |
NA** |
|
|
AHPV genotyping + reflex LBC |
25 |
9.6 |
5.1 |
86.2 (67.4–95.5) |
97.5 (96.9–98.1) |
29.4 (20.3–40.4) |
99.8 (99.5–99.9) |
0.918 (0.855–0.982) |
0.0046# |
|
|
45–54 yrs |
LBC |
31 |
6.6 |
8.0 |
72.1 (58.1–83.7) |
94.2 (93.5–94.9) |
10.8 (7.6–15.1) |
99.7 (99.5–99.8) |
0.832 (0.764–0.900) |
— |
|
AHPV |
37 |
7.9 |
11.6 |
86.0 (74.4–95.3) |
92.6 (91.9–93.4) |
10.2 (7.3–13.9) |
99.9 (99.7–100.0) |
0.893 (0.841–0.946) |
0.178* |
|
|
AHPV with LBC triage |
26 |
5.5 |
4.2 |
60.5 (46.5–74.4) |
97.0 (96.5–97.5) |
16.3 (11.1–23.1) |
99.6 (99.4–99.8) |
0.787 (0.713–0.861) |
0.073** |
|
|
AHPV genotyping + reflex LBC |
29 |
6.2 |
5.4 |
67.4 (53.5–81.4) |
96.3 (95.7–96.9) |
15.0 (10.5–21.0) |
99.7 (99.4–99.8) |
0.819 (0.748–0.890) |
0.698# |
|
|
55–64 yrs |
LBC |
24 |
9.2 |
6.9 |
66.7 (50.0–80.6) |
95.8 (95.0–96.7) |
19.4 (13.0–27.6) |
99.5 (99.1–99.7) |
0.812 (0.734–0.891) |
— |
|
AHPV |
35 |
13.5 |
14.1 |
97.2 (91.7–100.0) |
92.3 (91.3–93.4) |
16.0 (11.5–21.7) |
100.0 (99.7–100.0) |
0.948 (0.920–0.975) |
0.002* |
|
|
AHPV with LBC triage |
23 |
8.8 |
3.9 |
63.9 (50.0–80.6) |
97.8 (97.2–98.4) |
30.7 (20.8–42.5) |
99.4 (99.0–99.7) |
0.809 (0.729–0.888) |
0.783** |
|
|
AHPV genotyping + reflex LBC |
26 |
10.0 |
6.0 |
72.2 (58.3–86.1) |
96.9 (96.2–97.6) |
25.7 (17.8–35.6) |
99.6 (99.2–99.8) |
0.845 (0.771–0.920) |
0.236# |
In the AHPV-LBC approach, women testing positive for AHPV were sent for further assessment only if their liquid-based cytology (LBC) showed atypical squamous cells of undetermined significance (ASCUS) or more severe changes. For the AHPV-genotyping strategy with reflex LBC, AHPV-positive samples received additional genotyping; patients were directed to colposcopy if HPV16 or HPV18/45 was identified, or if other high-risk HPV types were found in combination with LBC results of ASCUS or higher.
*Comparison of area under the curve (AUC) for LBC versus AHPV alone. **Comparison of AUC for LBC versus the combined AHPV-LBC method. #Comparison of AUC for LBC versus AHPV-genotyping plus reflex LBC.
HSIL+: high-grade squamous intraepithelial lesion or worse; PPV: positive predictive value; NPV: negative predictive value; AUC: area under the receiver operating characteristic curve; NA: not applicable.
For women aged 45–54 years (Table 2), AHPV achieved a sensitivity of 86.0% (95% CI: 74.4–95.3) for identifying HSIL+, which surpassed LBC's 72.1% (95% CI: 58.1–83.7), although the gap was not statistically meaningful (P = 0.210). The AUC for AHPV stood at 0.893 (95% CI: 0.841–0.946), somewhat above LBC's 0.832 (95% CI: 0.764–0.900), yet without reaching significance (P = 0.178). Using AHPV-genotyping with reflex LBC as triage yielded a slightly lower HSIL+ detection rate than LBC by itself (6.2 per 1,000 versus 6.6 per 1,000).
In the 55–64 age group (Table 2), AHPV's sensitivity for HSIL+ reached 97.2% (95% CI: 91.7–100.0), markedly outperforming LBC's 66.7% (95% CI: 50.0–80.6; P = 0.003). On the downside, AHPV exhibited reduced specificity compared with LBC (92.3%, 95% CI: 91.3–93.4 versus 95.8%, 95% CI: 95.0–96.7; P < 0.001), while positive predictive values were comparable (16.0%, 95% CI: 11.5–21.7 versus 19.4%, 95% CI: 13.0–27.6; P = 0.426). AHPV's AUC proved substantially better than LBC's (0.948, 95% CI: 0.920–0.975 versus 0.812, 95% CI: 0.734–0.891; P = 0.002). In this older cohort, the AHPV-genotyping strategy with reflex LBC triage boosted HSIL+ detection by 8.7% relative to LBC (10.0 per 1,000 versus 9.2 per 1,000) and cut colposcopy referrals by 13.0% (6.0% versus 6.9%). That said, AUC comparisons between this triaged approach and standalone LBC showed no meaningful difference (0.845, 95% CI: 0.771–0.920 versus 0.812, 95% CI: 0.734–0.891; P = 0.236). Ultimately, for women aged 55–64, the genotyped AHPV method with reflex LBC did not demonstrate a clear advantage over LBC alone in detecting HSIL+.
In this large-scale, real-world study involving community-based populations, we evaluated how well AHPV testing performed compared to cytology for identifying high-grade squamous intraepithelial lesions or worse (HSIL+) in women aged 35–64 years. Although HPV-based screening is recommended for women aged 30 and older, selecting the best way to manage HPV-positive results remains a key challenge [11, 18]. Our findings showed superior performance of AHPV over liquid-based cytology (LBC) in the 35–44 and 55–64 age groups. Additionally, AHPV genotyping combined with reflex LBC triage appeared appropriate for women aged 35–44, but proved less effective in those aged 55–64 and even underperformed LBC for HSIL+ detection in the 45–54 group.
High-risk HPV (hr-HPV) prevalence was highest among women aged 55–64 (14.1%), followed by 35–44 (12.2%), and lowest in 45–54 (11.6%). These patterns align with recent Chinese reports describing a secondary peak of HPV infections in women around 50–60 years [19] or specifically 55–64 years [14].
Across all age groups, AHPV identified more HSIL+ cases than LBC. The sensitivity advantage of AHPV was statistically significant in 35–44-year-olds (P < 0.001) and 55–64-year-olds (P = 0.003), but not in 45–54-year-olds (P = 0.210). Earlier studies using HPV DNA assays for primary cervical cancer screening have also explored age-related differences [20-22]. For example, a study in Costa Rica found greater HPV sensitivity in women aged 41 and older (93.2%) than in those aged 31–40 (80.8%) [23], while an Indian study noted peak sensitivity in women 50 and above [24]. In our cohort, AHPV sensitivity reached its highest level (97.2%) in 55–64-year-olds and its lowest (86.0%) in 45–54-year-olds—mirroring the age distribution of hr-HPV prevalence. Differences in age-specific HPV sensitivity across studies likely stem from cohort variations, regional sexual behaviors, and geographic factors influencing HPV prevalence [25]. Notably, both HPV DNA and AHPV methods in these reports, including ours, demonstrated strong sensitivity in older women. Some other studies, however, found consistently high HPV sensitivity regardless of age [26-28].
In our data, AHPV specificity declined as age increased. This echoes prior findings of age-dependent HPV specificity (highest below age 35; P < 0.0001) [28], though contrasting reports have shown specificity rising with age [29]. Possible explanations for these age-related patterns include: women in the 45–54 group, who had the lowest hr-HPV rates, are often perimenopausal with fluctuating hormones and less sexual activity; older women (55–64) may experience reduced specificity due to higher infection rates, weakened immunity, thinner cervical/vaginal epithelium prone to micro-injury [30], and elevated low-grade squamous intraepithelial lesion (LSIL) detection.
Cytology (LBC) sensitivity was highest in 45–54-year-olds, then 55–64-year-olds. This supports earlier evidence of better cytologic detection of HSIL+ in women over 50 compared to younger ones [29], potentially linked to age-specific patterns of cytologic abnormalities [31]. Although abnormal cytology rates generally decline with age, abnormalities in older women tend to be high-grade [32]. We found the highest abnormal cytology prevalence (8.0%) in 45–54-year-olds. In perimenopausal and postmenopausal women, high-grade lesion cells are less likely to be missed, and atrophy from low estrogen is readily recognized by cytologists.
With HPV testing now endorsed as primary screening [11], age-appropriate triage strategies need reevaluation. In our study, the two triage options performed differently by age. Compared to standalone LBC, AHPV-LBC triage yielded similar HSIL+ detection in 35–44-year-olds but fewer cases in the older groups. In contrast, AHPV genotyping with reflex LBC detected more HSIL+ than LBC in 35–44 and 55–64-year-olds, but not in 45–54-year-olds. Colposcopy referral rates with this genotyping triage rose with age (5.1%, 5.4%, and 6.0% across the groups). AUC values showed no significant difference between genotyping triage and LBC in 55–64-year-olds. One prior study similarly found genotyping plus reflex cytology identified more HSIL+ in 35–54-year-olds but not in 55–64-year-olds compared to cytology alone [12], possibly because many high-grade lesions in postmenopausal women involve non-16/18 HPV types [33]. Thus, current triage methods have limitations for perimenopausal and postmenopausal HPV-positive women, highlighting the need for alternative approaches.
Study strengths include its community-based design, reflecting real-world urban and rural Chinese populations rather than hospital patients. Limitations involve suboptimal colposcopy follow-up among HPV-positive/cytology-negative women, restriction to three age brackets (excluding 25–34-year-olds), and the cross-sectional nature lacking longitudinal data to refine age-specific triage.
Conclusion
In summary, primary AHPV screening with tailored triage strategies varies in effectiveness across age groups. AHPV stands out as a suitable primary tool for women aged 35–44 and 55–64. Genotyping combined with reflex LBC triage works well for 35–44-year-olds. In the context of primary HPV screening, new triage options should be explored specifically for older HPV-positive women.
Acknowledgments: None
Conflict of Interest: None
Financial Support: None
Ethics Statement: None