Identifying BRAF mutations is crucial for managing advanced melanoma in treatment-naïve patients. When tumor tissue is unavailable or inadequate, liquid biopsy represents a promising alternative. This retrospective, single-center study evaluated the effectiveness of plasma circulating tumor DNA (ctDNA) in detecting BRAF mutations and assessed patient outcomes following BRAF/MEK inhibitor therapy initiated based on ctDNA results. A total of 46 patients (21 women, 25 men) with advanced melanoma underwent ctDNA analysis. Mutations in BRAF were observed in 45.7% (21/46) of liquid biopsy samples and 44.8% (13/29) of available tissue samples. Among patients with both tissue and ctDNA data (n = 29), the two approaches agreed in 82.8% of cases. In 7 out of 17 patients assessed exclusively via ctDNA, BRAF mutations were detected. Eighteen patients received BRAF/MEK inhibitor therapy guided by liquid biopsy findings, achieving an objective response rate of 77.8% and a median progression-free survival of 6.0 months. These results demonstrate that plasma ctDNA is a reliable tool for BRAF mutation detection and that targeted therapy can be initiated based on liquid biopsy in real-world clinical practice.
Introduction
The era of precision oncology has fundamentally changed how cancers, including melanoma, are diagnosed and treated. Historically, patients with advanced melanoma faced poor outcomes under conventional chemotherapy. The discovery of BRAF mutations in melanoma cells catalyzed the development of targeted therapies, leading to a series of BRAF inhibitors designed to selectively block these oncogenic pathways [1]. Vemurafenib was the first agent to gain FDA and EMA approval in 2011 and 2012, respectively, following pivotal clinical trial results [2]. Later, newer BRAF inhibitors such as dabrafenib and encorafenib were incorporated into therapeutic protocols [3, 4]. To improve treatment durability and mitigate resistance, MEK inhibitors—including cobimetinib, trametinib, and binimetinib—were introduced [4-6]. The current standard of care for patients with advanced melanoma, as well as for adjuvant therapy, involves combined BRAF and MEK inhibition [7, 8].
Activating mutations in BRAF, particularly at codon 600, are critical determinants of responsiveness to these targeted therapies, with approximately 40–50% of cutaneous melanoma cases harboring such alterations [1]. While V600E is the predominant variant, other mutations—V600K, V600D, V600R, V600M, and V600E2—have also been reported [9]. Accurate identification of these mutations is essential for guiding treatment decisions. Typically, mutation testing is performed on formalin-fixed, paraffin-embedded tumor tissue from primary or metastatic lesions. However, obtaining sufficient tissue can be challenging in certain patients, creating a need for less invasive diagnostic strategies.
Liquid biopsy has emerged as a minimally invasive approach to assess circulating tumor cells (CTCs) or circulating tumor DNA (ctDNA) from blood or urine samples [10]. ctDNA analysis enables comprehensive profiling of tumor genetics and has been validated for detecting clinically relevant mutations, including BRAF in melanoma and EGFR in lung cancer [11, 12]. Despite its potential, liquid biopsy remains largely restricted to clinical trials, though its integration into routine clinical practice is gradually increasing.
In this study, we investigated the real-world utility of ctDNA for BRAF mutation detection in melanoma patients. We examined patient characteristics, reasons for ctDNA testing, and clinical outcomes in those treated with BRAF/MEK inhibitors based on ctDNA results.
Materials and Methods
We conducted a retrospective review of medical records at the Maria Skłodowska-Curie National Research Institute of Oncology in Warsaw to identify patients with cutaneous melanoma who underwent BRAF testing via liquid biopsy between January 1, 2018, and August 15, 2020, ensuring a minimum follow-up of 12 months. Tissue-based BRAF testing was performed when available. Collected information included patient demographics, disease stage, timing of test ordering and result availability, indications for liquid biopsy, and subsequent BRAF-targeted therapy.
The study received ethical approval from the local bioethics committee (Opinion 13/2008).
Plasma samples (4–5 mL) were collected, and ctDNA was isolated immediately using the QIAamp® Circulating Nucleic Acid Kit (QIAGEN). Quantitative PCR was performed using either the EntroGen® or AmoyDx® BRAF V600 Mutation Detection Kits, following the manufacturers’ protocols. Both assays are CE-IVD certified and detect V600 variants of BRAF through mutation-specific amplification. The EntroGen® assay identifies V600E, V600E2, V600K, V600D, V600R, and V600M mutations, with sensitivity ranging from 0.05% (V600E) to 1% (V600K). The AmoyDx® assay detects V600E, V600E2, V600K, V600R, V600D1, and V600D2 mutations with a minimum mutant allele frequency of 1%. Neither assay distinguishes between V600 codon variants. Results were considered positive if CT values were within manufacturer-specified ranges.
Tissue DNA was extracted using QIAamp® DNA Mini Kit (QIAGEN) or Cobas® DNA Sample Preparation Kit (Roche) and analyzed via therascreen® BRAF RGQ PCR Kit, AmoyDx® BRAF V600 Kit, or Cobas® 4800 BRAF V600 Test. All methods detect activating codon 600 BRAF mutations. Testing was performed in EMQN- and GENQA-certified laboratories.
Data were summarized using descriptive statistics. The Mann–Whitney U test compared groups, and Kaplan–Meier analysis estimated survival. The database was locked on August 15, 2021, living patients were censored. Progression-free survival (PFS) was measured from therapy initiation to progression, death, or loss to follow-up. Overall survival (OS) spanned from treatment start to death or censoring. Duration of response (DOR) was calculated from the date of first documented objective response to progression, death, or censoring. Patients receiving BRAF/MEK inhibitors were monitored via imaging every 8–12 weeks, with responses assessed using RECIST 1.1 criteria. Turnaround time (TAT) for mutation testing was defined as the interval between test request and availability of results. Statistical analyses were performed using PS Imago PRO 7.0, with significance set at p < 0.05.
Results and Discussion
Patient characteristics
A total of 46 patients (21 women and 25 men) with cutaneous melanoma underwent BRAF mutation testing using liquid biopsy (Table 1). Most patients (n = 44, 93.6%) were classified as stage IV at the time of testing, while only 2 patients (6.4%) were stage III. The majority, 78.3% (n = 36), had not received prior systemic treatment. Additionally, 34.8% of patients presented with serum lactate dehydrogenase (LDH) levels equal to or exceeding twice the upper limit of normal (ULN) at diagnosis.
Table 1. Study population characteristics.
|
Characteristics |
n (%) |
|
|
Gender |
Male |
21 |
|
Female |
25 |
|
|
Stage |
III |
2 (6.4) |
|
IV |
44 (93.6) |
|
|
Previous treatment |
Yes |
10 (21.7) |
|
Anti-PD-1 |
9 (90.0) |
|
|
chemotherapy |
1 (10.0) |
|
|
LDH |
Normal |
13 (28.3) |
|
ULN < 2xULN |
11 (23.9) |
|
|
≥2xULN |
16 (34.8) |
|
|
Not available |
6 (13.0) |
|
|
Organs with metastatic lesions |
>3 |
11 (23.9) |
|
Brain metastases |
15 (32.8) |
|
LDH—lactate dehydrogenase, ULN—upper level of normal.
BRAF mutation testing
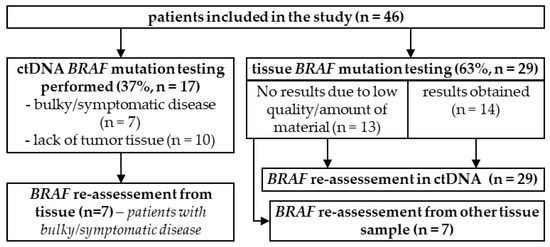
In 29 patients (63%), BRAF mutation testing was initially performed on tumor tissue. Among these, 13 patients (44.8%) could not have their mutation status determined due to insufficient or poor-quality tissue. Of these 13, six later underwent a complete reassessment using a different tissue specimen. In seven patients, rapid determination of BRAF status was necessary, prompting ctDNA testing while tissue results were pending. Additionally, ctDNA analysis was requested for nine patients who were initially BRAF-negative on tissue testing to confirm their results (Figure 1).
|
|
|
Figure 1. Flowchart of different BRAF mutation testing methods in the study population. |
|
In 37% of patients (n = 17), ctDNA testing was performed as the initial diagnostic approach. Among these, 10 patients underwent liquid biopsy due to the absence of available tumor tissue, while 7 patients had ctDNA analysis to expedite treatment initiation. Tissue-based BRAF results were subsequently obtained in all seven of these patients (Figure 1). All 46 patients ultimately had BRAF mutation results from ctDNA analysis, with 29 patients (63%) also having corresponding tissue sample results. Metastatic lymph nodes were the most frequently tested material (55.2%, 16/29), followed by distant metastatic lesions (34.5%, 10/29), and primary tumors (10.3%, 3/29). The median turnaround time (TAT) for ctDNA results was notably shorter at 1.07 days (range 0.2–6.0), compared to 9.2 days (range 2.9–38.0) for tissue testing (p < 0.001). BRAF mutations were identified in 45.7% of liquid biopsy samples (21/46) and 44.8% of tissue samples (13/29). Among the 29 patients with both ctDNA and tissue results, concordance between the two testing methods was 82.8%. ctDNA detected BRAF mutations in 84.6% of patients who were tissue-positive, while 81.3% of tissue-negative cases were correctly identified as mutation-negative in ctDNA. This corresponded to a sensitivity of 84.6% and specificity of 81.3% for ctDNA testing (Table 2). In patients who underwent only ctDNA analysis, BRAF mutations were found in 41.2% (7/17) of cases.
Table 2. Number of patients with BRAF-mutated wild-type melanoma according to the diagnostic modality and concordance of results between ctDNA and tissue sample testing.
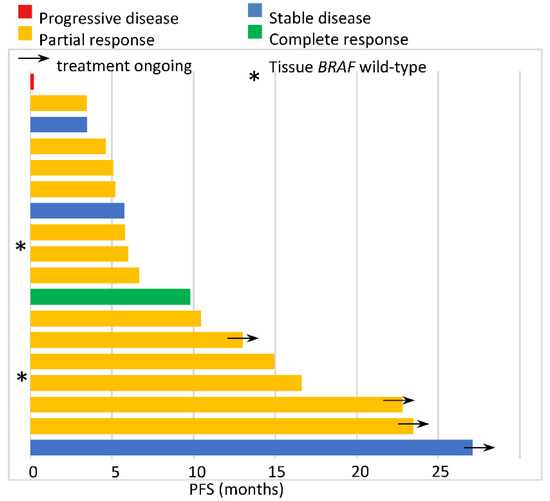
BRAF/MEK inhibitor treatment A total of 18 patients received first-line therapy with BRAF/MEK inhibitors guided by ctDNA BRAF mutation results. The median progression-free survival (PFS) was 6.0 months (95% CI, 4.1–7.8), with two patients still continuing treatment at the time of analysis (Figure 2). The objective response rate (ORR) was 77.8%, including one complete response (CR, 5.6%) and 13 partial responses (PR, 72.2%). The disease control rate (DCR) reached 94.4%, as only a single patient showed disease progression as their best response. Median duration of response (DOR) was 4.0 months (95% CI, 0–10.3). During follow-up, six patients died, and the median overall survival (OS) was 12.8 months (95% CI, 0–25.8).
|
|||||||||||||||||
|
Figure 2. Progression-free survival with BRAF/MEK inhibitors administered based on the ctDNA analysis. |
|||||||||||||||||
Among the patients analyzed, two of the three individuals with ctDNA-positive but tissue-negative BRAF results (as determined using the Cobas 4800 BRAF V600 Mutation Test) received BRAF/MEK inhibitor therapy, both achieving partial responses. Their progression-free survival (PFS) was 15.0 and 5.8 months, with corresponding durations of response (DOR) of 10.4 and 3.9 months. Conversely, one patient with ctDNA-negative but tissue-positive BRAF status commenced BRAF-targeted therapy, achieving stable disease for 27.1 months and continuing treatment at the time of analysis.
Five patients received BRAF/MEK inhibitors solely on the basis of ctDNA results, without available tissue data. Among these, one patient achieved a complete response, three attained partial responses, and one exhibited disease stabilization. Their PFS ranged from 3.5 to 26.1 months, specifically 26.1, 19.2, 9.8, 6.0, and 3.5 months, respectively.
Discussion
Detection of BRAF V600 mutations is an established step prior to initiating melanoma therapy, typically conducted on tumor tissue. However, in cases where tissue samples are limited or inadequate, alternative approaches such as liquid biopsy become necessary. This study provides a retrospective evaluation of all consecutive ctDNA-based BRAF tests performed in a tertiary care setting outside clinical trials.
Previous reports have demonstrated high concordance between ctDNA and tumor tissue in detecting somatic mutations, with 70–90% of single-nucleotide variants detected in both sample types [13]. Consequently, ctDNA testing is increasingly utilized in melanoma management. Prior studies report sensitivities of 50–100% and specificities of 75–100% for plasma ctDNA in identifying BRAF mutations [12, 14–18]. In our cohort, over 80% concordance between ctDNA and tissue results was observed, aligning with these ranges, although only 2/3 of patients had both sample types analyzed, potentially affecting accuracy. Additionally, most earlier studies derived data from clinical trials rather than routine practice.
Various methods exist to detect and quantify ctDNA. Standard qPCR, as employed here, identifies mutations present in ≥1% of ctDNA, whereas advanced techniques like digital PCR, droplet digital PCR, or BEAMing can detect mutant alleles at frequencies as low as 0.01% [11, 18]. Sensitivity is generally higher in stage IV versus stage III melanoma [19], and metastatic site influences detectability, visceral, bone, or lymph node metastases tend to produce higher ctDNA levels than brain or subcutaneous metastases [20]. Elevated ctDNA levels have been associated with poorer melanoma-specific survival, higher risk of distant metastasis, and reduced PFS and OS, particularly in stage IV patients [14, 17, 18, 21–24]. Importantly, decreasing ctDNA levels often correlate with response to BRAF/MEK inhibitors, while rising levels may precede radiologic or clinical disease progression [12, 14, 24]. In this study, ctDNA analysis was used solely for BRAF mutation detection, without quantitative monitoring—a limitation of the study.
Nonetheless, ctDNA testing facilitated initiation of first-line BRAF/MEK inhibitor therapy in 18 patients, reflecting real-world disease burden. Although immunotherapy is now generally preferred as upfront treatment for metastatic melanoma due to durable outcomes—with 5-year OS rates of 39–44% for anti-PD1 monotherapy and 52% for nivolumab plus ipilimumab combinations [25, 26]—BRAF-targeted therapy remains indicated for patients with rapidly progressing or symptomatic disease. In our cohort, the median PFS of 6.0 months and an ORR of 77.8% are consistent with real-world experiences, though slightly lower than phase III trials [27]. Patients in routine practice may have more adverse prognostic factors, such as elevated LDH or extensive disease, which is reflected in these outcomes [28].
The rapid turnaround time of ctDNA testing is a key advantage, enabling prompt treatment initiation, particularly in patients with symptomatic disease. ctDNA also provides a practical alternative when tissue is inaccessible or inadequate for molecular analysis. Notably, all patients receiving therapy solely based on ctDNA results experienced clinical benefit, including one complete response.
This study also highlights instances of plasma-positive/tissue-negative BRAF results. Previous research suggests that the Cobas 4800 assay may be less sensitive to mutations other than V600E [29, 30]. Because the assays used do not differentiate specific V600 codon mutations, exact variant identification was not possible. Despite this, two of the three patients in this category responded to BRAF/MEK inhibitors with partial responses, supporting the clinical relevance of ctDNA testing.
Several limitations should be acknowledged. This was a retrospective study of a small, selected patient cohort in routine clinical practice. ctDNA testing was primarily applied in patients for whom tissue was unavailable or when rapid treatment initiation was necessary. Furthermore, the assays used did not quantify mutant ctDNA levels or distinguish V600 mutation subtypes, limiting correlations with treatment outcomes.
Conclusion
Our findings demonstrate that ctDNA represents a practical and reliable source for BRAF mutation testing in patients with advanced melanoma, particularly when tumor tissue is unavailable or when rapid disease progression necessitates urgent treatment. The observed concordance of over 80% between ctDNA and tissue-based results underscores the clinical value of liquid biopsy. Advantages of this approach include its minimally invasive nature, cost-effectiveness, reproducibility, and rapid turnaround time. Additionally, liquid biopsy can overcome challenges related to tissue availability, sample quality, and intratumoral heterogeneity.
These real-world data indicate that BRAF/MEK inhibitor therapy can be effectively initiated based on ctDNA results, supporting the integration of liquid biopsy into routine clinical practice for advanced melanoma management.
Acknowledgments: None
Conflict of Interest: P.S. has received travel grants from MSD, Roche, Novartis, and Pierre Fabre and honoraria for lectures from Swixx BioPharma and BMS. Non-financial interests: European Society of Medical Oncology—Officer, Polish Society of Clinical Oncology—Member of Board of Directors. K.K. has received honoraria for lectures from BMS, MSD, Novartis, Pfizer, and Pierre Fabre. S.K. has received travel grants from Pierre Fabre. P.R. (Paweł Rogala) has received honoraria from BMS, MSD, Novartis, and Pierre Fabre. T.Ś. has received honoraria from BMS, Roche, and Novartis and research funding from Amgen. H.K.-P. has received honoraria for lectures from Merck, Novartis, BMS, MSD, and Pierre Fabre and financial support for participation in conferences from Roche, Novartis, MSD, and BMS. P.R. (Piotr Rutkowski): Personal financial interests: Blueprint Medicines, Advisory Board, BMS, invited speaker, honoraria for lectures, Advisory Board, Merck, Advisory Board, Merck, invited speaker, honoraria for lectures, MSD, Advisory Board, Novartis, invited speaker, Pierre Fabre, invited speaker, honoraria for lectures, Pierre Fabre, Advisory Board, Sanofi, Advisory Board, invited speaker. Institutional interests: BMS, funding, financial interest, research grant for institution, Pfizer, research grant, financial interest, research grant for ISS. Non-financial interests: ASCO, Officer, Polish Society of Surgical Oncology, Member of Board of Directors. A.G. and A.T. declare no conflict of interest.
Financial Support: None
Ethics Statement: This study was approved by the local bioethics committee at the Maria Skłodowska-Curie National Research Institute of Oncology in Warsaw—opinion 13/2008.
All data were collected in routine clinical practice. Informed consent for genetic testing was obtained from all subjects under routine procedure.