The combination of immune checkpoint inhibitors (ICIs) and vascular endothelial growth factor (VEGF) inhibitors has become a standard first-line therapy for patients with unresectable hepatocellular carcinoma (HCC), highlighting the importance of ICIs in treatment strategies. However, around one-fifth of patients fail to respond, often due to activating mutations in the Wnt/β-catenin signaling pathway, which are associated with primary resistance. Detecting Wnt/β-catenin activation through non-invasive methods could therefore be crucial for guiding clinical management in advanced HCC. Mutations in this pathway manifest in two distinct tumor behaviors: the “Jekyll phenotype,” which shows limited vascular invasion, low metastatic potential, and favorable prognosis, and the “Hyde phenotype,” a more aggressive form characterized by poor differentiation, frequent metastasis, cancer stem cell characteristics, and elevated serum alpha-fetoprotein levels. Differentiation between these phenotypes may be achieved using a combination of hepatobiliary phase Gd-EOB-DTPA-enhanced magnetic resonance imaging (MRI), which highlights the Jekyll phenotype via increased nodule enhancement, and FDG-PET/CT, which identifies the Hyde phenotype through elevated glucose uptake.
Introduction
Cancer can be understood through the lens of evolutionary biology at the cellular level, where neoplasms develop within a complex tissue ecosystem and are shaped by selective pressures. Tumorigenesis is driven by clonal selection, with genetic alterations that promote cell proliferation—known as driver mutations—conferring a growth advantage and facilitating malignancy [1]. Evidence suggests that the accumulation of at least three driver mutations is generally necessary for the emergence of malignant tumors [2].
Hepatocellular carcinoma (HCC) exhibits substantial heterogeneity at both the molecular and pathological levels. Early genomic alterations during the preneoplastic phase remain incompletely characterized, though aberrant DNA methylation, genomic instability, and activation of telomerase reverse transcriptase (TERT) have been implicated [3]. In established HCC, dysregulation of oncogenes such as MET, CTNNB1, MYC, and CCND1, alongside tumor suppressors including TP53, PTEN, CDKN2A, and CDH1, has been documented through genetic and epigenetic analyses [3]. The mutational landscape of HCC is highly variable, even across nodules within a single liver, highlighting complex oncogenic pathways in hepatocarcinogenesis. For instance, TERT promoter mutations occur in 60–70% of cases, TP53 in 21–35%, CTNNB1 in 16–40%, AXIN1 in 5–15%, APC in 2–3%, PIK3CA in 1.5%, RAS in 1.3%, and PTEN in 1% [4, 5]. Notably, CTNNB1 and TP53 mutations tend to be mutually exclusive, defining distinct HCC subtypes, whereas AXIN1 and TP53 alterations can co-occur, corresponding to the G2 subclass defined by Boyault et al. [4].
The poor prognosis associated with HCC is largely attributable to early metastasis, which often precludes surgical intervention. Multi-organ dissemination and vascular invasion are frequently observed in tumors undergoing epithelial-to-mesenchymal transition (EMT), a process linked to Wnt pathway dysregulation. Non-invasive imaging approaches, such as hepatobiliary phase Gd-EOB-DTPA-enhanced MRI, have been employed to infer Wnt pathway activity, as higher nodule enhancement correlates with OATP1B3 expression, a potential indicator of Wnt activation [6–9]. Most HCCs with active Wnt/β-catenin signaling and OATP1B3 expression display favorable prognoses, with reduced vascular invasion and limited metastasis [6].
Two distinct HCC phenotypes associated with Wnt activation have been described: the aggressive “Hyde phenotype,” characterized by EMT and metastatic potential, and the indolent “Jekyll phenotype,” which exhibits limited proliferation. Molecular mechanisms underlying these divergent phenotypes remain incompletely understood, partly due to selection bias in mutation analyses, which are typically performed on resected specimens favoring less aggressive tumors. Downstream effectors of Wnt signaling are likely involved in driving stemness and EMT programs. This review focuses on the key downstream molecules of Wnt/β-catenin signaling implicated in these contrasting HCC phenotypes and discusses their clinical implications.
Jekyll and hyde phenotypes of HCC
Activation of Wnt/β-catenin signaling can give rise to phenotypically distinct HCC subsets. The Hyde phenotype exhibits features of cancer stem cells, elevated serum alpha-fetoprotein (AFP) levels, vascular invasion, and multi-organ metastases, often accompanied by EMT and angiogenesis. In contrast, the Jekyll phenotype is associated with a favorable prognosis, low recurrence, and absence of elevated tumor markers. Wnt/β-catenin signaling contributes directly to EMT induction across multiple cancer types.
Epithelial-to-mesenchymal transition in the tumor microenvironment
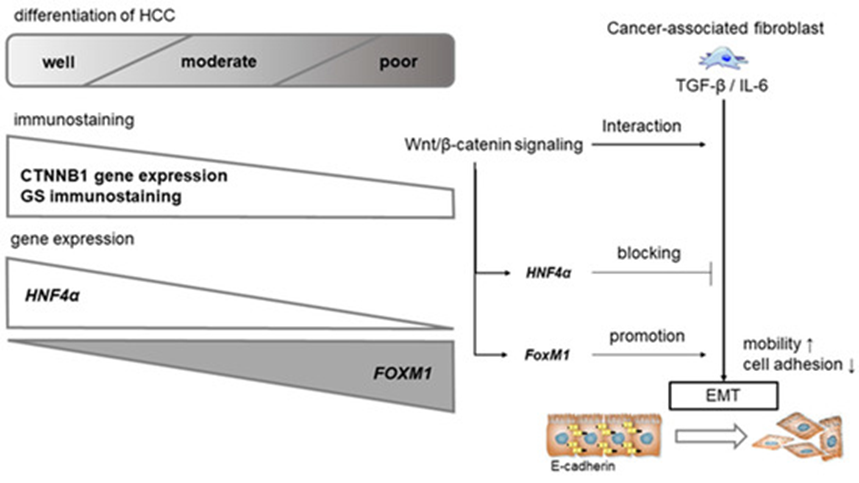
EMT is a developmental program essential for tissue patterning and organogenesis, which is aberrantly reactivated in cancer progression. Fibroblast phenotypic changes represent an initial step toward metastasis, with cancer-associated fibroblasts driving EMT through TGF-β and interleukin-6 signaling pathways [10] (Figure 1). Through cytoskeletal remodeling and acquisition of motility reminiscent of embryogenesis, cancer cells gain invasive and metastatic capabilities. EMT also supports colonization and growth at secondary sites. Hallmarks of EMT include downregulation of E-cadherin, compromising cell–cell adhesion, and upregulation of vimentin, marking the mesenchymal phenotype [11].
|
|
|
Figure 1. Interaction of Wnt/β-Catenin Signaling with EMT and TGF-β/IL-6 in HCC |
EMT, or epithelial-to-mesenchymal transition, is tightly regulated by the TGF-β/IL-6 signaling network, and evidence shows that Wnt/β-catenin signaling can also drive EMT directly. Activating mutations in Wnt/β-catenin are present in nearly 40% of hepatocellular carcinomas, particularly in tumors of well-to-moderate differentiation. Wnt downstream effectors produce distinct effects: HNF4α suppresses EMT, giving rise to a less invasive tumor profile with limited metastatic potential, while FOXM1 enhances EMT by reducing E-cadherin expression, producing an aggressive tumor phenotype characterized by high metastatic capability.
Although EMT contributes to normal tissue repair, its dysregulation fosters fibrosis and tumor progression through multiple pathways, including TGF-β, Wnt/β-catenin, Notch, HGF, EGF, FGF, and hypoxia-inducible factors. These signaling cascades converge on transcription factors such as Twist, Snail (Snai1, Snai2), Smuc, ZEB1/ZEB2, and E12/E47, which repress epithelial markers like E-cadherin and promote mesenchymal traits. Wnt/β-catenin-mediated EMT exhibits variability depending on tissue context and microenvironment, but Snail1 and Snail2 have been identified as direct transcriptional targets, enhancing tumor invasiveness through upregulation of matrix metalloproteinases. Twist, indirectly influenced by Wnt signaling and stabilized via β-TRCP, further promotes motility and metastatic behavior. In HCC, these EMT transcription factors are often induced by TGF-β, and studies in fibrous (scirrhous) HCC indicate that stromal fibroblasts may facilitate EMT gene expression and amplify TGF-β activity, linking the tumor microenvironment to cancer aggressiveness.
Wnt signaling and key molecular players
The Wnt family regulates embryonic development and maintains adult tissue homeostasis by controlling cell proliferation, differentiation, and stem cell renewal. Wnt proteins are small, conserved secreted molecules (~40 kDa), with 19 members identified in mammals. Alterations in Wnt signaling, either genetic or epigenetic, are commonly implicated in tumorigenesis. Wnt signals propagate through three main branches: the canonical Wnt/β-catenin pathway, the planar cell polarity pathway, and the non-canonical Ca²⁺ pathway, with the canonical pathway being most thoroughly studied.
Frizzled receptors, featuring seven transmembrane domains and an extracellular cysteine-rich region, interact with LRP5 and LRP6 co-receptors to mediate canonical Wnt signaling.
Canonical Wnt/β-catenin activation
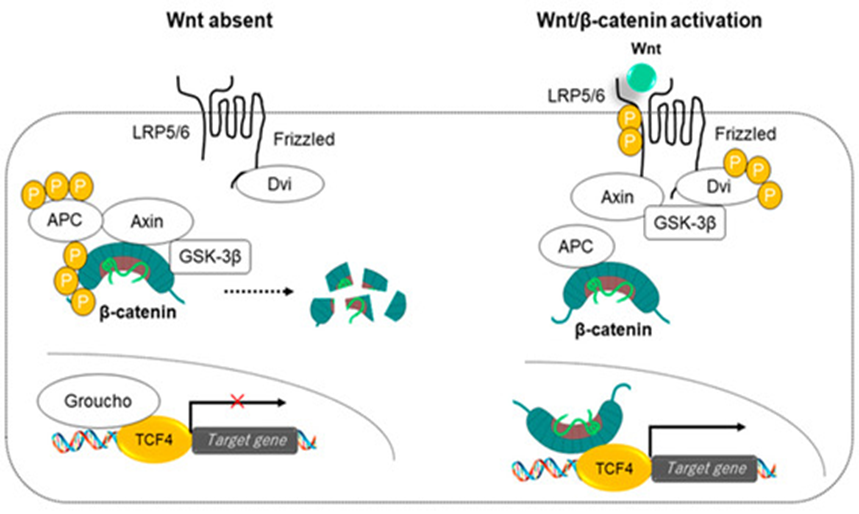
In the canonical pathway, Wnt ligands such as Wnt3a, Wnt1, or Wnt7 bind the Frizzled-LRP5/6 receptor complex on the cell surface, preventing β-catenin degradation. Accumulated β-catenin then translocates to the nucleus, activating transcription of genes involved in proliferation, EMT, and other tumor-promoting processes (Figure 2).
|
|
|
Figure 2. Mechanism of Canonical Wnt/β-Catenin Signaling |
In the absence of Wnt ligands, β-catenin is continuously targeted for degradation. Axin acts as a scaffold within the destruction complex, efficiently facilitating phosphorylation of β-catenin by glycogen synthase kinase 3β (GSK-3β). Cytoplasmic β-catenin interacts with Axin, while APC binds the regulator of G protein signaling (RGS) domain, forming the Axin/APC complex. Within this complex, multiple β-catenin molecules are sequentially phosphorylated by GSK-3β and subsequently recognized and degraded by the ubiquitin-proteasome system. Phosphorylation of Axin and APC further enhances β-catenin targeting for destruction. Concurrently, TCF transcription factors are bound by Groucho co-repressors, repressing Wnt target gene transcription.
When Wnt ligands engage the Frizzled/LRP5/6 receptor complex, phosphorylation of the cytoplasmic tail of LRP5/6 occurs, disrupting β-catenin phosphorylation by GSK-3β. This prevents β-catenin degradation, allowing accumulation in the cytoplasm. The destruction complex is sequestered away from Axin, and caveolin-mediated endocytosis of the Axin complex via LRP6 contributes to β-catenin stabilization. Stabilized β-catenin translocates to the nucleus, where it displaces Groucho and binds TCF/LEF transcription factors, activating Wnt-responsive genes. R-spondin can potentiate this pathway by increasing Frizzled receptor availability. Disruption of Wnt pathway components can lead to diverse tissue phenotypes and pathological consequences.
Through canonical signaling, β-catenin acts as a central mediator, controlling transcriptional programs that govern proliferation, differentiation, and other context-dependent cellular events. In the absence of Wnt, TCF/LEF factors function as transcriptional repressors, highlighting the switch-like nature of this pathway.
Downstream targets of Wnt/β-catenin
The Wnt/β-catenin pathway plays essential roles in embryogenesis, tissue homeostasis, and tumorigenesis. Over 100 downstream target genes have been identified, which can be broadly categorized into three groups: (1) regulators of cell cycle and proliferation, including c-myc and cyclin D1; (2) genes governing axis formation and organ development; and (3) components of the Wnt pathway itself, such as Wnt3a, Axin2, Frizzled, LEF1, TCF1, and LGR5.
Key transcription factors driving epithelial-to-mesenchymal transition (EMT), including Snail1, Snail2, and Twist, are well-established Wnt targets and contribute to metastatic potential. Wnt signaling also intersects with TGF-β pathways to coordinate EMT induction. In hepatocellular carcinoma, overexpression of Snail and Twist correlates with poor prognosis. Other Wnt-responsive genes include matrix metalloproteinases (MMPs) and VEGF, which facilitate neovascularization, and they interact with stemness and adhesion markers, such as SALL4, EpCAM, and E-cadherin, linking Wnt signaling to tumor progression and invasiveness.
Canonical Wnt/β-catenin mutations and tumorigenesis
The canonical β-catenin pathway plays a critical role in regulating cell proliferation and the cell cycle by controlling the expression of genes such as cyclin D1 and c-myc. Alterations in key regulatory components of this pathway can disrupt normal cell cycle control, thereby promoting carcinogenesis. Large-scale genomic analyses using deep sequencing have identified frequent mutations in APC, CTNNB1, and Axin across various cancer types, including colorectal and liver cancers, often resulting in β-catenin accumulation [12]. APC can also be silenced through epigenetic modifications, and dense methylation of APC has been observed in HCC [13]. Among human cancers, canonical Wnt/β-catenin mutations are most prevalent in colorectal cancer (>90%), followed by ovarian (~50%), hepatocellular carcinoma (~40%), and malignant melanoma (~30%) [14].
The dual nature of Wnt/β-catenin mutations
Aberrant Wnt/β-catenin signaling promotes cell proliferation, loss of epithelial characteristics, and cellular dedifferentiation. Key EMT-related transcription factors, such as Snail and Twist, are downstream targets of Wnt, facilitating metastasis and invasion, and are linked to poor clinical outcomes [15]. However, the relationship between Wnt activation and prognosis remains inconsistent across studies. In malignant melanoma, for instance, nuclear β-catenin accumulation has been associated with improved overall survival in clinical cohorts [16], whereas in mouse models harboring BRAF and PTEN mutations, β-catenin activation promotes tumor growth and metastasis [17]. Webster et al. reported that Wnt5a and ARF6 enhance β-catenin expression and tumor metastatic potential [18]. In colorectal cancer, molecular subtypes with high expression of Wnt target genes showed better post-recurrence survival than those with low expression [19]. In breast cancer, Wnt signaling is active in over half of patients, and elevated Wnt/β-catenin and cyclin D1 expression correlates with worse overall survival [20].
In HCC, canonical Wnt/β-catenin pathway activation has been reported in roughly 40% of cases [5], whereas a subset of tumors exhibits enhanced non-canonical Wnt/TGF-β signaling [21]. HCCs harboring canonical CTNNB1 mutations are generally well-differentiated, exhibit cholestatic and microtrabecular or pseudoglandular histology, and lack inflammatory infiltrates [4, 6, 7]. Importantly, these findings primarily come from surgically resected tumors, introducing bias, as aggressive HCCs undergoing EMT are often excluded. In this context, HNF4α expression has been associated with low-grade HCCs that do not undergo EMT.
Reports on Wnt/β-catenin mutations in poorly differentiated HCCs are limited. Inagawa et al. examined nuclear β-catenin accumulation in solitary HCCs, including 24% poorly differentiated tumors under 30 mm, and found that nuclear β-catenin negatively correlated with mortality in well-differentiated HCC, whereas it was a significant poor prognostic factor in poorly differentiated tumors [22]. They also observed that nuclear β-catenin accumulation was associated with reduced plasma membrane E-cadherin expression, a critical adhesion protein that interacts with β-catenin and suppresses tumor invasion. Reduced E-cadherin expression correlates with β-catenin nuclear localization and has been identified as a risk factor for recurrence post-surgery. Additionally, Yamashita et al. demonstrated that EpCAM is a Wnt/β-catenin target gene, and EpCAM-positive HCC cells display activated Wnt/β-catenin signaling, epithelial morphology, high tumorigenicity, and poor prognosis [23–25].
Downstream Wnt/β-catenin effectors define HCC phenotypes
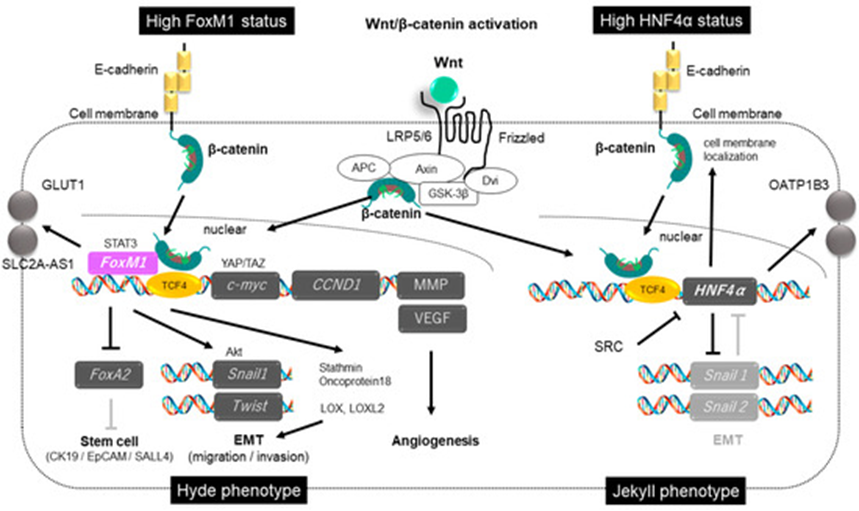
The apparently conflicting effects of canonical Wnt/β-catenin activation on HCC malignancy and prognosis may be explained by the differential expression of downstream master regulators. Yamashita et al. suggested that the mutually exclusive expression of HNF4α and FOXM1 underlies this duality [26] (Figure 1). In well- to moderately differentiated HCCs, β-catenin and glutamine synthetase (GS) are highly expressed, whereas their expression is less frequent in poorly differentiated HCCs (Figure 3). HNF4α, which identifies genes characteristic of mature hepatocytes, is predominantly expressed in less aggressive tumors, while FOXM1 expression is associated with poorly differentiated HCCs that express stem cell markers [26] (Figure 3).
|
|
|
Figure 3. Wnt/β-Catenin Dual Phenotypes: Jekyll vs. Hyde |
(Left panel) HCC cells with elevated FOXM1 expression show increased nuclear accumulation of β-catenin, which activates transcription of genes such as c-myc and CCND1. This triggers EMT and the acquisition of stem-like traits, leading to an aggressive tumor behavior known as the Hyde phenotype. FOXM1 may also upregulate GLUT1, enhancing metabolic activity.
(Right panel) HCC cells with higher HNF4α levels display β-catenin translocation into the nucleus, which stimulates HNF4α expression, suppresses EMT-related genes Snail1/2, and promotes β-catenin localization at the cell membrane. This generates a less aggressive, non-invasive tumor profile called the Jekyll phenotype. HNF4α also increases the expression of the bile acid transporter OATP1B3.
Jekyll phenotype and HNF4α function
Hepatocyte nuclear factors (HNFs) are essential regulators of liver development. Among them, HNF4α—a member of the steroid hormone receptor family—is highly expressed in the liver, moderately in the kidney and intestine, and minimally elsewhere [27]. Initially identified as a regulator of hepatocyte differentiation and adhesion, HNF4α also represses genes involved in hepatocyte proliferation, including cyclin D1, and its dysregulation has been linked to HCC development [27].
As a key transcriptional regulator, HNF4α coordinates the expression of multiple downstream genes governing hepatocyte growth, differentiation, and morphogenesis. Wnt/HNF4α interactions with LEF1 play a role in maintaining liver zonation [28]. HNF4α also inhibits EMT in HCC by restraining Wnt/β-catenin activity and reinforcing membrane localization of β-catenin [29]. This regulatory mechanism is characteristic of well-differentiated HCCs with lower vascular invasion, metastasis, and AFP levels. Yang et al. demonstrated that HNF4α forms a negative feedback loop on Wnt/β-catenin signaling, suppressing EMT transcription factors Snail and Slug [29] (Figure 3).
Two promoters of HNF4α, P1 and P2, produce transcriptional isoforms that are differentially expressed in HCC and colon cancer [30]. P1-HNF4α, predominantly expressed in adult liver, represses tumor-promoting genes including c-myc, cyclins, and EMT-related factors in a circadian manner [30]. In contrast, P2-HNF4α aberrant expression is associated with HCC development and strong repression of circadian genes such as ARNTL/BMAL1 [30]. In normal hepatocytes, P1-HNF4α co-expresses with BMAL1. HNF4α also regulates miR-122, a tumor suppressor that inhibits HCC progression through targets such as ADAM17, which is critical for liver tumorigenesis [31].
Imaging signatures of the jekyll phenotype
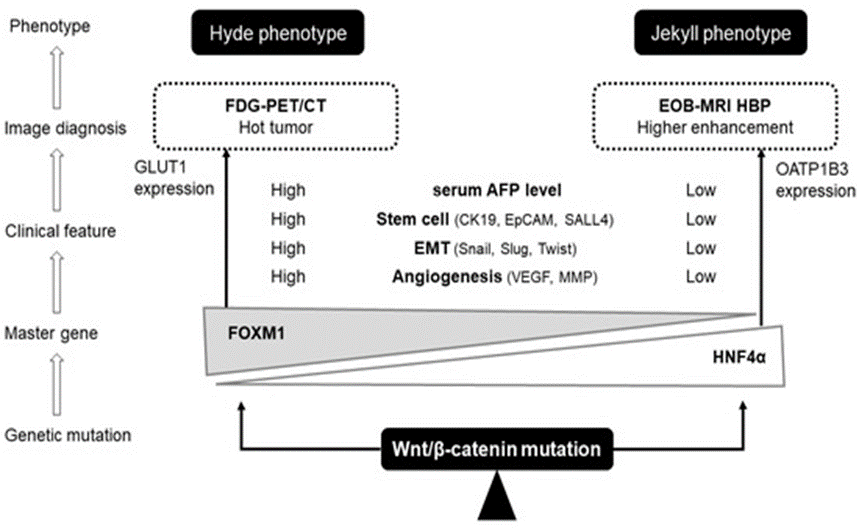
Tumors displaying cholestasis and high-intensity signals on Gd-EOB-DTPA-enhanced MRI—termed green hepatomas—typically exhibit favorable prognosis and frequently carry CTNNB1 mutations. These tumors show elevated OATP1B3 expression and are usually negative for cancer stem cell markers such as CK19 and EpCAM (Figure 4).
|
|
|
Figure 4. Imaging-Based Identification of Wnt/β-Catenin Activation in HCC |
The downstream effectors of canonical Wnt/β-catenin signaling, HNF4α and FOXM1, define two distinct HCC phenotypes. The Jekyll phenotype, characterized by well-differentiated morphology and limited metastasis and vascular invasion, is strongly linked to high HNF4α expression. HNF4α upregulates the bile acid transporter OATP1B3, enabling enhanced uptake of hepatocyte-specific contrast agents, which manifests as higher signal intensity in the hepatobiliary phase of Gd-EOB-DTPA-enhanced MRI. Conversely, the Hyde phenotype, associated with poor differentiation, extensive metastasis, and vascular invasion, correlates with elevated FOXM1 expression. FOXM1 promotes GLUT1 expression and is detected as hypermetabolic (“hot”) nodules on FDG-PET/CT.
Jekyll phenotype and imaging biomarkers
Gd-EOB-DTPA-enhanced MRI is widely employed for HCC detection due to its liver-specific contrast agent, which is transported into hepatocytes via OATP1B3. This property allows EOB-MRI to serve as a non-invasive imaging biomarker for CTNNB1 mutation prediction. Studies have shown that higher OATP1B3 expression correlates with greater hepatobiliary enhancement, indicating active Wnt/β-catenin signaling [6, 7]. Immunohistochemistry and RNA sequencing confirmed that OATP1B3 upregulation accompanies Wnt/β-catenin pathway activation [7]. For well-to-moderately differentiated HCC, Gd-EOB-DTPA-enhanced MRI predicted Wnt activation with 78.9% sensitivity, 81.7% specificity, and 81.2% accuracy at a relative enhancement ratio (RER) cutoff of 0.90 [7]. Moreover, co-activation of Wnt/β-catenin and HNF4α appears critical for OATP1B3 overexpression, leading to pronounced hepatobiliary enhancement in MRI [32]. Using this imaging approach, our prior study suggested that non-invasive identification of Wnt-activated HCC could help predict resistance to immune checkpoint inhibitors [9].
Hyde phenotype and FOX transcription factors
Canonical Wnt/β-catenin signaling is essential for proliferation and maintenance of both normal and cancer stem cells. In HCC, a subset of Wnt-activated tumors exhibits aggressive features, including EMT activation and expression of stem cell markers such as CK19, EpCAM, and SALL4 [22, 26]. These poorly differentiated tumors often display elevated Ki67 proliferation indices [24] and are strongly associated with FOXM1 activation [26, 33–36].
FOX proteins are evolutionarily conserved transcription factors involved in embryonic development and tissue homeostasis. Humans express 44 FOX family members grouped into 19 subclasses (A–S) based on the DNA-binding forkhead domain [37]. Despite sequence similarity, their transcriptional activity is context-specific, with many FOX factors showing restricted temporal and spatial expression. Approximately half of mammalian FOX proteins interact with the Wnt pathway, regulating cancer initiation and progression. Within this family, FOXM1 and FOXG1 act as Wnt activators in HCC. FOXM1, a key regulator of cell cycle progression, is directly controlled by canonical Wnt/β-catenin signaling and contributes to proliferation, survival, metastasis, and drug resistance in cancer cells [36]. FOXG1 overexpression also promotes apoptosis resistance and metastatic potential in various malignancies.
FOXM1 enhances nuclear β-catenin accumulation in both normal and tumor cells, facilitating transcription of Wnt target genes such as c-myc and cyclin D1 [36, 38]. Wnt3a stimulation further stabilizes FOXM1, promoting its binding to β-catenin and enhancing the transcriptional activity of downstream genes. Cyclin D1-positive HCCs frequently demonstrate aggressive clinical behavior, suggesting that the Wnt/FOXM1 axis drives the aggressive Hyde phenotype (Figure 3).
Continuous daily administration of cell-penetrating ARF peptides in mouse HCC models with active FOXM1 has been shown to suppress tumor proliferation, inhibit angiogenesis, and significantly enhance apoptosis in the tumor regions [39]. The P19 ARF peptide (equivalent to human p14ARF) exerts tumor-suppressive effects through both p53-dependent and p53-independent mechanisms [39]. The p14ARF tumor suppressor gene plays a critical role in HCC pathogenesis and exhibits alterations such as genetic mutations, promoter hypermethylation, and loss of heterozygosity at chromosome 9p21 [40]. High FOXM1 expression has been repeatedly associated with tumor progression and poor prognosis across multiple malignancies, including HCC, where it correlates with EMT features and cancer stem cell characteristics [26, 33–35]. FOXM1 also drives transcription of STMN1, which enhances cell motility, and upregulates lysyl oxidase (LOX) and LOXL2, contributing to the formation of pre-metastatic niches in distant organs. Furthermore, FOXM1 stimulates VEGF expression in HCC cells, supporting angiogenesis and reinforcing an aggressive tumor phenotype [41].
Glucose metabolism and the warburg effect
Cellular energy metabolism is highly conserved across organisms, and inhibition of metabolic pathways can influence gene expression through epigenetic mechanisms. Many proto-oncogenes increase the expression of glucose transporters and glycolytic enzymes, making tumor cells heavily reliant on glycolysis [42]. Tumor microenvironments are often characterized by low glucose availability due to high consumption by cancer cells [43]. Additionally, hypoxia, low pH from lactate accumulation, and nutrient deprivation create a challenging microenvironment. The Warburg effect describes the preference of tumor cells to metabolize glucose to lactate even in the presence of oxygen, allowing adaptation to nutrient-limited conditions [44]. In HCC, elevated GLUT1 expression correlates with poorer survival outcomes [45]. The anti-apoptotic protein PARP14 has also been implicated in promoting the Warburg effect, with higher PARP14 levels linked to worse prognosis in HCC [46].
Imaging biomarkers of the hyde phenotype
Aggressive HCC with activated Wnt/β-catenin signaling—characterized by HNF4α negativity and FOXM1 positivity—remains challenging to diagnose non-invasively. FOXM1 transcription is regulated via a STAT3 binding site in its promoter, and FOXM1 controls GLUT1 expression through the SLC2A1-AS1/STAT3 axis [47] (Figure 4). Knockdown of STAT3 significantly reduces FOXM1 and GLUT1 expression at both transcriptional and protein levels and lowers FOXM1 promoter activity [47]. FDG-PET/CT imaging has been used to detect high metabolic activity associated with FOXM1, with studies validating this approach in breast cancer and the Cancer Genome Atlas database [48]. Consequently, FDG-PET/CT may be suitable for detecting aggressive, Wnt/β-catenin-positive HCC (Hyde phenotype), whereas EOB-MRI remains ideal for identifying the less aggressive Jekyll phenotype.
Alignment with molecular classifications and implications for therapy
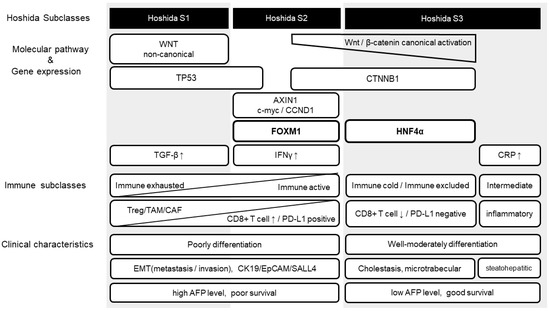
The current first-line treatment for unresectable HCC with preserved liver function (Child-Pugh class A) is a combination of immune checkpoint inhibitors (ICIs) and VEGF-targeted therapies [49, 50]. Despite this, approximately 20% of patients exhibit primary resistance, often due to activation of Wnt/β-catenin signaling [8]. Canonical Wnt/β-catenin activation by ligands such as Wnt3a, Wnt1, and Wnt7 gives rise to two phenotypes of HCC. One is driven by HNF4α induction, as observed in specific Hoshida S3 HCCs (Figure 5). In this subclass, Wnt/β-catenin signaling suppresses recruitment of CD103+ dendritic cells, downregulates chemokines such as CCL4/5, CXCL1, and CCL20, and induces ATF3 expression, creating an “immune excluded” or “immune cold” tumor microenvironment [5, 8]. HCC heterogeneity means that even a single nodule harboring Wnt/β-catenin mutations with HNF4α expression can reduce the efficacy of anti-PD-1/PD-L1 therapies [9].
|
|
|
Figure 5. Comparison with previous HCC subclasses |
Hoshida subclass 1 (S1) is characterized by an activated non-canonical Wnt/TGF-β axis, leading to “immune hot” tumors enriched with tumor-infiltrating T lymphocytes, though some cases display T-cell exhaustion. Hoshida subclass 2 (S2) frequently harbors c-myc and CCND1 mutations, shows elevated serum AFP, exhibits stem cell-like features, and demonstrates enhanced EMT. FOXM1 expression is notably upregulated in this subclass, suggesting that certain canonical Wnt/β-catenin-activated HCCs may fall into S2. This subclass likely represents an immune-active yet exhausted phenotype. A subset of Hoshida subclass 3 (S3) shows favorable prognosis, harboring CTNNB1 mutations indicative of canonical Wnt/β-catenin activation, low AFP levels, and well-to-moderate differentiation. These tumors are typically immune cold with fewer tumor-infiltrating T cells, which may limit responsiveness to immune checkpoint inhibitors (ICIs).
Activation of FOXM1 via canonical Wnt/β-catenin signaling likely corresponds to the Hoshida S2 subclass, which is characterized by high AFP, stemness features, and a macrotrabecular/compact histological pattern. Oncogenes such as YAP/TAZ and stem cell markers including EpCAM, CK19, and SALL4 are also upregulated. The immune landscape of S2 shows increased CCL5, abundant TILs, enhanced IFNγ signaling, upregulation of immunosuppressive receptors, and strong antigen presentation, aligning with the aggressive Hyde phenotype and a microenvironment amenable to ICI therapy [51]. FOXM1 and β-catenin complexes promote c-myc transcription, and c-myc-expressing HCC cells have been reported to evade immune surveillance through the canonical Wnt/β-catenin pathway [52]. Wnt/FOXM1 also regulates MMP-9, facilitating immature dendritic cell migration through the basement membrane. S2 HCC is prone to vascular invasion and poor prognosis but responds to Wnt signaling inhibitors [23]. Moreover, SALL4 interacts with histone deacetylases (HDACs) to form chromatin remodeling complexes; HDAC inhibitors may reduce EpCAM-positive stem cell populations and downregulate SALL4 expression. Recently developed FOXM1 inhibitors have decreased β-catenin activity and tumor growth in xenograft models.
Non-canonical Wnt ligands, such as Wnt5a, Wnt6, and Wnt11, preferentially activate the Wnt/TGF-β axis, corresponding to Hoshida S1 tumors [21]. These tumors exhibit immune infiltration but show an exhausted phenotype with resistance to ICIs [5].
In studies of resected HCC specimens, approximately 30–40% were Wnt/β-catenin-positive, while OATP1B3-positive HCCs detectable by Gd-EOB-DTPA-enhanced MRI comprised 15–20%, implying the presence of a Wnt/β-catenin-positive, HNF4α-negative, FOXM1-positive aggressive subset. However, surgical cohorts are biased, as patients with vascular invasion or multi-organ metastases are generally excluded. Future studies should validate these findings in more advanced HCC samples.
Conclusion
HNF4α acts as a tumor suppressor by repressing EMT and is predominantly expressed in well-to-moderately differentiated HCCs, which are associated with low AFP levels and favorable prognosis. As a Wnt/β-catenin target, HNF4α also promotes OATP1B3 expression, allowing non-invasive detection of nodules with high hepatobiliary enhancement in Gd-EOB-DTPA-enhanced MRI.
Conversely, FOXM1, downstream of Wnt/β-catenin, defines an aggressive HCC subset with poor prognosis. These tumors show high AFP, positive stem cell markers, EMT features, and reduced E-cadherin, while lacking HNF4α expression. They are not detected as high-enhancement nodules on EOB-MRI but can be visualized through GLUT1 expression using FDG-PET/CT.
HCCs with active Wnt/β-catenin signaling generally exhibit primary resistance to first-line ICIs. Accurate detection of this pathway activation is therefore crucial for guiding treatment in advanced HCC, particularly when biopsy samples are unavailable.
Acknowledgments: None
Conflict of Interest: None
Financial Support: This work was supported in part by a Grant-in-Aid for Scientific Research from the Japan Society for the Promotion of Science (KAKENHI: 21K07184, N. Nishida, and 21K07950, M Kudo) and a grant from the Smoking Research Foundation (N. Nishida).
Ethics Statement: None