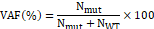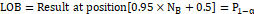Circulating tumor DNA (ctDNA) has emerged as a powerful tool for liquid biopsy (LB) to guide personalized treatment decisions in oncology. Effective clinical application requires well-defined ctDNA thresholds to detect residual disease and monitor tumor burden dynamics during therapy. In this study, we evaluated the clinical validity of the limit of blank (LOB) and limit of quantification (LOQ) for assays targeting key somatic mutations in colorectal cancer (CRC), including BRAF p.V600E and KRAS p.G12/p.G13, across 212 plasma samples. Using the LOB to define ctDNA positivity, we observed strong agreement with evidence of metastasis or disease recurrence. Similarly, applying the LOQ as a threshold for quantitative ctDNA changes reliably reflected tumor burden fluctuations during chemotherapy and throughout disease progression. Comparison with conventional markers, such as carcinoembryonic antigen (CEA) and circulating free DNA (cfDNA) levels, demonstrated that ctDNA-based LB provides superior accuracy in detecting residual disease and predicting tumor burden changes. These findings highlight the potential of validated ctDNA assays to enhance monitoring and clinical management of CRC patients.
Introduction
Cell-free DNA (cfDNA) is released into the bloodstream from both normal and tumor cells [1, 2]. Within this pool, the fraction of tumor-derived circulating tumor DNA (ctDNA) serves as a biomarker for the presence of cancer and overall tumor burden, typically assessed through the detection of tumor-specific mutations [3-5]. In addition to ctDNA, other liquid biopsy (LB) components such as circulating tumor cells (CTCs) have been explored for clinical applications. While CTCs provide detailed single-cell molecular information [6, 7], multiple studies have demonstrated that ctDNA profiles closely mirror the genetic landscape of primary tumors and metastases [8, 9], suggesting a higher potential for clinical translation [10]. Both ctDNA and CTCs share the advantages inherent to LB—minimally invasive sampling and the ability to perform repeated measurements irrespective of patient condition, enabling monitoring at any point during the disease course [11-13].
In certain cancers, such as non-small cell lung cancer (NSCLC) and breast cancer, ctDNA-based LB is already integrated into treatment decision-making and even covered by insurance [14, 15]. For colorectal cancer (CRC), LB is anticipated to become a standard tool once its clinical utility is confirmed in key applications, including: (1) detecting residual disease post-surgery to guide adjuvant therapy decisions, (2) monitoring recurrence, and (3) real-time assessment of treatment response during chemotherapy. This is particularly important as conventional CRC monitoring methods, such as carcinoembryonic antigen (CEA) testing, have notable limitations. Prognostication based on postoperative CEA combined with clinicopathologic features of the resected tumor often lacks accuracy [16]. Moreover, CEA measurements, CT scans, and colonoscopies have limited sensitivity for detecting recurrence and provide only modest benefit in treatment monitoring [17-19].
For ctDNA to be implemented reliably in routine clinical practice, its assay performance—including diagnostic sensitivity and specificity for variant detection—must be thoroughly validated. CtDNA levels can be extremely low (<1% variant allele frequency, VAF) after surgery or chemotherapy [3, 20, 21], making accurate detection challenging due to assay noise and non-tumor-derived signals, such as those arising from clonal hematopoiesis. Clinicians therefore require variant-specific cutoffs for ctDNA positivity to reliably identify residual disease and recurrence [3, 22, 23], as well as precise quantification of ctDNA levels to track tumor burden over time [23]. According to CLSI guidelines on establishing clinical laboratory measurements, cutoffs for detection (limit of blank, LOB) and quantification (limit of quantification, LOQ) must be determined for clinical reporting and are not equivalent to the general assay limit of detection (LOD) typically provided by LB assay vendors [24].
In this study, we established and validated LOB and LOQ thresholds for variant-specific ctDNA assays, using them as cutoffs for ctDNA detection and quantification to assess residual disease, recurrence, and tumor burden. A total of 124 plasma samples from 22 CRC patients were analyzed, and the clinical validity of ctDNA results was compared with cfDNA levels and CEA measurements.
Materials and Methods
Study design and participants
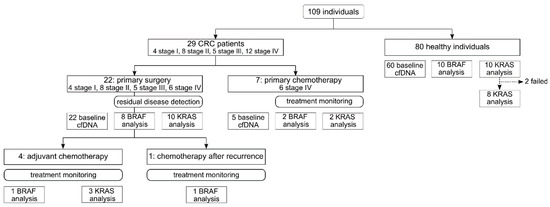
Between October 2018 and March 2021, a total of 212 plasma samples were collected from 29 CRC patients (UICC stage I–IV) and 80 healthy volunteers aged 19–87 years (Figure 1) [25]. Patients were enrolled prior to the initiation of any therapy, including surgery or chemotherapy. Healthy participants were required to have no prior cancer diagnosis, no known tumor predisposition, and not be pregnant. As KRAS and BRAF are autosomal genes, participant sex was not considered a confounding factor. To control for age-related differences between younger healthy controls and older patients, lymphocyte genomic DNA (gDNA) was analyzed to rule out clonal hematopoiesis in ctDNA-positive samples, which is more prevalent in older individuals [26].
|
|
|
Figure 1. Overview of Study Workflow. BRAF analysis refers to the BRAF p.V600E variant, whereas KRAS analysis includes one of the following: KRAS p.G12 [A/C/D/R/S/V] or KRAS p.G13D. |
Out of the 29 enrolled colorectal cancer patients, 22 underwent primary surgical intervention. Plasma samples were collected up to five days before surgery and again between four and fifty days afterward (Supplementary Data—Residual Disease). Among these 22 patients, tumor variant status was determined in 18 individuals (8 with BRAF p.V600E and 10 with KRAS p.G12/p.G13). For these 18 patients, ctDNA was analyzed both before and after surgery to evaluate residual disease. Four patients from this group received adjuvant chemotherapy (1 BRAF p.V600E, 3 KRAS p.G12/p.G13), and one patient underwent chemotherapy following disease recurrence. ctDNA monitoring was performed throughout treatment in all five cases.
The remaining seven patients initiated treatment with chemotherapy alone. Baseline plasma was collected within five days prior to therapy, with additional samples taken at multiple intervals during the treatment course. Tumor variant status was known for four of these patients (2 BRAF p.V600E, 2 KRAS p.G12/p.G13), and ctDNA analysis was used to track therapeutic response for each case.
In total, ctDNA assays were performed for 18 patients (87 plasma samples) pre- and post-surgery using the limit of blank (LOB) as the threshold for residual disease detection. An additional nine patients (76 plasma samples) underwent ctDNA monitoring to assess whether the limit of quantification (LOQ) could reliably reflect tumor burden dynamics and treatment response during chemotherapy. Detailed protocols for sample collection and processing are described in the Supplementary Methods. The study received approval from the Bavarian Medical Association Ethics Committee (No. 17059) and was registered with the German Clinical Trials Registry (DRKS00012890). Neither patients nor clinicians were aware of the ctDNA results, and all participants provided informed consent prior to the collection of blood and tissue samples.
Sample processing and droplet digital PCR (ddPCR)
Methods for cfDNA extraction and preparation for ddPCR are described in the Supplementary Methods.
Droplet digital PCR assays
ddPCR analysis was carried out using the Bio-Rad BRAF p.V600E single-probe assay (#dHsaMDV2010027) and the KRAS p.G12/p.G13 screening kit (#1863506) on the QX200 platform (Bio-Rad), according to the manufacturer’s instructions (Supplementary Methods). The KRAS kit reports a positive result when any of the seven specified variants are present but does not identify which variant is detected. For each assay, 20–30 ng of cfDNA was analyzed. Gating and variant calling were performed using mutant and wild-type controls with the QX Manager software (Bio-Rad, v.1.1).
ctDNA was quantified in terms of the mutant VAF, which describes the abundance of detected mutant alleles within all detected alleles and is calculated as follows:
|
|
(1) |
Equation (1). Variant allele frequency. VAF: variant allele frequency; Nmut: number of mutant alleles; NWT: number of wild type alleles.
Samples with VAFs > LOB were defined with ctDNA positive status, and samples with VAFs > LOQ harbored quantifiable ctDNA VAFs.
Establishing cutoffs for ctDNA positivity and quantifiable levels
The limits of blank (LOB) and quantification (LOQ) for the ddPCR assays were determined following CLSI guidelines [24] and expressed with 95% confidence intervals. The LOB reflects the assay’s specificity by defining the highest signal observed in negative controls, thus representing the threshold below which results are considered negative. To establish this, over 60 wild-type control samples were analyzed for each assay, resulting in LOB values of 0.02% VAF for BRAF p.V600E and 0.11% VAF for KRAS p.G12/p.G13. The LOQ was determined using at least 40 replicates of positive control samples containing the respective variant at a provisional LOQ, aiming for a minimum of 80% precision and 90% trueness. This yielded LOQ values of 0.52% VAF for BRAF p.V600E and 0.41% VAF for KRAS p.G12/p.G13. These thresholds were validated using 20–30 ng of input cfDNA per reaction [27].
Establishing cutoff for elevated cfDNA levels
Elevated plasma cfDNA levels have previously been reported in CRC patients [28–31]. To evaluate whether cfDNA quantification could provide additional clinical insight, baseline plasma cfDNA levels from 60 healthy individuals were compared with 128 samples from 29 CRC patients. cfDNA concentrations were measured using the High-Sensitivity NGS Fragment Analysis Kit (Agilent, #DNF-474-0500) on the Fragment Analyzer platform (Agilent). In line with CLSI recommendations [24], a minimum of 60 samples is necessary to establish an LOB with 95% confidence, supporting the robustness of using 60 healthy individuals as a reference. Median cfDNA concentration in healthy controls was 2.5 ng/mL, while CRC patients showed significantly higher levels at baseline (median 11.6 ng/mL; Wilcoxon test, p = 2.64 × 10⁻¹¹).
With 95% specificity, a cutoff at 5.6 ng/mL cfDNA was established to differentiate between CRC patients and healthy individuals, as follows:
|
|
(2) |
Equation (2). Determination of the cfDNA cutoff. LOB: limit of blank; NB: number of negative control measurements; P(1−α): percentile at the level of 1 − α.
Linear interpolation between the results of the next lower and the next higher rank position was used to determine the cfDNA cutoff [24].
CEA measurement
Plasma carcinoembryonic antigen (CEA) concentrations were measured using the Human CEA ELISA Kit (Biorbyt, Cambridge, UK, Cat# orb438561) according to the manufacturer’s protocol.
Statistical analysis
Comparisons of cfDNA concentrations between CRC patients and healthy controls were performed using the Wilcoxon rank-sum test. Longitudinal changes in ctDNA VAFs, cfDNA, and CEA levels throughout disease progression were assessed using the Kruskal–Wallis test. To correct for multiple comparisons, p-values were adjusted using the Bonferroni method. Sample size calculations for a statistical power of 0.8 indicated that at least 18 samples per group were needed for the Wilcoxon test and 9 samples per group for the Kruskal–Wallis test (G*Power version 3.1.94, https://gpower.software.informer.com/3.1/, accessed 3 January 2022). Statistical significance was defined as p < 0.05. All analyses were conducted using the stats package in R version 4.0.3 (https://www.r-project.org/, accessed 3 January 2022).
Results and Discussion
Validation of ctDNA positivity cutoffs and quantifiable VAFs in reference samples
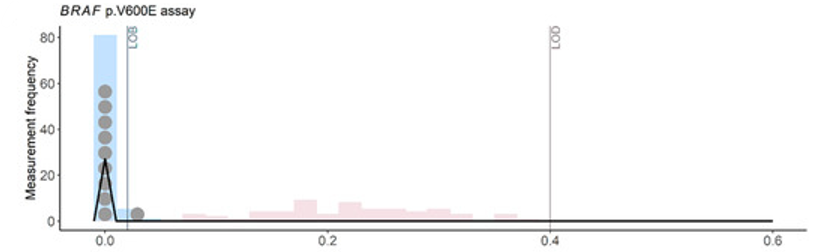
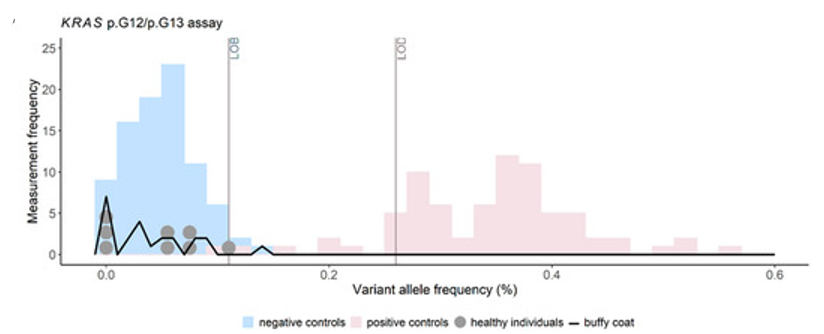
Accurate definition of ctDNA positivity is essential for reliably detecting residual disease and recurrence. In accordance with CLSI guidelines [24], thresholds were established using well-characterized wild-type reference materials. In this study, plasma samples were considered ctDNA-positive when the VAFs of BRAF p.V600E or KRAS p.G12/p.G13 exceeded their respective LOBs (0.02% and 0.11% VAF) (Figure 2)(blue) [27]. For KRAS p.G12/p.G13, as the assay cannot discriminate between individual variants, a single combined cutoff was applied.
|
|
|
a) |
|
|
|
b) |
|
Figure 2. Validation of ctDNA Positivity Cutoffs |
The clinically verified limit of blank (LOB) for positive ctDNA status was established using measurements from healthy control plasma samples (grey dots), which generally displayed ctDNA signals below the defined positivity thresholds for both BRAF p.V600E (A) and KRAS p.G12/p.G13 (B) assays. Importantly, clonal hematopoiesis did not interfere with the tumor-specific ctDNA signal, as ctDNA measured in lymphocyte gDNA from buffy coat samples remained below the LOB (black line). Histograms of negative (blue) and positive (pink) reference material measurements facilitated the definition of the LOB and the limit of detection (LOD), as previously described in analytical validation [27].
Accurate monitoring of tumor dynamics during therapy requires defining the quantitative threshold above which ctDNA levels can be reliably measured, the limit of quantification (LOQ). In this study, quantitative assessment of ctDNA VAFs was possible for BRAF p.V600E and KRAS p.G12/p.G13 variants exceeding the LOQ of 0.52% and 0.41%, respectively [24, 27].
Clinical verification of ctDNA cutoffs in healthy plasma
To confirm the clinical applicability of previously validated LOB thresholds, ten healthy control plasma samples were tested with the BRAF p.V600E and KRAS p.G12/p.G13 assays (Figure 2). Two KRAS analyses failed, leaving eight evaluable samples. None of the eight KRAS and only one out of ten BRAF control samples exceeded the respective ctDNA positivity cutoffs. The single BRAF-positive signal measured 0.03% VAF, which is below the 15% allowable exceedance for verification [24]. Since this testing was conducted under the same conditions as analytical validation and the predefined criteria were met, the ctDNA positivity cutoffs for both assays were clinically confirmed and can be applied to residual disease and recurrence analyses (Figure 2)(grey dots).
Tumor specificity of positive ctDNA signals
To ensure that ctDNA positivity reflects tumor-derived signals rather than clonal hematopoiesis, lymphocyte gDNA from all ctDNA-positive CRC patients was analyzed. No BRAF signals (0/27) and only one KRAS signal (1/23) exceeded the ctDNA positivity threshold (Figure 2) (black line). In this single KRAS-positive case, the lymphocyte gDNA VAF (0.14%) was lower than the corresponding plasma VAF (1.48 ± 0.39%), confirming that the plasma sample was still considered ctDNA-positive. These results demonstrate that clonal hematopoiesis did not confound ctDNA detection and that positive ctDNA status in plasma reliably represents tumor-derived DNA.
Baseline cfDNA levels outperform ctDNA positivity and CEA
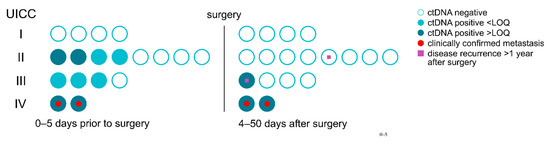
Applying the validated ctDNA cutoffs, 9 of 18 patients were classified as ctDNA-positive at baseline. The frequency of ctDNA positivity increased with advancing UICC stage: 0/4 in stage I, 4/8 in stage II, 3/4 in stage III, and 2/2 in stage IV (Figure 3) (Supplementary Methods—Residual disease). These findings are consistent with prior studies indicating that higher tumor stages release greater amounts of ctDNA into circulation [22, 28–30].
|
|
|
Figure 3. ctDNA Positivity in CRC Patients Across Stages I–IV for Residual Disease Assessment |
As a comparative biomarker, plasma levels of carcinoembryonic antigen (CEA), a standard marker in CRC, were measured. Elevated CEA values were defined according to established thresholds: >2.5 ng/mL in non-smokers and >5 ng/mL in smokers [32, 33]. At baseline, only 2 of 18 patients displayed elevated CEA levels, with no stage I or II patients affected, one stage III patient, and one stage IV patient showing increased levels.
For total cfDNA, a clinical threshold of 5.6 ng/mL was established to define elevated plasma cfDNA concentrations relative to healthy controls. Using this cutoff, 12 of 18 patients exhibited elevated cfDNA at baseline: two stage I, four stage II, four stage III, and two stage IV patients. Given that both ctDNA positivity and elevated cfDNA measurements were determined with 95% specificity, cfDNA demonstrated superior baseline diagnostic performance compared to ctDNA and CEA alone. Combining all three biomarkers did not further enhance detection at baseline.
ctDNA positivity predicts residual disease and recurrence
To evaluate the utility of ctDNA for predicting residual disease post-surgery, variant allele frequencies (VAFs) of BRAF p.V600E and KRAS p.G12/p.G13 were measured in plasma cfDNA from 18 CRC patients at baseline and 4–50 days post-surgery (Figure 3). All patients underwent complete locoregional R0 resection.
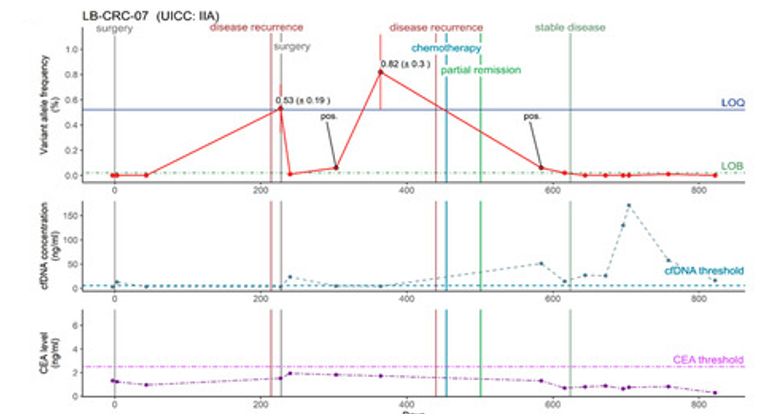
At baseline, ctDNA was detectable (VAF > LOB) in 9 of 18 patients. For BRAF variants, this included one stage II, one stage III, and one stage IV patient; for KRAS variants, it included three stage II, two stage III, and one stage IV patient. Patients who were ctDNA-negative prior to surgery remained negative postoperatively. None of these patients developed metastases within 50 days after surgery, supporting the high specificity of ctDNA analysis. Remarkably, one patient later experienced two instances of clinical recurrence, both of which were preceded by detectable ctDNA up to three months before clinical diagnosis (Figures 3 and 4a) (LB-CRC-07).
|
|
|
a) |
|
|
|
b) |
|
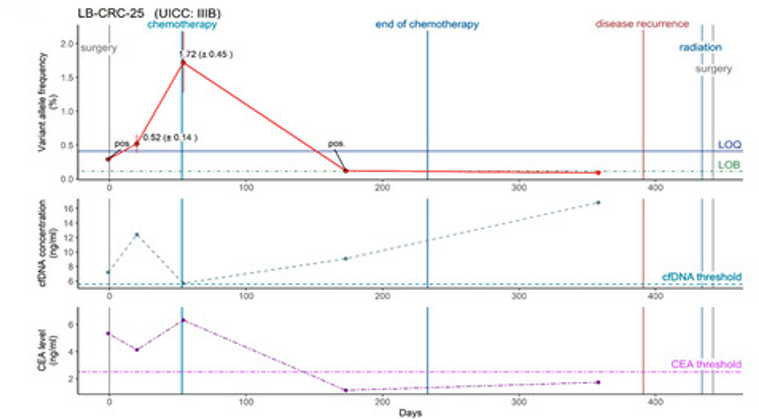
Figure 4. ctDNA (line 1), cfDNA (line 2) and CEA (line 3) analysis throughout the course of the disease in two CRC patients (a) LB-CRC-07 and (b) LB-CRC-25, with recurrence. |
Among the nine patients who exhibited positive ctDNA status at baseline, three continued to show ctDNA presence in plasma following surgery, indicating molecular residual disease (MRD). This subgroup included one stage III patient and two stage IV patients, all with variant allele frequencies (VAFs) exceeding the limit of quantification. Both stage IV patients had metastases confirmed clinically, whereas the stage III patient, despite lacking radiologically detectable metastases, was considered high-risk and received adjuvant chemotherapy. The treatment resulted in the clearance of ctDNA during therapy, although disease recurrence occurred more than one year after surgery, approximately six months following completion of chemotherapy. While ctDNA did not predict recurrence in one patient shortly before clinical manifestation, these findings collectively support the utility of ctDNA as a complementary biomarker for MRD detection and early recurrence prediction.
The predictive performance of ctDNA was compared with conventional biomarkers, including circulating free DNA (cfDNA) and carcinoembryonic antigen (CEA). Among the three patients with MRD, two had clinically confirmed metastases. In one patient, cfDNA was elevated from baseline to one month post-surgery, whereas CEA remained within the normal range, indicating that cfDNA, but not CEA, identified MRD. In another patient, cfDNA measurements were not available during the immediate post-surgical period, but elevated CEA levels detected MRD. In the third patient, who later experienced recurrence over a year after surgery and six months post-adjuvant chemotherapy, cfDNA concentrations were consistently elevated but did not show dynamic changes that could predict MRD or recurrence. CEA levels in this patient were initially elevated postoperatively but normalized several months before recurrence, accurately reflecting MRD but failing to anticipate relapse, similar to ctDNA findings. In another patient with eventual recurrence, cfDNA remained normal throughout the first year, and only increased after chemotherapy for systemic nodal progression; CEA remained within the normal range throughout. These observations demonstrate that ctDNA provides superior sensitivity for detecting MRD and predicting recurrence compared with cfDNA and CEA.
Beyond residual disease and recurrence detection, quantitative analysis of ctDNA VAF was employed to monitor chemotherapy response. In nine patients, changes in ctDNA levels were tracked to assess therapeutic efficacy. Among four patients receiving primary chemotherapy, all with stage IV disease, baseline ctDNA VAFs ranged from approximately 9% to 48%. Within the first month of treatment, ctDNA levels declined substantially, in some cases to undetectable levels, reflecting effective response. For patients receiving adjuvant chemotherapy after surgery, MRD was detected in two out of four cases prior to treatment; both patients exhibited a decrease in ctDNA VAF to undetectable levels, indicating favorable response. The remaining two patients had no detectable MRD before therapy, and ctDNA remained undetectable during follow-up over one year. In a stage II patient receiving palliative chemotherapy following systemic nodal progression more than a year post-surgery, ctDNA VAF decreased from 0.82% to undetectable, corresponding with partial remission and disease stabilization. Collectively, these data demonstrate that precise quantification of ctDNA VAF reliably reflects tumor response, with increasing levels signaling treatment resistance and decreasing levels indicating therapeutic efficacy.
To evaluate the predictive performance of quantitative ctDNA VAF measurements in monitoring chemotherapy response, these data were compared with cfDNA and CEA levels. Prior to treatment, ctDNA was detectable in seven of nine patients, with VAFs ranging from 0.52% (±0.14%) to 47.75% (±7.11%). In all cases, fluctuations in ctDNA VAFs throughout chemotherapy accurately reflected clinical responses or resistance.
For the two patients without measurable ctDNA prior to chemotherapy, cfDNA concentrations were elevated. In one patient, cfDNA levels normalized within a year, whereas in the second patient, cfDNA oscillated and remained elevated approximately one year after treatment initiation. CEA levels remained within normal limits for both patients throughout therapy, indicating that neither cfDNA nor CEA provided reliable information on treatment response or resistance.
Among patients with quantifiable ctDNA, a stage II patient with a BRAF variant showed elevated cfDNA only after starting chemotherapy, which did not align with clinical evidence of partial remission and stable disease. CEA remained within normal limits throughout treatment. In a stage III patient with a KRAS variant, cfDNA remained elevated during therapy, while CEA levels were high at baseline but normalized over time. The remaining five patients had stage IV CRC, comprising three BRAF and two KRAS variants. In one patient, cfDNA and CEA measurements were only available after disease progression, both aligning with clinical findings. Another patient exhibited elevated cfDNA at baseline, which normalized after two months of chemotherapy, then increased again two months later, reflecting stable and progressive disease; CEA remained elevated throughout. In a third stage IV patient, cfDNA was consistently elevated except in a single sample, while CEA decreased to normal levels approximately 1.5 months after ctDNA became undetectable. The last two stage IV patients maintained elevated cfDNA levels, but CEA remained within normal limits in almost all samples. Collectively, cfDNA predicted chemotherapy response or resistance in only two patients, and CEA in three, whereas ctDNA VAFs accurately tracked treatment response in all cases.
These observations demonstrate that quantitative ctDNA measurements are more sensitive and reliable than cfDNA and CEA for monitoring response or resistance to chemotherapy, supporting ctDNA as a superior marker.
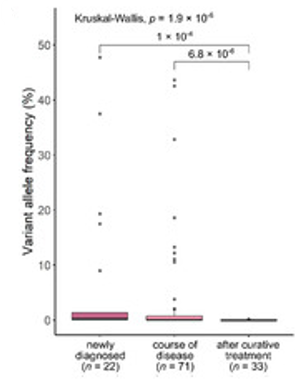
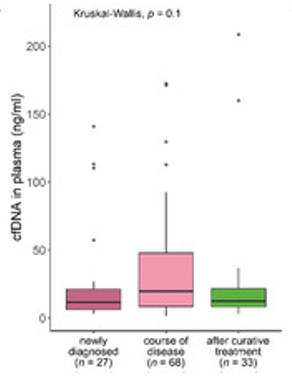
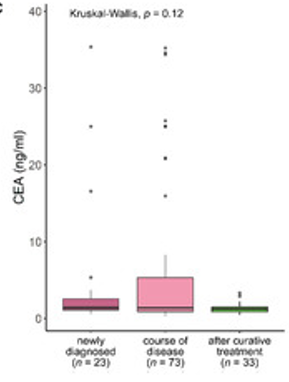
To further evaluate temporal changes, ctDNA VAFs, cfDNA concentrations, and CEA levels were analyzed across different stages of the disease, including baseline, during active disease, and after curative treatment. Significant differences in ctDNA VAFs were observed depending on the sampling time (p = 1.9 × 10⁻⁶), whereas cfDNA and CEA did not exhibit statistically significant variation (p = 0.1 and 0.12, respectively). These results suggest that accurate determination of ctDNA positivity and precise quantification of ctDNA VAFs using validated LOB and LOQ thresholds reliably reflect tumor burden at baseline and during active disease, as well as confirm tumor clearance following curative therapy. In contrast, cfDNA and CEA lack sufficient sensitivity to detect tumor burden fluctuations. These findings align with the observed performance of ctDNA for MRD and recurrence detection, as well as chemotherapy monitoring.
|
|
|
|
|
a) |
b) |
c) |
|
Figure 5. ctDNA VAFs, cfDNA concentration and CEA levels at different times in the course of the disease. (A) ctDNA quantification levels but not (B) cfDNA concentration and (C) CEA levels significantly differ at different times in the course of disease. |
||
Discussion
Circulating tumor DNA (ctDNA) offers a non-invasive, real-time method to assess tumor burden and detect mutation-specific signatures in cancer patients, making it useful for monitoring residual disease, recurrence, and tumor progression. For clinical use, it is critical to distinguish low-level ctDNA signals as truly tumor-derived, avoiding interference from technical artifacts or biological confounders such as clonal hematopoiesis [34]. Therefore, defining a clear cutoff for tumor-specific ctDNA positivity is essential. In this study, we established and clinically validated such a cutoff according to CLSI guidelines [24, 27], demonstrating that healthy control samples did not exceed this threshold and that clonal hematopoiesis did not interfere with positive ctDNA findings. This validation underscores that ctDNA above the defined threshold is tumor-specific, a key advantage over non-specific plasma markers such as CEA and cfDNA.
The utility of ctDNA positivity was evaluated for detecting residual disease and recurrence. Among 18 patients monitored after primary surgery, molecular residual disease (MRD) was identified in three individuals, two of whom had metastatic disease and one without immediate clinical evidence of recurrence. CtDNA positivity showed greater prognostic value than cfDNA or the commonly used CRC marker CEA, outperforming conventional markers with respect to residual disease detection and recurrence prediction [16]. Moreover, ctDNA allowed detection of recurrence several months prior to clinical manifestation, consistent with previous studies [35, 36]. These findings suggest that ctDNA can complement standard surveillance methods, which often have limited impact on overall survival or recurrence prediction and may increase patient burden and costs [37].
For chemotherapy monitoring, quantitative ctDNA assessment is essential. By applying a validated limit of quantification (LOQ), changes in ctDNA variant allele fractions (VAFs) accurately reflected tumor response or resistance in all patients, outperforming cfDNA and CEA measurements [27, 38]. Such precise quantification enables clinicians to interpret increases or decreases in ctDNA VAF as true tumor progression or response, supporting treatment decisions.
Although cutoff thresholds are assay-specific, our approach provides a framework for validating ctDNA assays for clinical use. Elevated cfDNA levels were observed in most patients at baseline, highlighting its potential as a supportive diagnostic marker, whereas ctDNA positivity and quantification provide more specific information for residual disease, recurrence, and treatment monitoring.
Limitations include the relatively small patient cohort and focus on BRAF and KRAS hotspot mutations, which limits applicability to patients with these variants [39, 40]. Inclusion of all disease stages may reduce power for stage-specific analysis but does not undermine the importance of defined cutoffs for clinical interpretation. Future expansion to untargeted ctDNA analyses and combination with additional liquid biopsy analytes, such as circulating tumor cells and exosomal miRNAs, may further enhance clinical utility [6, 7, 41-47]. Age differences between controls and patients were addressed by analyzing lymphocyte gDNA to exclude potential confounding from clonal hematopoiesis [26].
Conclusion
Our study demonstrates that ctDNA detection and quantification using LOB- and LOQ-based cutoffs provide an accurate, clinically implementable approach for monitoring residual disease, recurrence, and response to therapy in CRC patients. CtDNA analysis outperforms traditional markers like CEA and cfDNA and may be readily integrated into clinical workflows to supplement current monitoring strategies.
Acknowledgments: We would like to thank all healthy individuals and colorectal cancer patients for providing their written informed consent to participate in this study. We also thank all study secretaries for their assistance in obtaining study data and patient sample collection.
Conflict of Interest: None
Financial Support: None
Ethics Statement: The study was conducted in accordance with the Declaration of Helsinki, and was approved by the ethics commission of the Bavarian Medical Association (No. 17059; 11.01.2018).