Malnutrition and sarcopenia negatively affect treatment response and clinical outcomes in cancer patients. In gastroenteropancreatic neuroendocrine neoplasms (GEP-NENs), tumor location and hormone secretion may further exacerbate sarcopenia and its consequences. This study investigated the prevalence of malnutrition and sarcopenia in GEP-NEN patients and explored their associations with tumor characteristics, survival outcomes, and the expression of ghrelin system components in tumor tissue. A total of 104 patients were included. Anthropometric measurements, biochemical parameters, and CT scans at diagnosis were analyzed. Tumor expression of key ghrelin system components was assessed in 63 samples.
Nutritional status was comparable across tumors of different origins. Relapsed disease correlated with lower body mass index, and patients presenting with weight loss at diagnosis had significantly shorter overall survival (108 [25–302] vs. 263 [79–136] months). GOAT (ghrelin O-acyltransferase) expression was elevated in these patients. Sarcopenia was highly prevalent (87.2%), and mortality occurred exclusively in patients with sarcopenia. Muscle mass was associated with biochemical markers but showed no correlation with ghrelin system expression. Both nutritional status and expression of certain ghrelin system components are linked to survival in GEP-NEN patients. Regular nutritional assessment and timely interventions are recommended to improve clinical outcomes and quality of life.
Introduction
Malnutrition frequently affects individuals with cancer, resulting not only from the tumor itself but also from treatments, including surgery and chemotherapy. The European Society for Clinical Nutrition and Metabolism (ESPEN) estimates that 10–20% of cancer-related deaths are linked to malnutrition rather than tumor progression, since it can compromise both tolerance to therapy and treatment efficacy [1]. This highlights the need for systematic nutritional screening at the time of diagnosis and during follow-up, enabling timely and appropriate nutritional interventions [2].
Traditional reliance on body mass index (BMI) for nutritional assessment is insufficient, particularly given the rising prevalence of overweight and obesity. Beyond simple body weight, factors such as visceral fat accumulation, sarcopenia, and sarcopenic obesity have been identified as negative prognostic indicators in oncology. Excess adiposity is also associated with an increased risk for multiple types of cancer [3, 4]. Consequently, specific screening tools have been developed to detect malnutrition in cancer patients. Positive screening results should trigger comprehensive assessments to identify sarcopenia and guide targeted nutritional support [1, 5].
Sarcopenia, defined as the loss of skeletal muscle mass, strength, and functional performance, involves alterations in protein metabolism, including increased muscle catabolism and loss of fibers [6]. Its detection requires specialized methods that are not routinely used in clinical practice. Among current options, computed tomography (CT) and magnetic resonance imaging (MRI) are regarded as the most accurate for quantifying muscle mass in cancer patients [7], though their use for routine evaluation remains limited.
Patients with gastroenteropancreatic neuroendocrine neoplasms (GEP-NENs) face additional nutritional challenges due to tumor hormone secretion, which can cause diarrhea, malabsorption, steatorrhea, altered gastrointestinal motility, and weight loss [3]. Despite this, many NENs are slow-growing, treatments are generally well-tolerated, and median survival can reach 41 months [8]. As a result, routine nutritional monitoring is often neglected in this population, and few studies have specifically assessed malnutrition and sarcopenia in NEN patients [9].
The ghrelin system plays a central role in energy balance, appetite regulation, gastric motility, hormonal secretion, and body composition [10–14]. Ghrelin must undergo acylation at its third serine residue, mediated by ghrelin-O-acyl-transferase (GOAT), to become the biologically active form capable of binding the GHSR1a receptor. A truncated receptor, GHSR1b, also exists, though its ligand and function are poorly understood [10, 15, 16]. Ghrelin is expressed widely, particularly in the gastrointestinal tract and endocrine glands, and influences energy homeostasis, gastric acid secretion, insulin release, and turnover of gastrointestinal mucosa [17]. Given these roles, the ghrelin system may modulate cancer-related metabolic disturbances and counteract protein breakdown during cachexia [18–22]. Our previous work has identified ghrelin expression in GEP-NENs and reported associations with tumor progression [23], yet its influence on body composition and nutritional status remains unclear.
This study therefore aimed to investigate nutritional status and the presence of sarcopenia in GEP-NEN patients at diagnosis using a combination of anthropometric, biochemical, and imaging assessments. We also examined potential relationships between nutritional status, sarcopenia, and tumor characteristics, as well as their impact on patient survival. Additionally, we explored associations between sarcopenia and the molecular expression of key ghrelin system components in tumor tissue to enhance the clinical understanding of malnutrition in NENs.
Materials and Methods
Patient selection
This research was conducted according to the Declaration of Helsinki and received approval from the institutional Ethics Committee. All participants provided written informed consent before enrollment. Patients were managed in line with national and international clinical guidelines [24–26].
Data were collected from 104 patients diagnosed with GEP-NENs at a single center between 2001 and 2014. Demographic and clinical characteristics are summarized in Table 1. Tumor tissue samples preserved in formalin-fixed, paraffin-embedded (FFPE) blocks were available for 63 patients for molecular analyses. Patients with hereditary endocrine syndromes were excluded. Detailed clinical information, including prior medical history, was obtained from hospital records.
Table 1. Baseline clinical and biochemical characteristics.
|
Characteristic |
Total (n = 104) |
|
Sex (♂/♀) |
45.2/54.8 |
|
Age at diagnosis (years) |
54.5 (52–58) |
|
Functional tumors |
32.9 (27/82) |
|
Incidental tumor |
38.7 (29/75) |
|
Tobacco exposure |
|
|
No |
31.1 (14/45) |
|
Active |
48.9 (22/45) |
|
Previous exposure |
20 (9/45) |
|
Other neoplasms |
20 (18/90) |
|
Tumor localization |
|
|
Pancreas |
38.5 (40/104) |
|
Stomach |
4.8 (5/104) |
|
Small bowel |
21.2 (22/104) |
|
Hindgut |
34 (35/104) |
|
Other |
2 (2/104) |
|
Nutritional characteristics |
|
|
Weight loss at diagnosis |
39.7 (25/63) |
|
Weight at diagnosis (Kg) |
70 (65– 78) |
|
BMI at diagnosis |
27.2 (24.5–28.7) |
|
Metastasis at diagnosis |
49.1 (51/104) |
|
Liver |
17.4 (8/46) |
|
Spleen |
2.2 (1/46) |
|
Lymph nodes |
50 (23/46) |
|
Peritoneum |
2.2 (2/46) |
|
Multiple invasion |
28.2 (13/46) |
|
Relapsed disease |
25.4 (17/67) |
|
Disease-free |
75.9 (44/58) |
|
Mortality |
34.6 (36/104) |
|
Histologic features |
|
|
Necrosis |
7.3 (9/33) |
|
Multiple tumors |
7.5 (4/53) |
|
Peritumoral invasion |
51.8 (44/85) |
|
Vascular invasion |
28.2 (22/78) |
|
Perineural invasion |
28 (21/75) |
|
Tumor grade |
|
|
Grade 1 |
33.7 (35/104) |
|
Grade 2 |
26.9 (28/104) |
|
Grade 3 |
9.6 (10/104) |
|
Unknown |
29.8% (31/104) |
|
Biochemical analysis at diagnosis |
|
|
Lymphocytes |
1520 (390–2762) |
|
Transferrin (mg/dL) |
240 (199–262) |
|
Ferritin (mg/dL) |
81.7 (5–63) |
|
Albumin (g/dL) |
3.9 (1.6–5.6) |
|
Prealbumin (mg/dL) |
23 (9.7–41.6) |
|
RCP (g/dL) |
2.6 (1.3–5.4) |
|
Total cholesterol (mg/dL) |
165 (30–206) |
|
LDL cholesterol (mg/dL) |
95 (53–124) |
|
HDL cholesterol (mg/dL) |
72 (15–108) |
Legend: Categorical data are presented as percentage and absolute number. Continuous data are presented as median and 95% interquartile range.
CT-based muscle assessment
For the assessment of muscle mass, CT scans performed at diagnosis were utilized. Two consecutive axial slices at the level of the third lumbar vertebra (L3) were selected for each patient, and the cross-sectional area of skeletal muscle (cm²) was measured and averaged. Images were processed on a dedicated workstation (Carestream Vue PACS v12.0.0.0700; Carestream Health, Rochester, NY, USA), which allows tissue segmentation using predefined Hounsfield unit (HU) thresholds. Muscle tissue was distinguished from fat and bone using density cut-offs: +35 HU separated fat from muscle, while +150 HU distinguished muscle from bone [27].
The muscles analyzed included the rectus abdominis, lateral and oblique abdominal muscles, psoas, and paraspinal muscles (quadratus lumborum and erector spinae). Measurements were performed by a trained observer who was blinded to patient outcomes. The cross-sectional area was normalized to the patient’s height squared (m²) and reported as the lumbar skeletal muscle index (SMI, cm²/m²). Sarcopenia was defined using previously established CT-based cut-offs: 38.5 cm²/m² for women and 52.4 cm²/m² for men [28].
RNA extraction and cDNA synthesis
Total RNA was extracted from FFPE tumor specimens (n = 63) using the RNeasy-FFPE Kit (Qiagen, Limburg, The Netherlands) according to the manufacturer’s instructions [23, 29]. RNA quantity and quality were determined with a NanoDrop 2000 spectrophotometer (Thermo Fisher Scientific, Wilmington, NC, USA). Complementary DNA (cDNA) was generated from total RNA using the First-Strand Synthesis kit and random hexamer primers (Thermo Fisher Scientific), as previously described [18, 19, 30–32].
Quantitative real-time PCR (qPCR)
Gene expression analyses were performed using the Brilliant III SYBR-Green Master Mix (Thermo Fisher Scientific) on a Stratagene Mx3000p system. Specific primers were used to measure the mRNA levels (absolute copy number per 50 ng RNA) of ghrelin, In1-ghrelin, GOAT, GHSR1a, and GHSR1b, following validated protocols [33–35]. Expression values were normalized to the 18S rRNA housekeeping gene, selected as the most stable reference after comparison with BACT using GeNorm 3.3 software [36].
Statistical methods
Comparisons between groups were conducted using the Mann–Whitney U test for nonparametric data or the Kruskal–Wallis test for comparisons among more than two groups. Paired analyses used either the Student’s t-test (for normally distributed data) or the Wilcoxon signed-rank test (for nonparametric data). Categorical variables were compared using the chi-squared test. Analyses were performed in SPSS version 20 and GraphPad Prism version 8. Results are reported as median ± interquartile range or percentages. Statistical significance was set at p < 0.05.
Results and Discussion
Cohort characteristics and clinical features
The study included 104 patients, with a slight female predominance (54.8%). Median age at diagnosis was 54 years. The majority of tumors originated from the pancreas (38.5%), and most were grade 1; patients with neuroendocrine carcinoma were excluded. Despite a median BMI of 27.2 kg/m², nearly 40% of patients had experienced weight loss at diagnosis (Table 1).
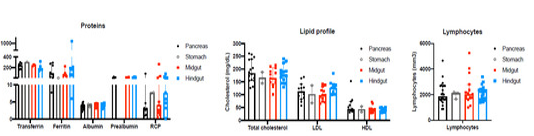
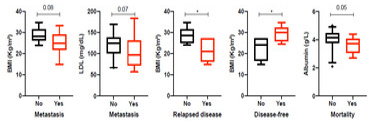
Biochemical assessments—including serum proteins (albumin, transferrin, prealbumin, ferritin, and CRP), lipid profile (total and fractionated cholesterol), and lymphocyte counts—were generally similar across different primary tumor sites (Figure 1a). Notably, patients presenting with metastatic disease at diagnosis (approximately 50%) tended to have lower BMI and reduced serum LDL cholesterol. Similarly, patients with recurrent disease had lower BMI, whereas those in remission had higher BMI values at diagnosis. Lower serum albumin levels were also associated with increased mortality risk in this cohort (Figure 1b).
|
|
|
a) |
|
|
|
b) |
|
Figure 1. (a) Biochemical markers used to evaluate nutritional status in NEN patients, stratified by primary tumor site. (b) Associations between nutritional indicators and clinical outcomes in NEN patients. *p < 0.05. |
At diagnosis, weight loss was observed more frequently in patients with grade 2 tumors, who also showed lower total cholesterol levels and elevated CRP. These differences did not reach statistical significance.
Relationship between nutritional status and survival in NEN patients
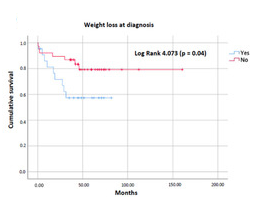
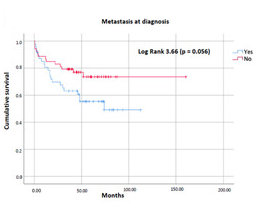
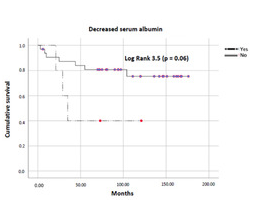
Patients presenting with weight loss at diagnosis exhibited significantly reduced overall survival compared to those without weight loss (median survival: 108 [25–302] months vs. 263 [79–136] months; (Figure 2a). Similarly, the presence of metastases at diagnosis was associated with shorter survival (136 vs. 245 months; p = 0.05; (Figure 2b)). Patients with low serum albumin levels at diagnosis also tended to have worse survival outcomes compared to those with normal albumin (65 vs. 142 months; p = 0.06; (Figure 2c)).
Other nutritional indicators—including BMI, transferrin, ferritin, lymphocyte counts, CRP, and cholesterol—did not show a significant association with overall survival in this cohort.
|
|
|
|
a) |
b) |
|
|
|
|
c) |
|
|
Figure 2. Cumulative survival curves for NEN patients according to the presence of nutrition-related parameters at diagnosis: (a) weight loss; (b) metastasis; (c) decreased serum albumin levels. |
|
Ghrelin system expression and its association with nutritional features in NEN patients
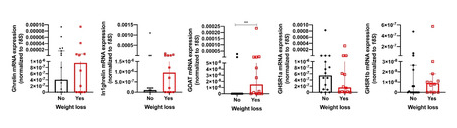
Given that weight loss and low serum albumin were the most clinically relevant markers linked to survival in NEN patients, we next investigated their relationship with the expression of ghrelin system components in tumor samples from 63 patients. Notably, patients who exhibited weight loss at diagnosis showed a significant upregulation of the GOAT enzyme (Figure 3a). Other components of the ghrelin system, such as the ghrelin hormone itself and the splice variants In1-ghrelin and GHSR1b, were also elevated, although these increases did not reach statistical significance.
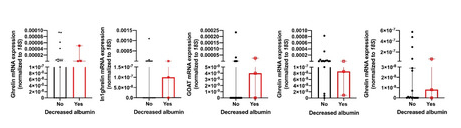
In contrast, no significant correlations were detected between decreased serum albumin levels and the expression of any ghrelin system components (Figure 3b).
|
|
|
|
a) |
|
|
|
|
|
b) |
|
|
|
|
|
c) |
d) |
|
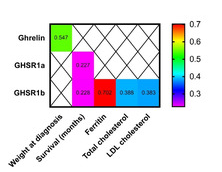
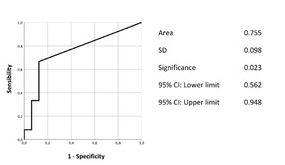
Figure 3. Analysis of ghrelin system components in tumor samples from NEN patients: (a) stratified by presence of weight loss; (b) stratified by low serum albumin; (c) correlations between mRNA levels of ghrelin-related genes and nutritional indicators; (d) ROC curve assessing GOAT enzyme as a marker for identifying patients with weight loss (**p < 0.01). |
|
Analysis revealed that ghrelin levels were linked to patients’ body weight at the time of diagnosis. The receptors, both canonical (GHSR1a) and truncated (GHSR1b), showed associations with overall survival duration. In particular, GHSR1b also correlated with nutritional biomarkers such as ferritin, total cholesterol, and LDL cholesterol (Figure 3c). Comparing all ghrelin system components via ROC analysis, GOAT enzyme emerged as the most reliable predictor of weight loss, showing an AUC of 0.755 (Figure 3d).
Sarcopenia is highly prevalent in NEN patients at diagnosis
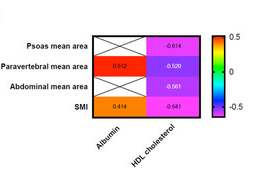
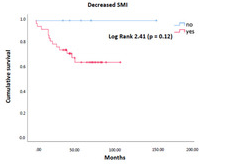
Using CT imaging, sarcopenia was identified in 87.2% of patients at the time of diagnosis. Muscle areas in the paravertebral, abdominal, and psoas regions, as well as overall SMI, were significantly associated with serum nutritional markers (Figure 4a). However, no specific relationship was observed between these muscle measurements and clinical outcomes. Interestingly, deaths occurred only in patients without sarcopenia, though this trend was not statistically significant (Figure 4b).
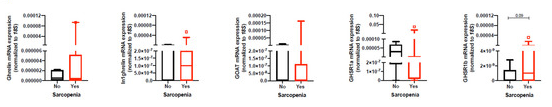
Furthermore, expression of ghrelin system genes did not differ significantly between patients with or without sarcopenia as defined by SMI (Figure 4c). Reduced SMI was more frequent in patients with grade 2 tumors, while no connection with the primary tumor location was detected in this cohort.
|
|
|
|
a) |
b) |
|
|
|
|
c) |
|
|
Figure 4. (a) Correlations between CT-derived muscle parameters, including SMI, and clinical/biochemical nutritional markers. (b) Kaplan-Meier survival curves for NEN patients based on sarcopenia status at diagnosis. (c) Expression levels of ghrelin system components in tumor samples according to sarcopenia presence at diagnosis. |
|
This study aimed to comprehensively assess the nutritional status of patients with GEP-NENs at the time of diagnosis using a combination of epidemiological, anthropometric, biochemical, and imaging approaches, and to explore potential associations with the molecular expression of key ghrelin system components. Although a few studies have addressed nutritional aspects in NENs [37, 38], this is, to our knowledge, the first investigation combining CT-based evaluation of sarcopenia with a detailed molecular analysis in a representative cohort of 104 well-differentiated GEP-NEN patients. In addition, we examined the prognostic relevance of nutritional status over a follow-up period of 7–20 years. While prior reports have documented the presence of ghrelin system elements in NENs [20, 23, 39–41], their direct association with nutritional markers had not been specifically explored before.
Our findings indicate that weight loss at diagnosis is a predictor of poorer survival outcomes in NEN patients. Sarcopenia was highly prevalent, affecting 87% of the cohort, highlighting the utility of CT imaging for early detection. Moreover, components of the ghrelin system, particularly the GOAT enzyme, exhibited expression patterns associated with nutritional status, suggesting a potential mechanistic link.
Albumin and prealbumin, recognized by the American Society for Parenteral and Enteral Nutrition as indicators associated with adverse outcomes, should not, however, be solely relied upon to diagnose protein-energy malnutrition [42]. In line with this, we observed a trend for serum albumin to correlate with survival in our cohort, supporting the notion that measuring visceral protein levels alone is insufficient to evaluate malnutrition in cancer patients. Additionally, albumin levels were positively correlated with CT-derived muscle area and SMI, consistent with previous studies [43], reinforcing the importance of integrating multiple nutritional assessment methods.
Weight loss remains a key criterion for diagnosing malnutrition and has been consistently linked to higher mortality in solid tumors, independent of age, race, or tumor stage [44–47]. Our results confirm decreased survival in NEN patients who experienced weight loss at diagnosis. This aligns with prior observational work, including a study of 203 NEN patients, which reported that malnourished patients—identified using a combination of screening tools, anthropometrics, and biochemical markers—had longer hospital stays and reduced overall survival [48].
Despite its recognized prevalence in cancer populations, malnutrition in NEN patients remains under-characterized, particularly in relation to survival and prognosis [37]. Recent evidence suggests that 21–25% of NEN patients may exhibit malnutrition [48, 49], emphasizing the need for systematic nutritional screening at diagnosis [9]. Current clinical guidelines also highlight the importance of evaluating muscle mass loss alongside BMI, weight loss, food intake, and inflammatory markers for accurate malnutrition diagnosis [44]. Low skeletal muscle mass, used to define sarcopenia, provides clinicians with a practical and rapid tool for treatment decision-making, as BMI alone does not reveal sarcopenia or myosteatosis [50, 51].
In this context, CT-based evaluation of sarcopenia represents a gold standard for assessing body composition in cancer patients [7]. Since most patients undergo abdominal imaging, paravertebral muscle assessment can be performed routinely at diagnosis and during follow-up. A recent study in 49 metastatic NEN patients undergoing peptide receptor radionuclide therapy reported 67% prevalence of sarcopenia and 71% prevalence of myosteatosis; progression-free survival was not significantly different between sarcopenic and non-sarcopenic patients, and 12% died during follow-up [37]. In contrast, our cohort demonstrated higher sarcopenia prevalence (87%) and a higher mortality rate. Notably, we did not specifically analyze treatment effects.
Similarly, a retrospective study of gastric NENs reported sarcopenia prevalence of 42.8%, with higher incidence among older male patients, those with BMI <25 kg/m², and tumors >50 mm [38]. Sarcopenia in this study did not correlate with short-term clinical outcomes but predicted long-term complications in patients with mixed adenoneuroendocrine carcinoma. Differences from our results may be attributed to the limited number of well-differentiated gastric NENs, absence of post-surgical complication analysis, and a largely male Asian population (only 23.9% female).
Based on our findings, it is advisable that all patients with NENs undergo systematic nutritional screening both at diagnosis and during follow-up, similar to recommendations for other cancers [1]. Nutritional guidance, including individualized caloric and protein intake, should be provided, and oral nutritional supplementation should be initiated promptly in patients identified as malnourished or at risk of malnutrition [1, 52].
Ghrelin, an orexigenic hormone primarily secreted by gastrointestinal tissues, plays a central role in signaling hunger to the central nervous system [53]. Beyond stimulating appetite, ghrelin can influence body weight and composition by enhancing growth hormone release, gastric acid secretion, and overall anabolic processes. Additionally, it can mitigate muscle catabolism, improve gastrointestinal motility, and modulate metabolic pathways [13, 54, 55]. These pleiotropic actions suggest that ghrelin may counteract the cachexia cycle through its combined anabolic, orexigenic, and anti-inflammatory effects [13]. Evidence increasingly indicates that the ghrelin system may participate in cancer progression, particularly influencing tumor proliferation and metastatic behavior [17]. Expression of ghrelin, its canonical receptor GHSR1a, and the truncated receptor GHSR1b has been documented in multiple cancer types, including renal cell carcinoma and various neuroendocrine tumors, using techniques such as immunohistochemistry and RT-PCR [41, 56, 57]. Some studies have also reported associations between ghrelin system expression, tumor progression, and patient survival in cancers including renal carcinoma and GEP-NENs [23, 57, 58]. Mechanistically, ghrelin may enhance cancer cell migration and invasion via the GHSR/PI3K/Akt signaling pathway, although its role in breast and prostate cancers remains controversial [17, 59, 60].
Within the context of NENs, previous studies—including ours—have suggested that the ghrelin system contributes to tumor biology and pathophysiology [11, 12, 23, 39]. However, investigations specifically linking ghrelin system components to nutritional status in NEN patients have been lacking. In prior work, we reported notable overexpression of the GOAT enzyme in GEP-NEN tumors, correlating with increased tumor size [23]. In the present study, we observed elevated GOAT expression in patients exhibiting weight loss at diagnosis, a clinical feature associated with decreased survival. Interestingly, no significant differences were found in ghrelin system expression between sarcopenic and non-sarcopenic patients as defined by CT imaging, which may be partially attributable to the limited sample size.
This study has several limitations. It is retrospective, and specific nutritional anthropometric assessments recommended in current guidelines were not performed [61]; for example, bioimpedance data were not available. The relatively small cohort size also precluded analysis of the impact of individual therapeutic regimens, and circulating levels of ghrelin components were not measured. Nevertheless, the study has notable strengths, including a well-characterized cohort of well-differentiated GEP-NENs with balanced gender representation and sarcopenia assessment using CT scans, the gold standard for body composition evaluation in cancer patients [7]. Furthermore, patients were followed longitudinally over extended periods, providing valuable survival and clinical outcome data.
Conclusion
In conclusion, this study provides a detailed assessment of nutritional status and CT-based sarcopenia in GEP-NEN patients at diagnosis, and it examines their relationship with survival and the molecular expression of key ghrelin system components. The findings underscore the high prevalence of sarcopenia in this population, supporting the implementation of early nutritional screening and intervention to identify patients at risk of adverse outcomes and to guide therapeutic strategies aimed at improving nutritional status, quality of life, and clinical prognosis. Future prospective studies with larger cohorts are warranted to validate these results, and measurement of circulating ghrelin system components—particularly GOAT—may offer additional prognostic insights and potential therapeutic targets in GEP-NENs.
Acknowledgments: None
Conflict of Interest: None
Financial Support: This work was funded by Instituto de Salud Carlos III: JR19/00050), Junta de Andalucía (PI-0038-2019, BIO-0139). GETNE Junior Grant 2019. Young Investigator’s Grant SEEN 2020. SANCYD Research Grant 2021. Ministerio de Ciencia e Innovación (PID2019-105564RB-I00), and CIBERobn. PID2019-105201RB-100; GETNE2019 Research Grant. Additionally, Nestle Healthcare and Nutricia have kindly contributed with the funding of this study. The funders were not involved in the study design, collection, analysis, interpretation of data, the writing of the manuscript or the decision to submit it for publication. CIBER is an initiative of Instituto de Salud Carlos III, Ministerio de Sanidad, Servicios Sociales e Igualdad, Spain.