Many breast cancer survivors (BCS) continue to face lasting side effects, among which breast cancer–related lymphedema (BCRL) is especially frequent. Exercise is generally recognized as a safe approach to support recovery and enhance daily functioning in BCS, either living with or susceptible to BCRL. Yet, the influence of combined aerobic and resistance (concurrent) training in this group is not well established. This investigation assessed the impact of a 12-week guided concurrent exercise regimen followed by another 12-week period without training on molecular, physical, and clinical indicators in BCS. Eleven participants with or at risk for BCRL completed a single-group study assessing changes after the 12-week program and again after the follow-up period. The parameters examined included molecular (92 inflammation-associated proteins), functional (upper- and lower-body strength, grip force, and aerobic capacity), and clinical measures (body mass index, arm size, tissue and muscle thickness, joint range of motion, habitual activity, heart rate variability, pain, and quality of life [QoL]). Following the exercise intervention, upper-body and grip strength, pain perception, emotional state, and overall QoL improved significantly. At the end of the follow-up, the gain in rowing strength persisted, and several inflammatory proteins declined notably. Twelve weeks of concurrent training enhanced muscular strength, reduced pain, and improved QoL in BCS without provoking inflammation. During the follow-up, strength benefits were maintained and inflammatory protein levels fell, emphasizing the promise of this training type. Broader and controlled research is warranted to confirm these findings.
Introduction
Breast cancer (BC) ranks as the world’s second most common malignancy, with about 2.3 million new diagnoses each year [1]; by 2040, projections suggest this number could reach 3 million [2]. While survivorship rates have risen, post-treatment complications remain poorly characterized [3]. Nearly 90% of survivors endure chronic outcomes—ranging from physical and emotional limitations to social and functional constraints—that adversely affect quality of life (QoL). Commonly reported problems include pain, breast cancer–related lymphedema (BCRL), loss of muscular power, lowered cardiorespiratory fitness (CRF), and limited range of motion (ROM) [4, 5]. In particular, upper-limb strength values are generally below those of healthy individuals [5]. Moreover, chemotherapy-related cardiotoxicity is frequent, further diminishing both survival and QoL [6].
BCRL remains one of the most troublesome complications, resulting from lymphatic impairment that leads to localized fluid accumulation [7]. While axillary lymph node dissection (ALND) is considered the chief risk factor, sentinel lymph node biopsy (SLNB) and radiation therapy can also contribute [8, 9]. The estimated five-year cumulative incidence stands at 30.1% for ALND combined with regional radiotherapy, 24.9% for isolated ALND, 10.7% for SLNB plus nodal radiotherapy, and 8.0% for SLNB alone [10]. Additional risks include body mass index (BMI) ≥ 30 kg/m² at diagnosis, postoperative cellulitis, and higher relative volume change [11]. The disorder compromises QoL through arm swelling, adipose thickening of subcutaneous tissue, and persistent inflammation [7]. Chronic inflammatory activity in BCS may further influence recurrence and survival outcomes, with raised C-reactive protein (CRP) and serum amyloid A levels linked to poorer prognosis [12].
Comprehensive follow-up care for BC survivors should target both symptom reduction and overall cardiometabolic improvement [13]. Aerobic and resistance exercise are widely endorsed as safe, evidence-based strategies for this population [14, 15]. Recent reviews highlight that mixed (concurrent) programs enhance muscular and aerobic capacity while also modulating inflammatory responses [16]. Because concurrent protocols integrate both exercise modes within the same session, they may produce broader physiological advantages [17, 18]. Investigating such combined routines could clarify their clinical and functional relevance for QoL enhancement in survivors. Furthermore, meta-analyses indicate that structured exercise can lower circulating concentrations of insulin-like growth factor 1 (IGF-1), interleukins IL-6 and IL-10, tumor necrosis factor-alpha (TNF-α), and CRP in both BC patients and survivors [19, 20]. A notable dose–response association was reported for interventions lasting over 11 weeks and reductions in IL-6 [21]. In addition, prior work showed that a single resistance exercise session, irrespective of intensity, does not raise pro-inflammatory cytokine levels in women with BCRL [22].
Nevertheless, the prolonged effects of exercise on inflammatory profiles in this cohort remain uncertain. Earlier investigations largely employed progressive or isolated resistance protocols [23, 24], often omitting aerobic components. At present, lymphedema-specific exercise guidelines for cancer survivors mostly emphasize resistance training, with little attention to combined formats [15].
Hence, the present single-group study primarily sought to assess how concurrent training influences upper- and lower-limb strength and inflammation-related proteins in BCS who have or are at risk of BCRL. Additional analyses explored its effects on handgrip strength, CRF, BMI, limb volume, tissue composition, ROM, activity levels, heart rate variability (HRV), as well as self-reported pain, function, and QoL after both the 12-week training and 12-week follow-up periods.
Materials and Methods
Study design
This pilot investigation employed a single-group quasi-experimental format and was carried out at the Miguel de Cervantes European University (Valladolid, Spain) between March and October 2024. The research included a 12-week supervised combined exercise plan and a 12-week observation period without physical training. Evaluations of molecular, clinical, functional, and self-reported variables were conducted one week prior to the intervention (baseline), immediately after the 12-week training (post-intervention), and one week following the non-training follow-up phase (follow-up).
All procedures were performed according to the Declaration of Helsinki and good clinical practice guidelines. Ethical approval was issued by the Valladolid East Health Area Drug Research Ethics Committee on 23 November 2023 (code PI 23-3382). Every participant provided signed informed consent before entering the study.
Study Participants
From 20 December 2023 to 5 March 2024, 80 breast cancer survivors (BCS), either diagnosed with breast cancer-related lymphedema (BCRL) or at risk of developing it, were invited to join the project. Ultimately, 12 women agreed to participate and fulfilled the eligibility requirements:
(a) female BCS aged 18–65 years, who had completed chemotherapy, radiotherapy, or surgery at least six months earlier, and
(b) diagnosed with unilateral BCRL stage I or II as defined by the International Society of Lymphology (ISL) [25], or considered at risk (following radical or modified radical mastectomy, breast surgery with ALND or SLNB, or axillary radiotherapy).
Exclusion criteria included: (a) any recent surgical procedure (<3 months) or one planned during the study, (b) cognitive limitations, or (c) medical disorders preventing physical activity.
A total of 11 participants completed the baseline, post-intervention, and follow-up assessments for clinical, functional, and questionnaire-based outcomes. For molecular outcomes, data from one participant were unavailable across all points and thus excluded from the analysis (Figure 1).
|
|
|
Figure 1. Participant recruitment and retention across the study. |
Exercise training protocol and compression bandage use
Participants engaged in a 12-week structured concurrent training program followed by a 12-week non-exercise phase. Before starting, there was a one-week familiarization session where initial loads were personalized. Training consisted of two 60-minute supervised sessions weekly, performed individually or in pairs, each under direct 1:1 supervision.
Every session began with a 10-minute warm-up, including mobility work (shoulder girdle, hip, knee, and ankle) and basic strength movements (10 repetitions of squats and front/lateral raises with a light elastic band).
Strength training used elastic bands available in seven intensities (5, 15, 20, 25, 30, 35, and 40 kg), arranged in a circuit of seven exercises covering the main muscle groups:
Unilateral standing row
Unilateral standing chest press
Pallof press
Squat
Single-leg deadlift
Unilateral front raise
Step-up
Each person completed two rounds of 8–12 repetitions per exercise, working at moderate to high effort (EC, calculated as the ratio of completed to potential repetitions [26]). Participants rested for two minutes between circuit rounds, while inter-exercise rest was only the time required to switch stations.
During the first training session, participants performed two initial sets to failure to determine strength capacity and set the starting resistance. Loads were adjusted accordingly. Every three weeks, training load was rechecked using a Chronojump Force Sensor Kit and Chronojump 2.3.0 software (Chronojump Boscosystems®, Barcelona, Spain) to measure the mechanical output for each repetition. When participants achieved 17–20 repetitions, resistance was increased by one level, and 10 repetitions were then completed at that higher tension. If 16 or fewer repetitions were achieved, future sets were reduced to 80% of that number with no load change.
After strength work, participants performed aerobic cycling using a Bodytone Active Bike 200 (Bodytone International Sport S.L., Murcia, Spain) at 70–75% of their predicted maximum heart rate (220- age) [27]. Heart rate was continuously tracked with a Polar H10 chest strap and Polar software (version 3.5.8, Polar Electro Oy, Kempele, Finland). The aerobic phase began at 15 minutes and increased by 5 minutes every two weeks, reaching 30 minutes at maximum [27].
After each session, perceived exertion (RPE) was recorded using the Borg CR-10 scale [28]. Participants could choose whether or not to wear compression garments during training and were encouraged to maintain their normal daily activities throughout.
The entire exercise approach followed the CORE-CERT reporting framework to ensure a comprehensive description of exercise interventions in breast cancer management [29].
Compression bandage application
Participants diagnosed with BCRL had a cohesive compression wrap placed on the affected arm following each exercise session. For those merely at risk of BCRL, the wrap was omitted for comfort-related reasons. Individuals were advised to remove the bandage two hours after it was applied [30].
The process began with an elastic tubular cotton layer (Liderton®; sizes 5 and 6) placed directly on the skin. Over this, an elastic cotton strip (NOBAFIX®; 4 cm × 4 m) was wrapped around the fingers and the back of the hand. The final layer consisted of a cohesive compression band (Cinfa Farmalastic®, 5 cm × 4.5 m for the hand and wrist; 10 cm × 4.5 m for the arm), applied from the hand upward to the upper arm. A cotton insert was positioned in the antecubital region to enhance comfort. Wrapping was performed with an overlap of 50% at the most distal section and 25% from the elbow upward, ensuring gradual pressure reduction from distal to proximal areas [31].
Outcome evaluation
The main study variables included functional measures (upper- and lower-limb strength) and molecular indicators (inflammatory proteins). Additionally, secondary clinical, functional, and questionnaire-based outcomes were assessed. Data were gathered at baseline, after the 12-week concurrent training period, and after the 12-week non-training phase.
Training compliance was determined by the percentage and number of attended sessions for each subject.
Primary outcomes
Functional measures
Upper- and lower-body strength
To determine the maximal voluntary isometric contraction (MVIC), both upper- and lower-limb strength were evaluated using a Chronojump Force Sensor Kit (Chronojump Boscosystems®, Barcelona, Spain) connected to the Chronojump 2.3.0 software for Windows. The force signal was amplified to 80 Hz via a dedicated amplifier.
For the upper body, MVIC was assessed through the unilateral standing chest press and unilateral row.
During the chest press, participants stood with feet parallel and comfortably apart, maintaining the shoulder at 45° abduction and the elbow flexed to 90°, holding a neutral horizontal position.
For the row assessment, subjects stood with neutral shoulders and elbows bent at 90°.
In both exercises, a handle attached to a chain was connected to the force transducer, mounted on a height-adjustable bar. The right arm was always tested before the left.
The lower-limb MVIC was measured through an isometric squat. Each participant was linked to the platform with an adjustable cable to accommodate individual height. From a standardized 90° hip and knee flexion, participants executed maximal isometric effort as quickly as possible and held it for five seconds. Verbal encouragement was provided to ensure maximal intensity.
Each subject performed three maximal trials lasting at least five seconds, separated by two-minute rests. Peak force values from all attempts were recorded, and the average of three repetitions was used for subsequent analysis.
Molecular measures
Inflammatory protein analysis
Blood samples were obtained via venipuncture of a forearm vein by an experienced nurse. The samples were drawn into EDTA-coated Vacutainer tubes, followed by centrifugation at 1500× g for 10 minutes. The plasma layer was separated and re-centrifuged at 2500× g for 15 minutes. Twenty microliters (20 µL) of plasma were stored in cryovials at −80 °C.
At the time of measurement, 20 µL of each plasma sample was shipped on dry ice to the Cobiomic laboratory, Olink® Proteomics (Córdoba, Spain). There, 1 µL of each sample was analyzed using the Olink® Target 96 Inflammation panel [Cobiomic Bioscience S.L.; https://olink.com/products/olink-target-96
(accessed 7 June 2025)] and the Proximity Extension Assay (PEA) method [32].
The PEA technique employs antibody pairs tagged with short DNA oligonucleotides that interact upon binding, generating a signal proportional to protein presence. Results were expressed as Normalized Protein Expression (NPX) on a log₂ scale, where higher NPX denotes greater expression.
Each target protein included a lower limit of detection (LOD) established by negative controls within each assay [33]. Only those proteins with NPX values above the LOD in at least 75% of all samples were included in the statistical analyses.
Secondary outcomes
Clinical outcomes
Body mass index (BMI)
Participant height and body weight were determined using a stadiometer together with a Tanita BC-545N digital scale (Tanita, Tokyo, Japan). Measurements were taken without footwear and while participants wore light indoor clothing. BMI was subsequently computed as weight (kg) divided by squared height (m²).
Arm volume
The circumference of both arms—the limb with lymphedema and the contralateral one—was obtained using a 1 cm flexible tape (Orliman, Valencia, Spain). Each person lay on their back with the shoulders abducted at 45° and the palms turned upward. Measurements began at the metacarpophalangeal joints and were recorded at 10, 20, 30, 40, and 50 cm intervals, ending just below the axilla. All circumference readings were converted into volumetric data by applying the truncated cone (frustum) formula [34]. The total arm volume of both sides and the interlimb difference (mL) were included for later analyses.
Tissue thickness
The muscle and subcutaneous layers of the affected arm were assessed with a Samsung HS30 ultrasound scanner (Samsung Healthcare Global, Gangwon, Republic of Korea) using a 40 mm linear transducer (3–12 MHz).
In short, scans were taken 10 cm below and 10 cm above the elbow crease. The probe was positioned perpendicularly to the anterior surface of the upper arm, and ample gel was applied to minimize compression artifacts [35].
Muscle depth was defined as the distance between anterior and posterior fascial boundaries, whereas subcutaneous depth corresponded to the space from skin to fascia. Three readings were collected at each site, and the average values were used for subsequent statistics.
Range of motion (ROM)
Shoulder flexion and abduction were evaluated in both arms using a manual goniometer while participants remained supine. Each motion was tested three times, and the mean value represented the final result.
Physical activity level
Activity behavior was objectively tracked using an ActiGraph GT3X+ accelerometer (ActiGraph, Pensacola, FL, USA) [36]. Devices were worn on an elastic belt over the right hip during waking hours for seven consecutive days, excluding water activities. Assessments were conducted at baseline, after training, and after follow-up.
Participants received verbal and written guidelines plus a wear-time diary to promote compliance. Non-wear time was identified using the Choi algorithm [37] (window 90 min, stream frame 30 min, spike tolerance 2 min). Only data with ≥10 h/day of wear time for ≥5 days were analyzed.
Raw data were processed with ActiLife v6.13.4 software (ActiGraph, Pensacola, FL, USA), applying Freedson adult thresholds [38] in 60-second epochs to classify activity intensity:
Sedentary: <100 counts·min⁻¹
Light: 100–1951 counts·min⁻¹
Moderate–to–vigorous (MVPA): ≥1952 counts·min⁻¹
The total MVPA duration was used for analysis.
Heart rate variability (HRV)
HRV recordings were obtained via a Polar H10 chest strap sensor (Polar Electro Oy, Kempele, Finland) synchronized with the Elite HRV© application (Elite HRV Inc., Asheville, NC, USA). Each subject rested supine for 15 minutes in a dimly lit, quiet room maintained at 20–22 °C. The central five minutes of data were extracted for evaluation.
Artifact correction and HRV computation were performed using Kubios HRV Scientific Little® software (v4.1.1; Kubios Ltd., Kuopio, Finland), with a low threshold for beat correction. Time-domain indicators—Mean RR interval, SDNN, and RMSSD—and frequency-domain metrics—LF (0.04–0.15 Hz) and HF (0.15–0.4 Hz)—were analyzed [39].
Functional Outcomes
Cardiorespiratory fitness (CRF)
CRF was evaluated through a progressive cycling test using a Wattbike AtomX ergometer (Wattbike, UK). To ensure safety, blood pressure was checked before and after testing with an Omron M7 automated sphygmomanometer (HEM-780, Omron, Kyoto, Japan) while participants sat in the test start position.
The test began with a 2-minute seated rest, followed by a graded load protocol starting at 50 W, increasing by 25 W every 2 minutes [40], until voluntary exhaustion or 90% ± 10% of the predicted maximal heart rate. A 2-minute cooldown phase without resistance concluded the session.
Heart rate and respiratory exchange were continuously recorded. Gas analysis was performed with the MetaLyzer 3B metabolic system (Cortex Biophysik GmbH, Leipzig, Germany), which was calibrated daily as per manufacturer guidance.
Peak oxygen uptake (VO₂peak), representing cardiorespiratory capacity, was expressed per kilogram of body mass (mL·min⁻¹·kg⁻¹).
Handgrip strength
Grip strength assessment was carried out using a JAMAR® Plus Smart Digital Hand Dynamometer (Patterson Medical Ltd., Sammons Preston, Nottinghamshire, UK). Participants were seated upright with their forearms resting on a table, holding the dynamometer while keeping their shoulders neutral and the elbow bent at 90°. Each subject performed three maximal squeezes, lasting 3–5 seconds each, with a 3-minute recovery between trials [41]. Testing was conducted first on the affected arm, followed by the unaffected arm, and the average of the three readings was used for analysis.
Self-Reported Questionnaires
Pain
Pain intensity was evaluated using a Numeric Rating Scale (NRS) ranging from 0 to 10 [42], where 0 denoted “no pain” and 10 indicated “the worst pain imaginable.” Participants rated the resting pain in their affected limb accordingly.
Quality of life
Health-related quality of life (QoL) was determined using the Functional Assessment of Cancer Therapy–Breast (FACT-B+4) questionnaire [43]. This tool includes 41 items grouped into six categories: physical, functional, emotional, and social/family well-being, as well as breast cancer–specific and arm-related subscales. Both total FACT-B and FACT-B+4 composite scores were computed. Responses were rated from 0 (not at all) to 4 (very much), where higher totals reflected fewer symptoms and better overall well-being.
Upper-Body Function
The 30-item Disabilities of the Arm, Shoulder, and Hand (DASH) questionnaire [44] was utilized to assess functional performance of the upper limbs. The DASH measures mobility limitations and symptoms related to musculoskeletal conditions. Higher scores denote greater impairment in upper-limb function.
Statistical analysis
All statistical computations were performed with SPSS Statistics v23.0 (IBM, Chicago, IL, USA), Stata 14 (StataCorp, College Station, TX, USA), R v4.4.2 (Pile of Leaves), and RStudio Desktop v2024.12.0-467 (Posit Software, PBC, Boston, MA, USA). Graphs were generated using GraphPad Prism v8.0.1.
Descriptive statistics summarized baseline demographic and clinical features for all participants who completed the initial assessment. Continuous variables were presented as mean ± SD and median with interquartile range (Q1–Q3), while categorical variables were expressed as percentages. The Shapiro–Wilk test was used to examine data normality.
A one-way repeated-measures ANOVA was used to determine time effects (baseline, post-training, and follow-up) on normally distributed primary and secondary variables, and to test load progression over weeks 1, 4, 7, and 10. When a significant effect was detected, Bonferroni-adjusted post hoc tests were conducted to control for Type I error. For data deviating from normality, the Friedman test was applied, followed by Wilcoxon signed-rank post hoc tests if significant time differences appeared.
Effect size (ES) was expressed as partial eta squared (η²p) for ANOVA and Kendall’s W for Friedman analyses. The magnitude of change between measurements was quantified as follows:
For normally distributed data: Cohen’s d (mean change divided by pooled SD) with 95% confidence intervals (CIs).
For non-normal data: rank biserial correlation (r) with 95% CI, where r = Z / √N (Z = Wilcoxon statistic, N = total observations).
Pearson’s correlation tests explored the relationships between percentage changes (%Δ) in molecular, functional, clinical, and self-reported outcomes that showed significant differences. These were calculated as:
|
%Δ = ((post-intervention − baseline) / baseline) × 100 for post-intervention effects |
(1) |
|
%Δ = ((follow-up − baseline) / baseline) × 100 for follow-up effects |
(2) |
All outcomes were reported with corresponding p-values. Significance thresholds were set at p < 0.05 for clinical, functional, and questionnaire variables, while p < 0.001 was applied to molecular results because of the large number of protein comparisons (n = 74). Given the pilot nature of the study and limited sample size, no further corrections for multiple testing were implemented.
Fold change in protein expression was computed as the mean NPX difference (log₂ scale) between time points (baseline, post-training, follow-up). Significance (p < 0.001) was tested using paired t-tests for normally distributed data and Wilcoxon signed-rank tests otherwise.
No a priori power analysis was conducted, consistent with pilot study methodology. Literature indicates that ~12 participants are appropriate when prior variance data are unavailable [45]. This investigation initially enrolled 12 participants, with 11 completing all evaluations.
A post hoc power assessment was performed using two complementary methods:
G*Power v3.1.9.7 (α = 0.05), converting η²p to Cohen’s f via the formula f=η2p/(1-η2p)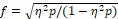 [46];
Kendall’s W from Friedman tests, applying the noncentral chi-squared approximation (χ² = W × n × (k − 1)) [47], where n is the number of participants and k the number of time points. Power estimation was completed in RStudio (α = 0.05).
Results and Discussion
Participant profile
All individuals enrolled in the study were women previously diagnosed with either invasive ductal carcinoma (81.82%) or invasive lobular carcinoma (18.18%). Each participant had undergone both breast and axillary surgery, with an average of 11 lymph nodes excised (Table 1).
Table 1. Baseline characteristics of participants.
|
Variable |
Mean ± SD / n (%) |
|
Age (years) |
53.00 ± 7.17 |
|
Body weight (kg) |
65.65 ± 12.59 |
|
Stature (m) |
1.61 ± 0.06 |
|
Body Mass Index (kg·m⁻²) |
25.42 ± 4.31 |
|
Duration since cancer diagnosis (years) |
6.83 ± 4.56 |
|
Side of affected limb |
|
|
Right arm |
5 (45.45) |
|
Left arm |
6 (54.55) |
|
Breast surgical procedure |
|
|
Any breast surgery |
11 (100) |
|
Lumpectomy / Tumorectomy |
5 (45.45) |
|
Tumorectomy with simple mastectomy |
1 (9.09) |
|
Radical mastectomy |
3 (27.27) |
|
Modified radical mastectomy |
2 (18.18) |
|
Axillary intervention |
|
|
Any axillary surgery |
11 (100) |
|
Sentinel lymph node biopsy (SLNB) |
2 (18.18) |
|
Axillary lymph node dissection (ALND) |
8 (72.73) |
|
Combined SLNB + ALND |
1 (9.09) |
Abbreviations: ALND = axillary lymph node dissection; BMI = body mass index; SD = standard deviation; SLNB = sentinel lymph node biopsy.
Most participants had a treatment history that included radiotherapy (81.82%), chemotherapy (81.82%), and current or past hormonal therapy (90.91%). Six individuals had a clinical diagnosis of breast cancer–related lymphedema (BCRL), at stage I (18.18%) or stage II (36.36%), and had finished the intensive phase of complex decongestive therapy (CDT). Four of these participants opted to continue wearing compression garments during exercise. There were no recorded alterations in their self-management of BCRL during the intervention. The average age of participants was 53.00 ± 7.20 years, and the mean baseline BMI was 25.42 ± 4.31 kg·m⁻².
Exercise adherence and tolerance
Overall compliance with the training program was 92.05%, corresponding to 22 ± 3 out of a possible 24 sessions completed. No negative events, symptom aggravations, or new cases of BCRL occurred during the intervention. Perceived exertion scores averaged 6.26 ± 0.28 on the Borg CR-10 scale [26, 48], confirming a moderate exercise intensity. The aerobic section of the sessions represented 72.18 ± 1.01% of each participant’s estimated maximum heart rate.
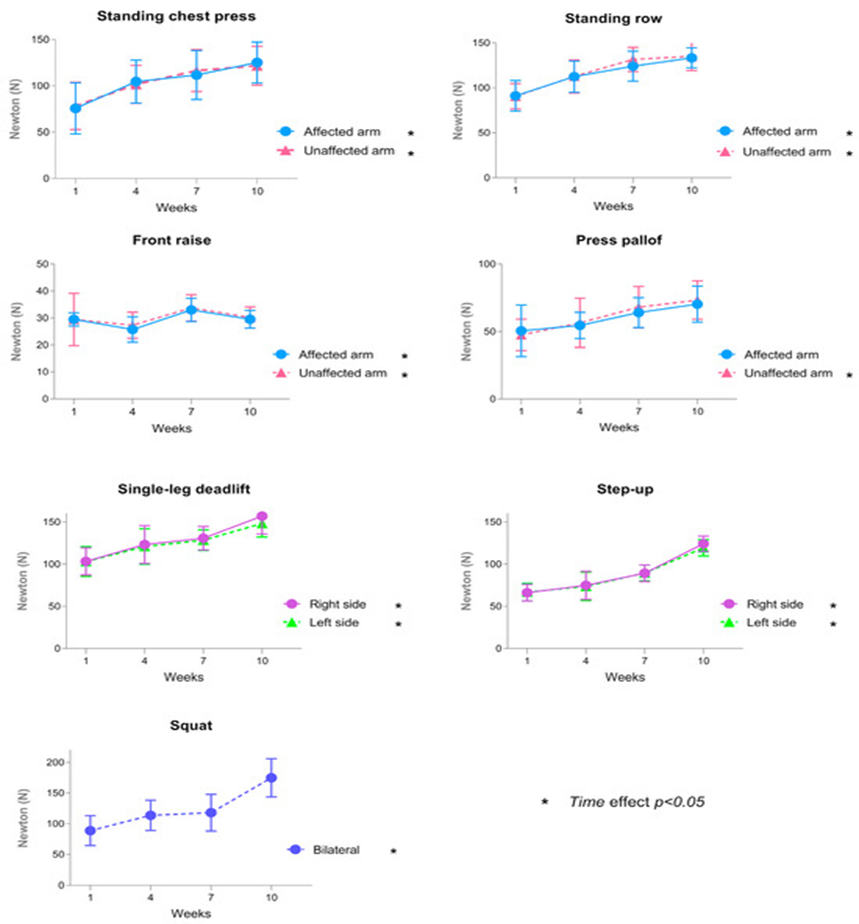
Resistance load adjustments were continuously evaluated using a force sensor every three weeks. Progression was achieved by modifying the elastic band resistance and/or the number of repetitions. Figure 2 shows the upward trend in force output (in newtons) across the 12-week period. A significant time-related improvement (p < 0.05) in load intensity was observed across all movements, excluding the Pallof press performed with the affected limb.
|
|
|
Figure 2. Load progression during 12 weeks of resistance training, measured with a force sensor at weeks 1, 4, 7, and 10. Exercises included the standing chest press, standing row, front raise, Pallof press, single-leg deadlift, step-up, and squat. |
Primary outcomes
Functional performance
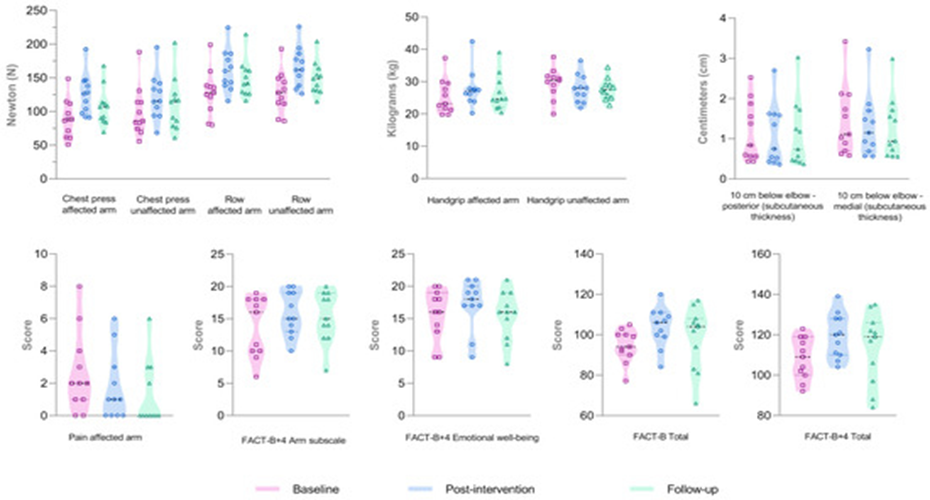
A time-dependent improvement in maximal voluntary isometric contraction (MVIC) was evident in the unilateral chest press for both affected (p < 0.001) and unaffected arms (p = 0.001) and in the unilateral standing row for both arms (p < 0.001) (Figure 3). Post-hoc comparisons showed significant gains at post-intervention relative to baseline in chest press (p < 0.001 and p = 0.004 for affected and unaffected arms, respectively) and in the row (p = 0.006 and p = 0.001 for affected and unaffected arms). At follow-up, the row test remained significantly improved compared to baseline (p = 0.045 for the affected arm, p = 0.025 for the unaffected). In the squat MVIC, improvements were present but not statistically significant at either post-intervention or follow-up assessments.
|
|
|
Figure 3. Functional and clinical parameters showing significant time effects. |
Abbreviations: FACT-B+4 = Functional Assessment of Cancer Therapy–Breast plus 4; cm = centimeters.
Molecular biomarkers
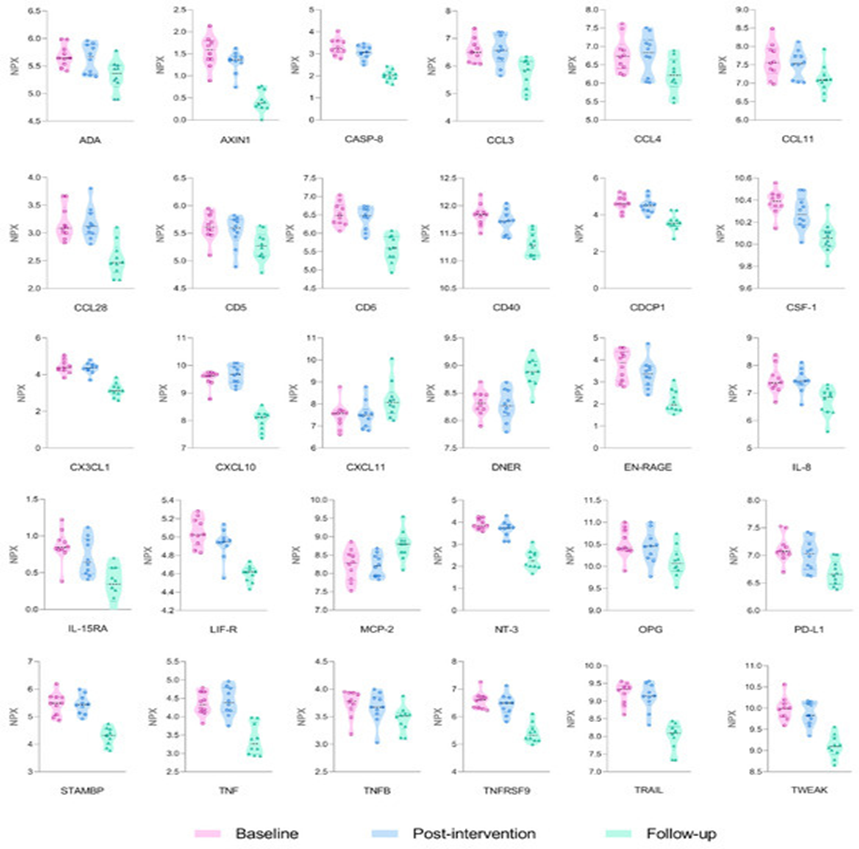
A targeted proteomic assessment, including 92 inflammation-associated proteins, was conducted. Eighteen markers were below the limit of detection (LOD) in ≥75% of the samples and were excluded from further testing. Blood samples from 10 participants were analyzed at three time points: baseline, post-intervention, and follow-up. In total, 30 proteins displayed significant time effects (p < 0.001) (Figure 4).
|
|
|
Figure 4. Proteins with statistically significant time effects. |
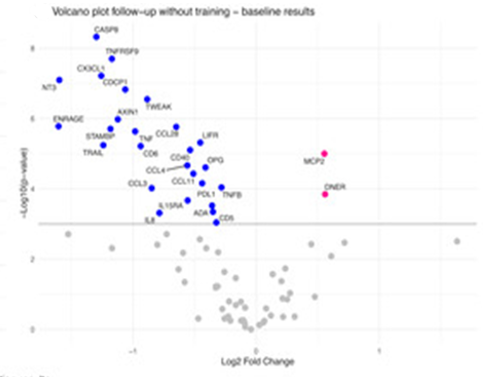
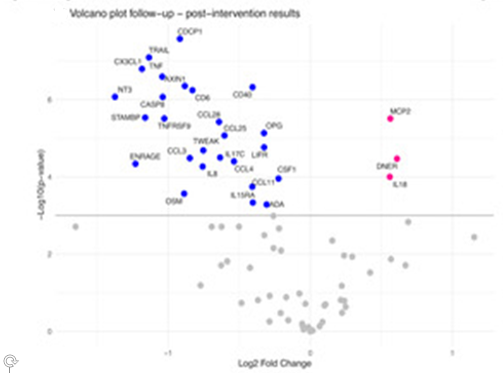
Post-hoc evaluation revealed that 19 proteins declined significantly at follow-up in comparison with both baseline and post-intervention results (p < 0.001). These included Axin-1 (AXIN1), caspase-8 (CASP-8), C-C motif chemokine 3 (CCL3), C-C motif chemokine 4 (CCL4), C-C motif chemokine 28 (CCL28), CD6, CD40, CDCP1, CX3CL1, S100-A12 (EN-RAGE), LIF-R, NT-3, OPG, PD-L1, STAMBP, TNF, TNFRSF9, TRAIL, and TWEAK.
Additionally, TNF-beta (TNFB), CSF-1, and CCL11 levels were lower at follow-up compared to baseline, while IL-8 and CCL25 decreased between post-intervention and follow-up (p < 0.001). In contrast, MCP-2 and DNER concentrations rose significantly at follow-up relative to both earlier points (p < 0.001).
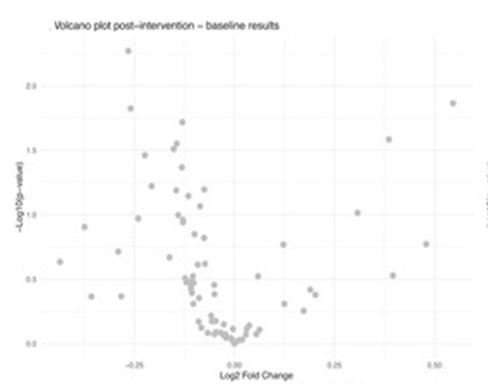
Mean values for 55 proteins were reduced after the intervention relative to baseline, but these changes were not statistically significant (Figure 5a). Beyond the previously mentioned markers, significant decreases were found for ADA, CD5, IL-8, and IL-15RA at follow-up compared with baseline (p < 0.001) (Figure 5b). Similarly, ADA, IL-15RA, OSM, and CSF-1 were significantly lower at follow-up than at post-intervention (p < 0.001) (Figure 5c).
|
|
|
|
a) |
b) |
|
|
|
|
c) |
|
|
Figure 5. Volcano plots were utilized to evaluate the NPX protein levels across three comparisons: (a) post-intervention vs. baseline, (b) follow-up vs. baseline, and (c) follow-up vs. post-intervention. On the y-axis, log₁₀-transformed p-values are shown, while the x-axis depicts the log₂ fold changes between time points. Negative fold change values indicate decreased protein expression after the intervention or during follow-up. Proteins with statistically significant differences (p < 0.001) are labeled on the plots. |
|
Secondary outcomes
Clinical metrics
No statistically meaningful changes were detected in BMI, total arm volume, inter-arm volume differences, shoulder range of motion, MVPA, or heart rate variability parameters (mean RR, SDNN, RMSSD, LF, HF). However, the medial subcutaneous tissue thickness distal to the elbow showed a significant effect over time (p = 0.013) with a reduction observed at follow-up compared with baseline (p = 0.048). Posterior subcutaneous tissue thickness also demonstrated a significant temporal effect (p = 0.029), although subsequent post hoc comparisons did not reach statistical significance (Figure 3).
Functional metrics
Handgrip strength showed a significant time effect for the affected arm (p = 0.020), increasing post-intervention relative to baseline (p = 0.021). For the unaffected arm, a significant effect over time was observed (p = 0.005), with a decrease at follow-up compared with post-intervention (p = 0.046) (Figure 3). No significant alterations were observed for VO₂peak.
Patient-reported outcomes
Pain, assessed by NRS, showed a significant temporal effect (p = 0.038), with post-intervention scores lower than baseline (p = 0.005). FACT-B+4 scores indicated significant changes over time for the arm subscale (p = 0.016), emotional well-being (p = 0.039), total FACT-B (p = 0.011), and total FACT-B+4 (p = 0.003). Post hoc analysis confirmed improvements in all domains except the arm subscale: emotional well-being (p = 0.027), total FACT-B (p = 0.005), and FACT-B+4 total score (p = 0.001). DASH questionnaire scores did not show significant changes.
Correlation analyses
Positive correlations were observed between improvements in chest press and row strength from baseline to post-intervention in both the affected (r = 0.915, p < 0.001) and unaffected arms (r = 0.656, p = 0.028). FACT-B increases were positively associated with FACT-B+4 total score increases (r = 0.937, p < 0.001).
For changes from baseline to follow-up, row strength improvements in the affected arm correlated positively with alterations in CCL3 (r = 0.716, p = 0.020) and CCL11 (r = 0.779, p = 0.008). Additionally, subcutaneous tissue thickness changes were significantly associated with changes in CCL3 (r = 0.687, p = 0.028), CSF-1 (r = 0.681, p = 0.030), MCP-2 (r = 0.658, p = 0.039), and DNER (r = −0.701, p = 0.024).
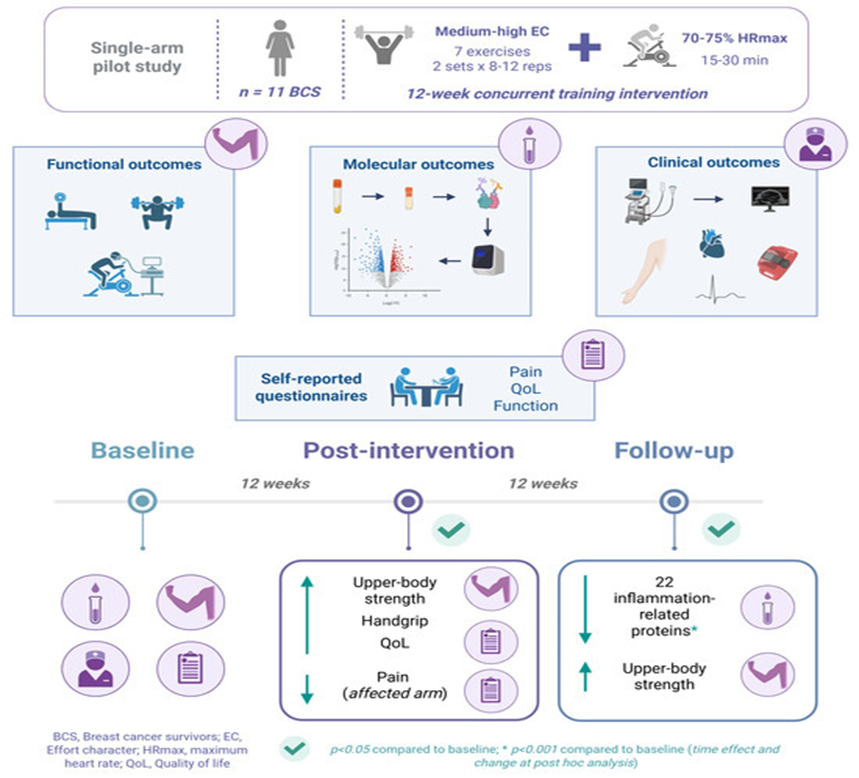
This study demonstrated that a 12-week concurrent training program in BCS with or at risk of BCRL led to significant gains in upper-body strength (unilateral chest press and row MVIC), handgrip strength in the affected arm, reductions in pain, improved emotional well-being, and better overall quality of life. At post-intervention, inflammation-related proteins did not significantly change, although a downward trend was observed: 55 of 74 analyzed proteins had lower mean levels than at baseline.
After a 12-week detraining period, gains in row MVIC persisted, and several inflammation-associated proteins showed significant reductions compared to baseline: AXIN1, CASP-8, CCL3, CCL4, CCL11, CCL28, CD6, CD40, CDCP1, CSF-1, C3XCL1, EN-RAGE, LIF-R, NT-3, OPG, PD-L1, STAMBP, TNF, TNFB, TNFRSF9, TRAIL, and TWEAK (Figure 6). No adverse events or BCRL exacerbations occurred.
|
|
|
Figure 6. Summary of key study outcomes. |
Systemic inflammation is an established prognostic marker for BCS, as higher levels correlate with increased comorbidity and recurrence risk [49]. Transcriptomic analyses in cancer-related lymphedema highlight distinct RNA and protein inflammatory profiles, supporting the role of chronic inflammation [7]. Prior work in 21 BCS with BCRL showed that acute resistance exercise at various intensities did not elevate inflammatory markers [50]. However, no previous studies evaluated the long-term effects of exercise on proinflammatory proteins in BCS with or at risk of BCRL.
Our findings provide insights into the chronic effects of 12 weeks of concurrent training followed by a 12-week detraining period. Notably, 22 inflammation-related proteins showed significant time effects and decreased significantly at follow-up relative to baseline: AXIN1, CASP-8, CCL3, CCL4, CCL11, CCL28, CD6, CD40, CDCP1, CSF-1, C3XCL1, EN-RAGE, LIF-R, NT-3, OPG, PD-L1, STAMBP, TNF, TNFB, TNFRSF9, TRAIL, and TWEAK.
Among these, six proteins (OPG, TNF, TNFB, TNFRSF9, TRAIL, and TWEAK) are members of the TNF/TNFR superfamily, which regulate inflammation through NF-κB signaling [51] and may be relevant to BCRL [52]. Additional proteins belong to CC (CCL3, CCL4, CCL11, CCL28) and CX3C (C3XCL1) chemokine families, which are proinflammatory [53, 54]. Dysregulation of cytokine and chemokine signaling contributes to chronic inflammation and may promote cancer-related pathology [55, 56].
Moreover, the expression of PD-L1 is elevated in several cancer types, including breast cancer (BC), following stimulation by pro-inflammatory cytokines [57]. Likewise, CD6, CD40, and CDCP1 contribute to immune system dysfunction [58], heightened inflammation through increased reactive oxygen species and chemokine synthesis [59], and unfavorable BC outcomes [60]. Additionally, CSF-1 is abundantly present in immune cells, where it plays a vital role in the advancement of numerous inflammatory disorders [61]. AXIN1 enhances inflammatory activity by activating the Stress-Activated Protein Kinase/Jun N-terminal Kinase signaling route, which drives the release of pro-inflammatory mediators [62]. CASP-8 is also implicated in many inflammatory and immune-related diseases, including cancers [63]. EN-RAGE functions as a key circulating pro-inflammatory biomarker because its binding to the receptor for advanced glycation end products initiates multiple signaling cascades—such as nuclear factor-κB (NF-κB) and mitogen-activated protein kinase—that elevate pro-inflammatory cytokine output [64]. The LIFR receptor complex is multifunctional, allowing numerous ligands to trigger distinct signaling pathways. When leukemia inhibitory factor binds to LIFR, it activates the Akt–mammalian target of rapamycin (mTOR) pathway, encouraging tumor growth and metastasis [65]. Similarly, NT-3 binds to its receptor—tropomyosin receptor kinase—which is overexpressed in BC and activates the phosphatidylinositol 3-kinase (PI3K)-Akt pathway, enhancing cellular proliferation [66]. This PI3K-Akt cascade also contributes to inflammatory processes and has been linked with lymphatic dysfunction in individuals with primary lymphedema [67]. Furthermore, STAMBP expression is associated with worse prognoses among patients diagnosed with triple-negative BC [68].
A reduction in these inflammation-associated proteins indicates that concurrent training might exert a protective impact observable during follow-up, possibly due to delayed physiological adaptations. A recent meta-analysis revealed that major inflammatory and growth-related factors—TNF-α, IGF-1, IL-6, CRP, and IL-10—tended to decline after exercise, though outcomes varied with exercise type and program duration (≤12 weeks) [20]. Exercise is known to lower inflammatory levels by improving endothelial performance and insulin responsiveness. On the other hand, short-term exercise may temporarily alter inflammation, whereas regular long-term activity leads to more sustained decreases [49]. This could explain why our study’s improvements appeared after the 12-week follow-up instead of immediately post-intervention. Still, inflammation did not significantly rise from baseline to the intervention’s end, confirming the safety of concurrent training in BC survivors (BCS) with or at risk for breast cancer-related lymphedema (BCRL). Previous findings also reported reduced TNF-α plasma concentrations in BCS after six months of exercise, supporting the prolonged anti-inflammatory potential of physical activity [69]. Nonetheless, future studies with larger samples are warranted to validate these findings in BCS with or prone to BCRL, as prior research has shown immediate anti-inflammatory benefits following combined training among BC patients and survivors [70, 71]. Although some evidence links intervention duration (>11 weeks) to IL-6 changes [21], a recent review suggested that programs lasting over 16 weeks might produce stronger effects in BCS [18], pointing to a dose–response relationship. Yet, the ideal training length for maintaining exercise-derived benefits remains uncertain. Further investigations should test extended interventions to evaluate how long exercise-driven reductions in inflammation persist among BCS.
Earlier studies have indicated that higher circulating pro-inflammatory cytokines correspond with lower muscle mass and strength in adults. IL-6, in particular, has a dual role—facilitating either anabolic or catabolic muscle activity depending on conditions. Nevertheless, chronic exposure to IL-6 and other cytokines can suppress anabolic mechanisms, disrupt energy regulation, and directly promote muscle degradation [72]. It has therefore been proposed that elevated pro-inflammatory cytokine levels may underlie cancer-related muscle loss [73]. BC patients often show lower strength scores than healthy controls both before and after therapy [74], potentially linked to joint dysfunction. In agreement with past research on resistance training [23], our outcomes support that a concurrent regimen—combining resistance and aerobic components—substantially improves upper-body strength in BCS affected by or at risk for BCRL. This gain could also help shield the arm from injuries by lessening mechanical strain during everyday movements [75].
For lower-body strength, while statistical significance was not reached, a mean increase of 232.38 N was observed between baseline and post-intervention, potentially meaningful for this group. A randomized controlled trial in BC patients receiving adjuvant therapy reported that enhanced one-repetition maximum leg press performance after 12 weeks of resistance exercise correlated with improved walking endurance and reduced fatigue during incremental walking, indicating better functional outcomes [76]. Similar leg press improvements were confirmed in a meta-analysis on participants with BCRL or at risk [75]. The absence of notable lower-body strength gains in our results might stem from using the isometric squat test rather than the leg press or knee extension, which are more common in prior studies [23, 75]. Handgrip strength—another key indicator of upper-limb function [77] and a general health marker [78]—was significantly higher in the affected arm following 12 weeks of concurrent training, implying meaningful clinical benefits for this population [79].
Reports of pain showed a marked decline after the intervention compared with baseline values. Even though the perception of pain is a subjective measure that may be influenced by participant bias, the Numeric Rating Scale (NRS) remains a suitable instrument for its evaluation due to its responsiveness to change and strong applicability in research contexts [80]. Likewise, overall quality of life (QoL), measured by the FACT-B+4 questionnaire, improved notably following the concurrent training sessions. These results are in accordance with a previous 12-week randomized resistance exercise trial involving breast cancer (BC) patients receiving adjuvant radiotherapy [81]. Moreover, a meta-analysis indicated that women with breast cancer-related lymphedema (BCRL) who demonstrated high adherence to the American College of Sports Medicine (ACSM) guidelines achieved larger QoL improvements compared to those with poor adherence [82]. This reinforces the relevance of structured, supervised physical training within this group. Although QoL is inherently subjective, its strong association with BCRL onset and progression [83] underlines the need to include patient-reported indicators when assessing intervention outcomes.
When evaluating arm volume and tissue thickness, no significant post-intervention changes were found. Nonetheless, follow-up analyses revealed a significant reduction in subcutaneous tissue thickness at the lateral region of the forearm relative to baseline. Importantly, a downward trend in subcutaneous tissue thickness was observed across all measured regions after the intervention, which could have clinical value. The absence of statistical significance at post-intervention might be explained by inter-individual differences in lymph fluid build-up and fibrosis patterns across the arm. Prior evidence showed that 8 weeks of resistance training significantly decreased subcutaneous tissue thickness among BCRL patients [35], suggesting exercise may positively influence this measure. More comprehensive studies should examine region-specific tissue adaptations and consider muscle growth factors [23], since evaluating arm volume alone may not capture relevant physiological changes. Although limb circumference remains a practical measure of BCRL severity, mathematical formulas used to estimate arm volume can yield overestimations when compared with water-displacement techniques [34]. The International Society of Lymphology (ISL) further recommends incorporating imaging-based tools—such as ultrasound—to assess tissue composition and lymphatic drainage variations [25]. All participants in this trial who had BCRL had previously completed the intensive phase of Complex Decongestive Therapy (CDT), which likely contributed to the observed stability in arm volume. Indeed, maintenance-phase care primarily aims to preserve reductions already achieved and prevent recurrence rather than induce new therapeutic effects [84].
The findings indicate that concurrent training was well-tolerated and led to measurable gains in both molecular and functional domains, as well as in subjective outcomes, among breast cancer survivors (BCS) with or vulnerable to BCRL. Furthermore, the exercise protocol did not aggravate lymphedema symptoms or increase inflammation, as reflected by stable arm volume and tissue thickness data. Nevertheless, baseline conditions—such as body mass index (BMI) [85]—and unmonitored dietary habits might have influenced molecular outcomes. Since participants’ food intake was not tracked, nutritional variations could have impacted plasma protein expression, consistent with earlier findings linking diet to protein concentrations [86]. Another limitation was the small sample size. Although power calculations suggested that the available sample (n = 11) was sufficient to identify large effect sizes, subtle differences in some parameters may have gone undetected. The single-arm design, while appropriate for feasibility assessment, restricts conclusions regarding causality. Despite this, the current study aimed primarily to provide exploratory data through a novel, long-term analysis of inflammation-related proteins. A future randomized controlled design with a larger cohort would help verify and expand upon these observations by comparing intervention outcomes with those of a usual-care group.
The present findings contribute preliminary but valuable evidence on the advantages of concurrent exercise in BCS who have, or may develop, BCRL. Functionally, the results partly mirror earlier studies where resistance programs significantly enhanced both upper- and lower-limb strength [23, 75]; however, in this trial, only upper-body strength improved significantly. On the molecular level, results were consistent with prior reports showing that resistance exercise did not elevate inflammatory protein levels 24 hours after training across varying intensities [22]. In addition, a recent systematic review concluded that combined aerobic and resistance training is particularly effective for preventing and managing BCRL when tailored to individual capacity [87].
Conclusion
The 12-week supervised concurrent training protocol led to significant improvements in handgrip and upper-body strength, reductions in pain, and enhanced physical and emotional well-being and overall QoL among BCS with, or at risk for, BCRL. While most inflammation-related proteins exhibited non-significant downward trends immediately after training, molecular adjustments became evident after a 12-week follow-up without additional exercise, during which muscle strength gains were retained. This suggests lasting physiological benefits of such training for BCS recovery. The program was well tolerated, with no adverse effects recorded. However, the study’s single-arm design and limited sample constrain generalization, emphasizing the need for larger randomized controlled trials to validate these preliminary findings and further explore the long-term implications of concurrent training in this population.
Acknowledgments: None
Conflict of Interest: None
Financial Support: None
Ethics Statement: None