Sarcomas display considerable histological diversity, with over 70 recognized subtypes, which complicates precise classification. Although specific genetic alterations can aid pathological evaluation, routine diagnostic workflows rarely incorporate large-scale molecular profiling. In this study, we explored the utility of whole genome sequencing (WGS) to enhance the clinical management of sarcoma patients by detecting diagnostic markers, therapeutically actionable variants, and underlying hereditary predispositions. Tumor and germline DNA from 83 patients with suspected sarcomas at a tertiary referral center were subjected to WGS, and patients were followed prospectively to determine the impact on clinical decisions. In 14% of cases (12/83), genomic analysis prompted a revision of the initial diagnosis, leading to treatment modifications in eight patients. Notably, all these cases had undergone multiple tissue sampling procedures and detailed immunohistopathological evaluations by both regional and expert pathologists before WGS. Additionally, potential therapeutic biomarkers were identified in 30 patients, and pathogenic germline variants were observed in seven. Overall, unbiased WGS enables the identification of genomic features with direct implications for patient care. Considering the diagnostic challenges and the urgent need for novel therapeutic options in sarcoma, WGS provides a valuable enhancement to conventional diagnostic approaches.
Introduction
Sarcomas constitute approximately 1% of all adult solid tumors. Despite their shared mesenchymal origin, these tumors are highly diverse, exhibiting unique pathological and clinical profiles across more than 70 histological subtypes. This diversity makes accurate classification a considerable challenge. In a review of 1,463 second-opinion sarcoma cases, nearly half of the expert assessments differed from the initial diagnoses [1], highlighting the critical importance of precise identification for optimal treatment planning and reliable clinical research outcomes.
Molecular characterization has become increasingly valuable in supporting histopathological evaluation. Certain sarcoma subtypes are defined by distinctive genetic alterations. For instance, MDM2 amplification—often co-occurring with CDK4 and HMGA2—is typical of dedifferentiated liposarcomas; synovial sarcomas frequently exhibit SS18–SSX fusions; and spindle cell/sclerosing rhabdomyosarcomas are associated with MYOD1 mutations [2, 3]. While targeted molecular tests are routinely applied when specific diagnoses are suspected, comprehensive genomic profiling is not standard practice for all sarcoma patients. Reliance solely on immunohistochemistry can result in diagnostic errors in approximately 14% of cases, even when pathologists report high confidence [4]. Moreover, selecting the most appropriate molecular test remains challenging, often leaving clinically relevant genomic events undetected. Indeed, unbiased whole-genome sequencing (WGS) has been shown to revise the diagnosis in 3% of sarcoma patients who had already undergone extensive conventional diagnostics [5].
Beyond its diagnostic utility, WGS offers additional clinical advantages by analyzing germline DNA alongside tumor genomes. This approach allows for the detection of previously unrecognized pathogenic germline variants. Germline mutations in cancer predisposition genes are observed in 10–15% of adult-onset sporadic sarcomas, yet many hereditary syndromes remain undiagnosed [6, 7]. Furthermore, retrospective analyses of large metastatic cancer cohorts (over 3,000 patients) demonstrate that WGS can uncover biomarkers with actionable therapeutic implications for the majority of cases [8].
Overall, comprehensive genomic analysis via WGS has the potential to prevent misdiagnosis, reveal new treatment opportunities, and identify previously unrecognized hereditary conditions. Here, we evaluate the clinical impact of prospective WGS in 83 patients with advanced or metastatic sarcomas at a specialized sarcoma center, demonstrating its direct relevance for patient management.
Materials and Methods
Study cohort
This study included patients from the WIDE (WGS Implementation in standard Diagnostics for Each cancer patient) trial, which enrolled 1,200 individuals with suspected or confirmed metastatic cancer between April 2019 and January 2021. A comprehensive description of the study design and objectives is available in the study protocol [9]. For patients undergoing WGS, tumor profiling was conducted independently and in parallel with standard diagnostic procedures. Eligible patients either underwent tissue sampling or required pathologic evaluation of fresh-frozen archival material. All procedures were approved by the Medical Ethical Committee of the Netherlands Cancer Institute (NL68609.031.18) and adhered to the Declaration of Helsinki, Dutch law, and Good Clinical Practice. Eighty-three participants with suspected sarcomas at enrollment were included in this analysis.
Sample acquisition
Tumor material—either from primary lesions, metastatic sites, or tumor-containing fluids—was collected during routine clinical procedures. After reserving sufficient tissue for conventional diagnostics, one sample was submitted to the Hartwig Medical Foundation for WGS analysis [9]. Additionally, a 10 mL blood sample was collected from each patient to facilitate germline DNA sequencing, which enabled accurate identification of somatic variants.
Conventional diagnostic workflow
WGS was performed independently from routine diagnostic testing. Standardized clinical tests were conducted as indicated by treating physicians or pathologists. The pathology department at NKI utilizes an array of molecular techniques, including targeted NGS panels (Ampliseq Cancer Hotspot Panel V2, Illumina, San Diego, CA), RNA-based NGS fusion panels (Archer FusionPlex Lung and Sarcoma panels, ArcherDX, Boulder, CO), Sanger sequencing, RT-PCR, in situ hybridization, and immunohistochemistry. All procedures follow ISO15189-accredited standards.
Whole-genome sequencing workflow and reporting
Whole-genome sequencing (WGS) was conducted according to the standard procedures of the Hartwig Medical Foundation in Amsterdam, Netherlands [10]. DNA was extracted from fresh-frozen tumor samples and sequenced to a depth of approximately 90–100×, while germline DNA obtained from blood samples was sequenced at ≥30× coverage using the Illumina® NovaSeqX platform. Comparing tumor DNA to the patient’s germline genome enabled the accurate identification of somatic variants unique to the tumor. A comprehensive report detailing all genomic alterations—including single nucleotide variants, structural rearrangements, copy number variations, fusions, microsatellite instability, tumor mutational burden, and homologous recombination deficiencies—was provided to treating physicians, along with potential diagnostic and therapeutic implications. Variant pathogenicity was assessed using previously established oncogenic driver scoring methods [8], and, when necessary, additional functional or protein-level assays were performed to confirm potentially pathogenic variants. The clinical relevance of each finding was evaluated, either in terms of standard therapies, such as imatinib for KIT-mutated GIST, or eligibility for ongoing clinical trials in the Netherlands. All results were reviewed by a multidisciplinary team composed of molecular biologists, pathologists, clinical geneticists, and oncologists before being shared with the treating clinicians. The bioinformatics workflow for WGS is publicly available [11], and the facility maintains ISO17025 accreditation.
Germline variant assessment
Patients were offered the option to receive information on germline variants associated with their tumors. Only variants with potential clinical significance for treatment decisions, follow-up care, or familial risk were reported. Individuals with detected pathogenic germline variants were referred to the Department of Clinical Genetics for counseling. To estimate the prevalence of clinically relevant variants in this cohort, an anonymized retrospective analysis of 49 cancer predisposition genes was conducted using the Hartwig Medical Foundation pipeline [11], focusing on variants classified as pathogenic or likely pathogenic (class 4 or 5) that could impact diagnosis or therapy.
Statistical analysis
Descriptive statistics were used to summarize patient characteristics, tumor features, and WGS findings. Differences in the number of tissue retrieval procedures and pathology assessments between patients who experienced diagnostic revisions after WGS and those who did not were analyzed using independent sample t-tests with IBM SPSS v25 (Chicago, IL, USA). Data regarding treatment outcomes following experimental therapies identified through WGS were not collected.
Results and Discussion
Characteristic genomic events
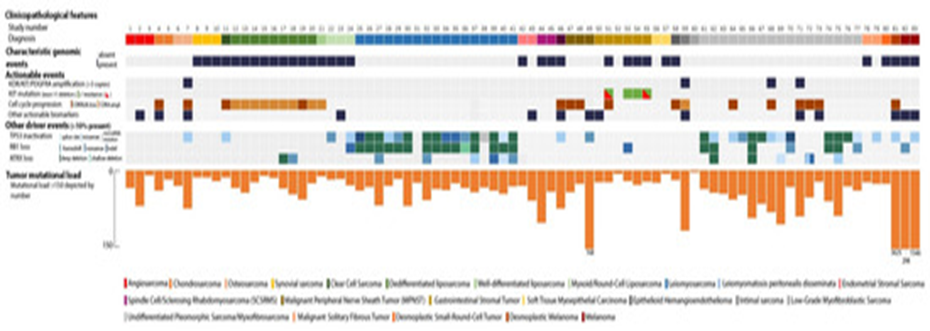
The study cohort included 83 patients with suspected sarcomas, encompassing 23 distinct histological subtypes (Table 1 and Figure 1). Tumor-specific genomic alterations were detected in 32 cases. Several rare sarcoma subtypes displayed hallmark genetic events that aided diagnosis. For example, the desmoplastic small-round-cell tumor exhibited an EWSR1–WT1 fusion, whereas epithelioid hemangioendothelioma was defined by a WWTR1–CAMTA1 fusion. All three synovial sarcomas carried an SS18–SSX1 fusion, and clear cell sarcoma harbored an EWSR1–ATF1 fusion. Two malignant solitary fibrous tumors demonstrated NAB2–STAT6 fusions, while the osseous spindle cell rhabdomyosarcoma displayed a FUS–TFCP2 fusion. Spindle cell/sclerosing rhabdomyosarcomas contained MYOD1 p.Leu122Arg mutations, and all three myxoid/round-cell liposarcomas showed the FUS–DDIT3 fusion, previously known as FUS–CHOP. Among endometrial stromal sarcomas, one was characterized by an MEAF6–PHF1 fusion, whereas the other did not exhibit a previously reported fusion. In the two soft tissue myoepithelial carcinomas, only one revealed an EWSR1–POU5F1 fusion. Additionally, all well-differentiated and dedifferentiated liposarcomas in the cohort demonstrated co-amplification of MDM2 and CDK4. These findings underscore the utility of WGS in identifying diagnostic genomic markers, particularly in rare or challenging sarcoma subtypes.
|
|
|
Figure 1. Oncoplot showing genomic information per sample. |
Table 1. Patient characteristics.
|
Patient Characteristics |
n = 83 |
|
Age at diagnosis, years |
|
|
Median |
54 |
|
Range |
22–83 |
|
Age at WGS analysis, years |
|
|
Median |
58 |
|
Range |
23–84 |
|
Gender, male:female |
46:37 |
|
Previous lines systemic treatment, n (%) |
|
|
0 |
52 (63%) |
|
1 |
18 (22%) |
|
2 |
12 (14%) |
|
3 |
1 (1%) |
|
Primary tumor localization, n (%) |
|
|
Head/neck |
8 (10%) |
|
Intrathoracic/mediastinal |
5 (6%) |
|
Intraabdominal/retroperitoneal/pelvic |
34 (41%) |
|
Trunk |
15 (18%) |
|
Extremity |
21 (25%) |
|
Disease stage |
|
|
Metastatic |
68 (82%) |
|
Advanced |
15 (18%) |
|
Tissue retrieval procedures (n) * |
|
|
1 |
37 |
|
2 |
17 |
|
3 |
10 |
|
4 |
3 |
|
5 |
2 |
|
>5 |
2 |
|
Pathological assessments (n) * |
|
|
1 |
27 |
|
2 |
17 |
|
3 |
7 |
|
4 |
13 |
|
5 |
2 |
|
>5 |
5 |
* Number of tissue retrieval procedures and pathological assessments including revisions needed to reach final diagnosis. Data not available for 12 patients.
Among the six gastrointestinal stromal tumors (GIST) analyzed, a majority carried deletions in KIT exon 11. Two of these patients had previously received imatinib therapy and developed secondary KIT mutations (p.Asn822Tyr and p.Val654Ala), which are associated with resistance to the drug. Interestingly, one patient was found to carry a previously unrecognized germline SDHA mutation, resulting in a confirmed GIST diagnosis. In the final case, whole-genome sequencing (WGS) uncovered an NTRK driver mutation (p.Lys104del), which had been missed by earlier routine genetic analyses, including targeted NGS panels and fusion testing, but was validated at the RNA level and by immunohistochemistry for NTRK expression.
Examination of leiomyosarcomas revealed that nearly all tumors (15 of 17) had disruptions in both RB1 and TP53, highlighting a recurrent pattern in this subtype. Among the remaining two, one tumor retained RB1 integrity but had a single TP53 mutation, while the other appeared to arise in the context of pre-existing leiomyomatosis that progressed to a low-grade intra-abdominal leiomyosarcoma. In this latter case, histological and genetic features suggested that the biopsy sample may have contained residual benign tissue rather than the fully malignant tumor.
Across the cohort, TP53, RB1, ATRX, and CDKN2A were the most frequently altered genes, each affected in more than 10% of patients. Notably, four tumors—including leiomyomatosis, low-grade myofibroblastic sarcoma, osteosarcoma, and a GIST—showed no detectable somatic driver events. Among these, the osteosarcoma and GIST patients carried germline variants in TP53 and SDHA, respectively, demonstrating the utility of WGS in uncovering underlying hereditary risks.
Incorporating WGS into the diagnostic workflow resulted in revised diagnoses for twelve patients, representing 14% of the cohort. These included cases that were initially misclassified based on morphology alone. For instance, one patient initially diagnosed with adenocarcinoma of unknown primary in the head and neck region was reclassified as a synovial sarcoma after detection of an SS18–SSX1 fusion. Similarly, three cases previously identified as alveolar or embryonal rhabdomyosarcoma, or undifferentiated pleomorphic sarcoma, were corrected to spindle cell/sclerosing rhabdomyosarcoma following identification of either MYOD1 mutations or an FUS–TFCP2 fusion. Additional reclassifications included a soft tissue Ewing sarcoma, which was revealed to be a myoepithelial carcinoma after WGS detected an EWSR1–POU5F1 fusion, and a previously unclassified tumor that was assigned as a desmoplastic small-round-cell tumor based on the presence of an EWSR1–WT1 fusion.
Overall, these findings highlight the significant value of WGS in sarcoma diagnostics, uncovering both previously undetected driver mutations and germline variants, and correcting misclassifications that have direct implications for patient management.
Table 2. Diagnostic revisions based on WGS analysis.
|
Study Nr |
Suspected Diagnosis |
Localization |
Molecular Diagnostic Test Performed |
Diagnostic Revision |
Based on |
|
8 |
Adenocarcinoma of unknown primary |
Head/neck |
IHC, SISH (HER2), NGS panel |
Synovial sarcoma |
SS18—SSX1 fusion |
|
44 |
Alveolar rhabdomyosarcoma |
Head/neck |
IHC, RT-PCR, fusion analysis |
Spindle-cell/sclerosing rhabdomyosarcoma |
MYOD1 p.Leu122Arg |
|
45 |
Embryonal rhabdomyosarcoma |
Head/neck |
IHC, FISH, methylation assay, fusion analysis |
Spindle cell/sclerosing rhabdomyosarcoma |
MYOD1 p.Leu122Arg |
|
46 |
Osteosarcoma, undifferentiated pleiomorphic sarcoma of bone |
Head/neck |
IHC |
Spindle cell/sclerosing rhabdomyosarcoma |
FUS—TFCP2 fusion |
|
47 |
Sarcomatoid mesothelioma vs. sarcoma |
Intrathoracic/mediastinal |
IHC, fusion analysis |
Sarcoma NOS |
Complete genomic profile, including lack of NF2 and BAP1 driver events |
|
54 |
Wild-type GIST |
Intra-abdominal |
IHC, NGS panel (2×), fusion analysis |
KIT mutated GIST |
KIT exon 11 deletion (51 nucleotides) |
|
57 |
Ewing sarcoma |
Trunk |
IHC, fusion analysis, RT-PCR (EWS1), FISH |
Myoepithelial carcinoma |
EWSR1—POU5F1 fusion |
|
63 |
Dedifferentiated liposarcoma (recurrence) |
Trunk |
- |
Radiotherapy-associated second primary |
Lack of MDM2/CDK4 co-amplification |
|
80 |
Carcinoma of unknown primary |
Intra-abdominal |
IHC |
Desmoplastic Small-Round-Cell Tumor |
EWSR1—WT1 fusion |
|
81 |
Malignant peripheral nerve sheath tumor |
Head/neck |
IHC, fusion analysis |
Melanoma |
High ML/UV-signature, TERT promoter mutation |
|
82 |
Melanoma vs. sarcoma |
Extremity |
IHC, fusion analysis |
Melanoma |
High ML/UV-signature, TERT promoter mutation |
|
83 |
Interdigitating dendritic cell sarcoma |
Extremity |
IHC, NGS panel (2×), FISH |
Melanoma |
High ML/UV-signature, TERT promoter mutation |
IHC = immunohistochemistry, SISH = silver in situ hybridization, FISH = fluorescence in situ hybridization, RT-PCR = reverse transcription polymerase chain reaction, NGS = next-generation sequencing.
During WGS analysis, three tumors initially suspected to be sarcomas were revealed to be melanomas, reflecting a well-known diagnostic challenge. Each of these cases exhibited genomic hallmarks typical of melanoma, including a higher overall mutational burden than conventional sarcoma samples, ultraviolet-related mutational signatures (COSMIC signature 7, C > T transitions), and driver alterations in the TERT promoter region. One of these patients also carried a BRAF p.Val600Glu mutation. More specifically, one patient presented with an axillary lymph node metastasis initially thought to originate from an interdigitating dendritic cell sarcoma. Another case involved a tumor first diagnosed as a trigeminal schwannoma, later revised to malignant peripheral nerve sheath tumor due to aggressive clinical progression; WGS ultimately identified it as a desmoplastic melanoma, consistent with its deep dermal and subcutaneous location, perineural invasion, and absence of melanA/HMB45 staining. In the third case, a small-blue-round-cell tumor on the thigh could not be clearly classified as either sarcoma or melanoma based on histology and immunostaining, but the genomic profile, including a BRAF p.Val600Glu mutation, confirmed a melanoma diagnosis.
In a separate case, a suspected locoregional recurrence of a dedifferentiated liposarcoma was reclassified as a secondary, radiotherapy-associated sarcoma. This revision was based on the absence of the characteristic MDM2/CDK4 co-amplification and the presence of widespread deletions flanked by microhomology, a genomic signature linked to prior ionizing radiation exposure. Additionally, one pleural tumor initially considered as either sarcomatoid mesothelioma or sarcoma was ultimately classified as sarcoma after the lack of canonical mesothelioma driver events (NF2, BAP1) and negative H3K27me3 staining.
WGS also uncovered a large KIT exon 11 deletion (51 nucleotides) in a patient previously classified as having a wild-type GIST, which had been missed by standard NGS analyses. This finding underscores the technical challenges of detecting large indels with conventional NGS, including primer-binding limitations and software recognition. Retrospective review of 71 GIST samples in the HMF database revealed that approximately 6% harbored similarly large indels, highlighting the need for careful diagnostic strategies in presumed wild-type cases.
Analysis of the patients’ diagnostic histories showed that revised cases had undergone a substantial number of tissue retrieval procedures and separate pathological assessments prior to WGS. Each patient received multiple biopsies or resections, with at least two independent pathologists reviewing the material. Among revised cases, the mean number of prior procedures was significantly higher than for cases with unchanged diagnoses (4 versus 2, p < 0.05), and the mean number of pathologists involved was also greater (6 versus 2, p < 0.05), reflecting the complexity of these diagnoses.
Regarding germline findings, seven patients carried eight pathogenic variants. While two variants (BRCA1 p.Gln12* and TP53 p.Arg196Ter) were already known from prior germline testing, six additional variants were only discovered through WGS. Notably, a young female patient with a wild-type GIST was found to carry an SDHA p.Arg31* germline mutation, previously unrecognized due to lack of family history, leading to confirmation of succinate dehydrogenase deficiency by immunohistochemistry. Another patient with a UPS and a prior history of Ewing sarcoma harbored a TP53 splice site mutation (c.782 + 1G > A). Four germline CHEK2 variants were also identified, including a p.Glu64Lys mutation in a patient already carrying BRCA1 p.Gln12* and three c.1100delC variants, known Dutch founder mutations. Somatic loss of the second CHEK2 allele occurred in one patient, while the others likely arose independently of the germline variant. The clinical significance of CHEK2 mutations in sarcoma remains uncertain.
The diagnostic revisions provided by WGS directly influenced patient management. Seven patients had modifications to their standard-of-care treatment. For example, detection of a KIT mutation in a GIST prompted a switch from sunitinib to imatinib, preserving sunitinib as a second-line option. Patients with revised melanoma diagnoses received guideline-directed immunotherapy or BRAF-targeted therapy, replacing prior regimens based on incorrect sarcoma classification. Similarly, a young female patient originally slated for intensive chemotherapy for presumed Ewing sarcoma underwent surgery instead after her tumor was reclassified as a soft tissue myoepithelial carcinoma. Other adjustments included changes in systemic chemotherapy for synovial sarcoma and desmoplastic small-round-cell tumor, as well as the identification of more appropriate treatment options for complex pleural sarcomas and spindle cell/sclerosing rhabdomyosarcoma misclassified as osteosarcoma. These findings emphasize the substantial clinical impact of WGS in correcting misdiagnoses and guiding therapy in sarcoma patients.
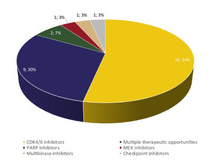
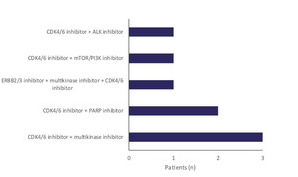
In the cohort of 80 sarcoma patients, WGS analysis revealed genomic biomarkers that could potentially guide enrollment in experimental targeted therapies for 30 individuals, representing 36% of the cohort. Among these, eight patients presented with more than one actionable therapeutic opportunity. The majority of identified targets—26 biomarkers across 25 patients—were associated with alterations in the RB pathway, including CDKN2A loss or inactivating mutations and CDK4 amplification, suggesting potential eligibility for CDK4/6 inhibitor treatment. Additional opportunities included alterations potentially targetable with PARP inhibitors, such as BRCA loss, CHEK2 loss, a CDK12 mutation, and an ATM mutation in five patients. Other actionable events encompassed KDR, PDGFRA, and KIT amplifications suitable for multikinase inhibitors in four patients, an activating NTRK mutation in one patient, and a NRG1 fusion in another. Further options included checkpoint inhibitor therapy for a tumor exhibiting high mutational load (excluding the three melanoma cases), an interstitial ALK deletion treatable with ALK inhibitors, a NRAS mutation potentially responsive to MEK inhibition, and ERBB3 amplification targetable with ERBB2/3 inhibitors. Eight patients commenced biomarker-directed experimental therapy, while eleven additional patients gained potential experimental options following progression on their last standard-of-care treatment. Because these treatments were administered within the context of ongoing clinical trials, detailed data on treatment response and duration were not yet available.
|
|
|
|
a) |
b) |
|
Figure 2. Experimental treatment opportunities identified with WGS. WGS identified experimental therapeutic opportunities for 30 patients (a), including eight patients with two experimental treatment opportunities (b). |
|
Implementing prospective WGS within the diagnostic workflow for sarcoma patients revealed genomic alterations with direct clinical relevance, influencing treatment decisions. In this study, 12 cases underwent diagnostic revision, resulting in modifications to the standard treatment plan for eight patients. Additionally, 30 patients harbored actionable genomic events, and six previously unrecognized pathogenic germline variants were identified. These findings are consistent with previous reports on the value of comprehensive molecular profiling in sarcoma, where actionable alterations are observed in 40–50% of patients and germline mutations are detected in roughly 10–15% of cases. Molecular profiling has also been shown to enhance diagnostic precision in sarcomas, as demonstrated in earlier clinical studies.
Traditional sarcoma diagnostics often rely on iterative pathology testing, whereas WGS enables detection of the full spectrum of genomic alterations in a single analysis. While most biomarkers driving diagnostic revisions could, in theory, have been identified using current standard-of-care assays, they were not captured in routine practice. Notably, this included evaluations performed in regional hospitals without dedicated sarcoma expertise before referral to our tertiary center. Only one case (patient 57) underwent simultaneous NGS-based fusion analysis and WGS, yielding concordant detection of the EWSR1–POU5F1 fusion.
Beyond identifying clinically actionable events, WGS offers several advantages for research and future patient care. First, novel biomarkers can be incorporated immediately into the WGS pipeline without additional validation or expansion of diagnostic panels. This is particularly relevant in light of the 2020 WHO classification updates, which have introduced numerous new gene alterations relevant for diagnosis, prognosis, and therapy selection. Second, germline analysis can reveal pathogenic variants with potential implications for patients and their relatives, even when the gene’s role in sarcoma is not fully established, as demonstrated by the CHEK2 variants identified here. Third, comprehensive genomic profiling can improve our understanding of tumor biology, which may aid interpretation of clinical trials and guide therapeutic strategies. For instance, myxofibrosarcomas and undifferentiated pleomorphic sarcomas share overlapping genomic landscapes, suggesting that similar treatment approaches may be appropriate despite phenotypic differences. Finally, WGS allows exploration beyond known cancer-associated genes, potentially leading to discovery of sarcoma-specific drivers not captured in carcinoma-centric gene panels. The study also highlighted a technical limitation of conventional NGS panels, which often miss large KIT exon 11 deletions in GISTs, suggesting that broad genomic profiling could improve detection of such alterations.
The higher rate of diagnostic revisions observed in this study (14%) compared with prior reports (3%) may reflect patient selection. Our cohort consisted of adult patients with advanced or metastatic disease referred to a tertiary sarcoma center, many with diagnostically challenging cases such as synovial sarcomas with epithelial components, melanomas with loss of immunohistochemical markers, and rhabdomyosarcoma subtype misclassifications. This likely represents a preselected population where clinicians prioritized WGS for complex cases. Current reimbursement policies in the Netherlands support WGS primarily for diagnostically challenging tumors. While this limits generalizability to all sarcoma patients, the findings underscore the value of comprehensive molecular profiling for complex cases.
Conclusion
This study demonstrates that WGS can have immediate clinical impact in a tertiary sarcoma referral setting, guiding diagnostic clarification, uncovering therapeutic opportunities, and identifying previously unrecognized germline variants. Comprehensive genomic profiling should be considered in sarcoma patients with diagnostically challenging tumors, both to inform current clinical management and to advance research in these rare malignancies.
Acknowledgments: The authors would like to thank Judith Westra and Sandra Visser for their contributions in patient inclusion, and Nina Jacobs for assistance in data collection and analysis.
Conflict of Interest: None
Financial Support: This research was supported by the Netherlands Organisation for Health Research and Care innovation ZonMw (Project No. 446002004), and an in kind contribution of Hartwig Medical Foundation. ZonMw had no role in design and conduct of the study, nor writing of the manuscript.
Ethics Statement: None